
Microalbuminuria in diabetes means that a moderately increased amount of albumin is detected in urine. It may be an early marker of kidney damage, even when serum creatinine and estimated glomerular filtration rate (eGFR) appear relatively normal.
The term microalbuminuria is still commonly used, but current medical guidelines generally refer to it as moderately increased albuminuria (A2).
A urine albumin-to-creatinine ratio (uACR) between 30 and 299 mg/g falls within this category.
However, one abnormal urine test does not automatically confirm diabetic kidney disease. Urine albumin can increase temporarily because of infection, fever, strenuous exercise or other medical factors.
Urine ACR, eGFR, repeat testing and clinical evaluation help determine whether albuminuria is persistent and what may be causing it.
Albumin is a protein normally found in the bloodstream.
Healthy kidneys contain tiny filtering structures called glomeruli. These help remove waste products and excess fluid while retaining most albumin in the blood.
When certain kidney conditions affect the filtration barrier, increased amounts of albumin may pass into urine.
This is called albuminuria.
In people with diabetes, long-term exposure to elevated blood glucose can damage the small blood vessels and filtering structures within the kidneys.
However, albuminuria may also develop because of hypertension, glomerular disease or other medical conditions.
Microalbuminuria is an older term describing a moderately increased amount of albumin in urine.
Contemporary classification generally uses:
A1: Normal to mildly increased albuminuria.
A2: Moderately increased albuminuria.
A3: Severely increased albuminuria.
The term microalbuminuria does not mean that the albumin molecules are smaller than normal. It refers to the amount detected in urine.
Albuminuria is an important marker used when evaluating kidney health and cardiovascular risk.
Persistent albuminuria may indicate kidney damage even when overall kidney filtration remains relatively preserved.
It is also associated with increased cardiovascular risk.
However, albuminuria does not always mean that a person has diabetic kidney disease, and it does not predict the same outcome for everyone.
Early abnormalities may remain stable, improve or progress depending on the underlying condition and other health factors.
Yes.
Early diabetic kidney disease often develops without noticeable symptoms.
A person may have:
No swelling.
Normal-looking urine.
No pain.
Relatively preserved eGFR.
Serum creatinine within the laboratory reference range.
Yet urine ACR testing may identify increased albumin.
This is why blood and urine investigations are important when assessing kidney health in people with diabetes.
Learn more about Diabetic Kidney Disease With Normal Creatinine.
A urine microalbumin test is an investigation used to detect small increases in urinary albumin.
The commonly recommended measurement is the urine albumin-to-creatinine ratio (uACR).
It measures albumin relative to creatinine in a urine sample.
Using the ratio helps account for differences in urine concentration caused by hydration and other factors.
Urine ACR is useful for screening and monitoring kidney abnormalities in people with diabetes, hypertension and chronic kidney disease.
Urine ACR testing is usually performed using a single urine sample.
A sample can be collected at a convenient time.
This is commonly used for routine screening.
A 24-hour urine collection is not usually necessary for initial urine albumin screening.
A first-morning specimen may be preferred when confirming an abnormal result.
It can help reduce some variation related to physical activity and changes in urine concentration.
The laboratory measures urinary albumin and creatinine and calculates their ratio.
Results may be reported in mg/g or mg/mmol.
The units matter because these two reporting systems use different numerical ranges.
Follow the collection instructions provided by the laboratory or healthcare professional.
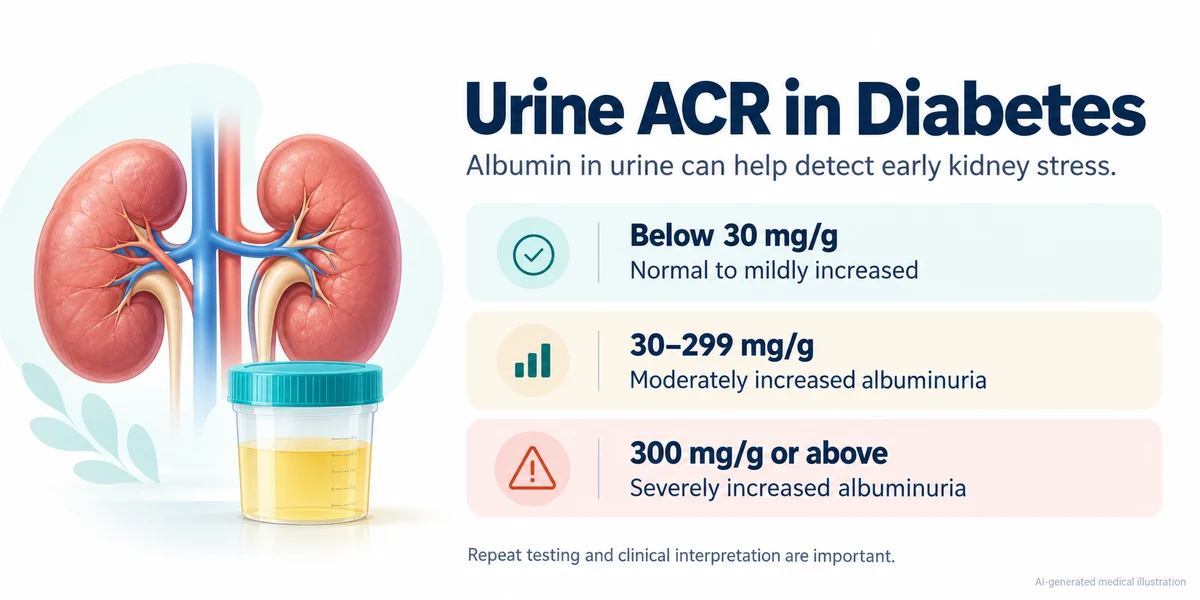
Urine ACR is commonly expressed as milligrams of albumin per gram of creatinine (mg/g).
| Urine ACR (mg/g) | Category | General interpretation |
|---|---|---|
| Below 30 | A1 | Normal to mildly increased |
| 30–299 | A2 | Moderately increased albuminuria |
| 300 or above | A3 | Severely increased albuminuria |
An ACR below 30 mg/g falls within the normal to mildly increased albuminuria category.
However, a result in this range does not independently rule out kidney disease.
Other abnormalities, including reduced eGFR or structural kidney disorders, may still be present.
This is classified as moderately increased albuminuria.
It may suggest kidney damage when persistent, particularly in people with relevant risk factors such as diabetes or hypertension.
However, repeat testing and clinical evaluation are important.
This is classified as severely increased albuminuria.
It may be associated with greater kidney and cardiovascular risk, depending on the overall medical condition.
Further evaluation may be appropriate to determine the cause and identify associated complications.
Important: These categories describe urine albumin levels. They do not independently establish the diagnosis or cause of kidney disease.
For a more detailed explanation, read Urine ACR Test Explained.
Yes.
A single elevated urine ACR may be influenced by temporary factors.
Possible contributors include:
Fever or acute illness.
Urinary tract infection.
Strenuous exercise.
Menstruation or specimen contamination.
Markedly elevated blood glucose.
Markedly elevated blood pressure.
Heart failure or other acute medical conditions.
These factors can temporarily influence urinary albumin measurements.
They should be considered when interpreting a result, but an abnormal finding should not automatically be dismissed.
Urine concentration can affect urine albumin measurements, particularly when albumin concentration is assessed without creatinine.
The albumin-to-creatinine ratio helps reduce this variation.
However, significant dehydration may affect kidney function or coincide with acute illness.
The result should be interpreted in clinical context.
Urine albumin excretion varies naturally from one measurement to another.
A single elevated result may not establish persistent albuminuria.
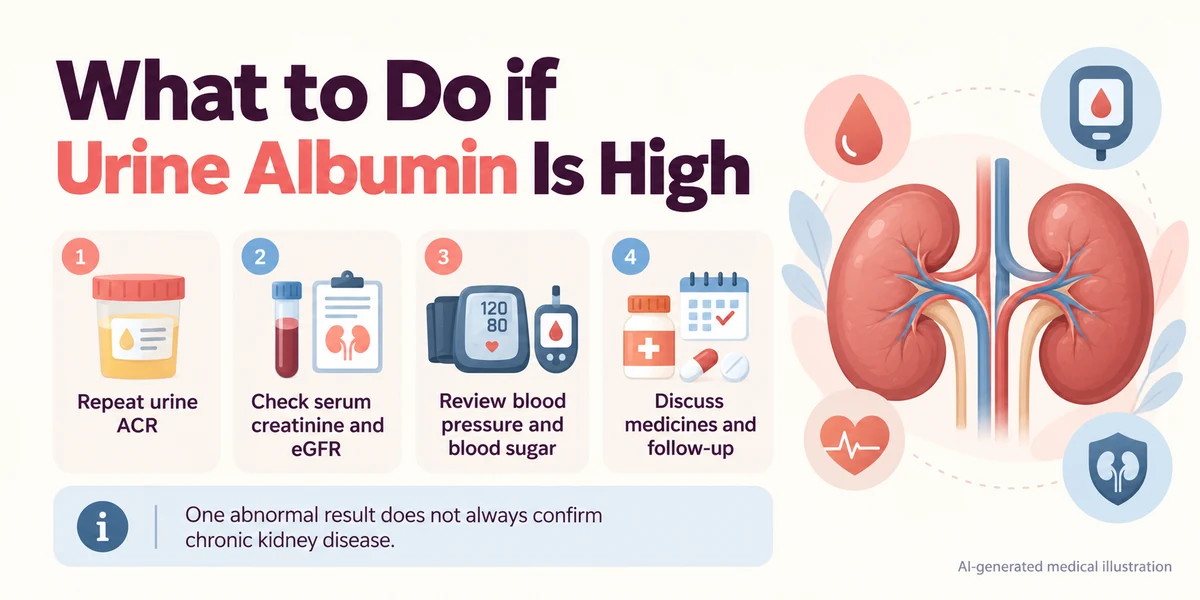
According to ADA guidance, clinicians commonly require at least two abnormal results among three urine ACR measurements obtained over approximately three to six months before considering moderately or severely increased albuminuria persistent.
The timing may be different when significant abnormalities or acute kidney problems require more urgent evaluation.
Not necessarily.
Chronic kidney disease generally involves abnormalities of kidney structure or function that persist for at least three months and have implications for health.
Persistently increased albuminuria is one possible marker.
However, the diagnosis requires consideration of kidney function, clinical findings, repeat measurements and other possible causes.
Yes.
Urine albumin may be increased even when serum creatinine remains within the laboratory reference range.
Serum creatinine is a blood marker used to estimate kidney filtration.
It does not directly measure albumin leakage.
Some people develop increased urine albumin while their eGFR is relatively preserved.
Others develop reduced eGFR without significantly increased albuminuria.
Urine ACR and eGFR should therefore be interpreted together.
| Test | What it measures | Why it matters |
|---|---|---|
| Serum creatinine | Creatinine concentration in blood | Used to help estimate kidney filtration |
| eGFR | Estimated kidney filtering function | Helps assess reduced filtration |
| Urine ACR | Albumin relative to creatinine in urine | Helps detect increased albumin leakage |
| HbA1c | Average blood glucose over approximately 2–3 months | Helps assess diabetes management |
| Blood pressure | Pressure within the arteries | Helps assess hypertension and associated risk |
These tests provide different information and are not interchangeable.
Learn more about Kidney Tests Explained.
The ADA Standards of Care in Diabetes—2026 provides general screening recommendations for adults.
Urine ACR and eGFR should generally be assessed at least annually once type 1 diabetes has been present for five years or longer.
Earlier testing may be appropriate in selected circumstances.
Urine ACR and eGFR should generally be assessed at least annually beginning at diagnosis, regardless of treatment.
Type 2 diabetes may have been present before it was identified.
Patients with established CKD may require urine ACR and eGFR monitoring approximately one to four times per year, or more frequently when clinically indicated.
Testing frequency depends on disease severity, progression risk, medicines and other medical conditions.
Children and adolescents require age-appropriate screening guidance.
Diabetes is an important cause, but it is not the only possible explanation.
Long-term elevated blood glucose can affect kidney filtering structures and may increase urinary albumin excretion.
Hypertension can damage small blood vessels in the kidneys.
It may contribute to albuminuria and reduced kidney filtration.
Certain inflammatory, immune-mediated or other glomerular disorders may cause increased urine albumin or protein.
Fever, urinary infection and acute medical conditions can sometimes cause temporary albumin abnormalities.
Structural, inherited, vascular and other medical kidney conditions may also be associated with albuminuria.
The underlying cause must be determined through clinical assessment rather than the urine ACR result alone.
Moderately increased albuminuria usually does not produce noticeable symptoms by itself.
When kidney disease becomes more advanced, possible symptoms may include:
Persistent foamy urine.
Swelling of the feet or ankles.
Puffiness around the eyes.
Fatigue or weakness.
Changes in urination.
Difficult-to-control blood pressure.
Reduced appetite or nausea.
These symptoms are not specific to diabetic kidney disease.
Foamy urine does not reliably establish albuminuria, and some people with significant kidney abnormalities have no symptoms.
Albuminuria may decrease with appropriate management of the underlying condition.
Possible approaches include:
Appropriate blood glucose control can reduce the risk of diabetes-related complications.
Individual HbA1c goals depend on diabetes type, age, other medical conditions and the risk of hypoglycaemia.
Blood pressure control is important for reducing kidney and cardiovascular risk.
Targets should be individualised according to the patient’s clinical condition and treatment tolerance.
Certain medicines can reduce albuminuria or the risk of kidney disease progression in eligible patients.
Examples include:
ACE inhibitors and ARBs: May be appropriate in selected people with diabetes, hypertension and albuminuria.
SGLT2 inhibitors: May provide kidney and cardiovascular benefits in eligible patients with type 2 diabetes and CKD.
Other treatments: Additional medicines may be considered according to kidney function, albuminuria, cardiovascular risk and other factors.
These treatments have potential adverse effects, contraindications and monitoring requirements.
Patients should not start, stop or change prescribed medicines independently.
Individualised care may include:
Reducing excessive sodium intake.
Avoiding tobacco.
Appropriate physical activity.
Weight management when indicated.
Reviewing medicines and supplements.
Following nutritional advice suited to kidney function and other health conditions.
No herbal remedy, supplement or special diet guarantees that albuminuria will resolve.
Some people experience improvement in albuminuria after appropriate management.
However, a decrease in urine ACR does not necessarily prove that underlying kidney damage has fully reversed.
Established chronic kidney scarring is often not completely reversible.
The outcome depends on the underlying condition, degree of kidney involvement and response to treatment.
No treatment guarantees complete recovery or prevention of kidney failure.
Yes.
Increased urine albumin is associated with higher cardiovascular risk in people with diabetes and other medical conditions.
However, an elevated ACR does not mean that a person currently has heart disease or will definitely experience a cardiovascular event.
Risk assessment also considers:
Blood pressure.
Blood glucose control.
Lipid levels.
Smoking status.
Kidney function.
Age and other clinical factors.
Urine ACR is one component of a broader medical assessment.
Specialist kidney assessment may be appropriate when:
Urine ACR remains significantly elevated.
Albuminuria increases rapidly.
eGFR declines progressively.
Kidney function changes unexpectedly.
Blood and protein are present together in urine.
Difficult-to-control hypertension occurs with kidney abnormalities.
Electrolyte disturbances are present.
The cause of abnormal kidney findings remains unclear.
Advanced chronic kidney disease is suspected.
Not everyone with one mildly increased urine ACR result requires immediate nephrology referral.
The need for specialist assessment depends on the severity, persistence and overall clinical findings.
Seek immediate emergency care for:
Severe breathlessness.
Chest pain.
Confusion or loss of consciousness.
Seizures.
Very little or no urine output accompanied by significant illness.
Rapidly worsening swelling with breathing difficulty.
Persistent vomiting, significant new swelling or rapidly deteriorating kidney function also requires timely medical assessment.
These symptoms can have several causes and should not be attributed to diabetic kidney disease without evaluation.
The following information may help patients understand and discuss their test results.
| Information | Why it may be useful |
|---|---|
| Latest urine ACR | Shows the measured level of albuminuria |
| Previous urine ACR results | Helps identify persistent or changing abnormalities |
| Serum creatinine | Helps assess kidney filtration |
| eGFR | Estimates overall kidney filtering function |
| HbA1c | Provides information about glucose management |
| Blood pressure readings | Helps assess hypertension-related risk |
| Current medication list | Supports review of medicine-related factors |
| Recent illness or exercise | May help explain temporary changes |
| Urinalysis | May identify blood or other urinary abnormalities |
Not every person needs all these investigations. Testing should be selected according to clinical circumstances.
Measures a waste product in blood and helps assess kidney function.
Estimates kidney filtration and assists with CKD assessment and monitoring.
Measures albumin leakage in urine and helps detect kidney damage.
Checks for blood, protein, infection-related findings and other abnormalities.
Evaluates potassium, sodium, bicarbonate and other substances that may be affected by kidney function.
May help evaluate kidney structure, urinary obstruction and selected other abnormalities.
Additional testing, including cystatin C, immune-related blood tests or kidney biopsy, may be considered when clinically appropriate.
Not every person requires every test.
A kidney specialist usually begins by reviewing the individual’s symptoms, past medical history, existing conditions, medicines and previous investigation results.
A clinical assessment may involve:
Reviewing serum creatinine, eGFR and urine reports.
Checking blood pressure and relevant physical findings.
Assessing diabetes, hypertension and other risk factors.
Reviewing medicines and supplements.
Considering additional blood, urine or imaging tests.
Discussing findings, monitoring requirements and possible treatment approaches.
A kidney biopsy or other specialised investigation is recommended only when medically indicated.
Treatment recommendations depend on the diagnosis, kidney function, other illnesses and individual medical circumstances.
If available, previous medical records can provide information about changes in kidney function over time.
Relevant records may include:
Serum creatinine and eGFR reports
Urine routine and ACR results
Blood pressure readings
Blood glucose and HbA1c reports
Current medicine and supplement list
Ultrasound or other imaging results
Previous hospital discharge summaries
Relevant kidney biopsy reports
Fasting is not routinely required before a nephrology consultation. Whether fasting is necessary for a particular blood investigation should be confirmed with the treating healthcare professional or laboratory.
Some kidney-related conditions require urgent medical assessment rather than a routine specialist consultation.
Seek emergency care for:
Very little or no urine, particularly when newly developed
Severe breathlessness or chest pain
Confusion or reduced consciousness
Severe illness with rapidly worsening kidney function
High fever with flank pain, particularly when accompanied by vomiting or marked weakness
Sudden severe pain with suspected urinary obstruction or infection
The urgency of a medical condition cannot be determined from an online article alone.
Early evaluation may identify kidney abnormalities before symptoms become noticeable.
Depending on the underlying diagnosis, timely management may help address reversible causes, control associated medical conditions and slow kidney disease progression in some individuals.
However, kidney diseases have different causes and outcomes. Early evaluation does not guarantee reversal or recovery.
Regular monitoring may be particularly relevant for people with diabetes, hypertension or known kidney disease.
For further information, see the KDIGO Clinical Practice Guidelines.
General kidney health measures include:
Following recommended screening schedules.
Monitoring blood pressure when indicated.
Managing diabetes according to an individual treatment plan.
Avoiding unnecessary use of potentially kidney-harming medicines.
Discussing supplements with a healthcare professional.
Maintaining appropriate physical activity and nutrition.
Attending follow-up appointments for known kidney conditions.
Fluid intake, protein intake and medication recommendations vary according to individual kidney function and medical needs.
Avoid making major dietary or medication changes based solely on online advice.
A normal UACR is less than 30 mg of albumin per gram of creatinine. Values between 30 and 300 mg/g indicate microalbuminuria, and above 300 mg/g suggest macroalbuminuria.
Guidelines recommend an annual spot‑sample UACR for adults with diabetes aged 12–70. If microalbuminuria is detected, repeat testing every 3–6 months until the trend is clear.
No. A single elevated result may be due to temporary factors like fever or intense exercise. Two of three positive tests over 3–6 months are needed to confirm true microalbuminuria.
ACE inhibitors or ARBs, tight blood pressure control, optimal glycemic management, low‑sodium diet, and lifestyle changes such as regular exercise and smoking cessation are proven to reduce albumin excretion.
Seek specialist care if you have macroalbuminuria, a declining eGFR (< 60 mL/min/1.73 m²), persistent high UACR despite treatment, or uncontrolled hypertension or diabetes.
Microalbuminuria is a low‑grade protein leak (30–300 mg/g) detectable only with specific tests, whereas proteinuria (macroalbuminuria) is a higher level (> 300 mg/g) that can be seen on standard dipsticks.
Microalbuminuria, now generally described as moderately increased albuminuria, is an important finding when evaluating kidney health in people with diabetes.
Urine ACR testing helps detect increased albumin that may appear before a substantial decline in kidney filtration.
However, a single abnormal result does not automatically establish diabetic kidney disease.
Repeat urine measurements, eGFR, previous results and clinical assessment help determine whether albuminuria is persistent and identify its possible cause.
Appropriate diabetes care, blood pressure management and selected treatments may reduce kidney-related risks, but outcomes vary between individuals.
Medical Information: Dr. Jyoti Bansode | MBBS, MD Medicine, DM Nephrology | Medical Registration No.: 2011/06/1863 | Maharashtra Medical Council (MMC).
Medical Review Status: Pending review and approval by Dr. Jyoti Bansode.
Medical Disclaimer: Website content and visuals are for general informational, educational and representational purposes only, may not reflect individual patient conditions or outcomes, and do not replace personalised medical advice, diagnosis or clinical assessment.
Plot no 70, Moreshwar Heritage, Sector 5, Ulwe, Navi Mumbai, Maharashtra 410206
For Booking: +91 8591009591
Chat With Us
Mini Sea Shore Road, Juhu Nagar, Sector 10A, Vashi, Navi Mumbai, Maharashtra 400703
Chat With Us