
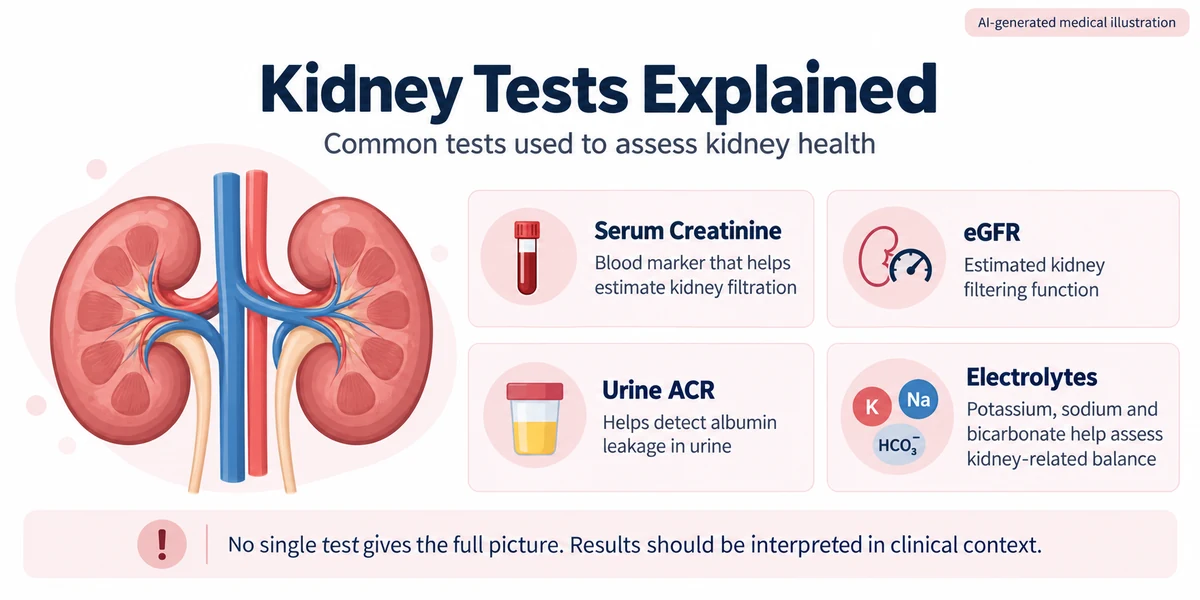
Kidney function tests help assess how effectively the kidneys filter waste products, regulate fluid balance and maintain essential electrolytes in the body. Common investigations include serum creatinine, estimated glomerular filtration rate (eGFR), urine albumin-to-creatinine ratio (uACR), blood urea nitrogen (BUN) and electrolyte measurements.
These tests provide different types of information. Some measure substances in the blood, while others detect abnormalities in urine.
The two key tests used to detect and monitor chronic kidney disease are eGFR and urine ACR. Additional investigations may help evaluate electrolyte disturbances, the possible cause of kidney dysfunction and associated complications.
Understanding what each test measures can help patients interpret their reports more accurately, although laboratory results must always be considered alongside medical history and clinical findings.
According to the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), blood and urine tests can help identify kidney abnormalities even when noticeable symptoms are absent.
The kidneys perform several essential functions, including:
Removing waste products from the bloodstream.
Regulating fluid and electrolyte balance.
Helping maintain the body’s acid–base balance.
Contributing to blood pressure regulation.
Supporting red blood cell production through hormone activity.
Helping regulate bone and mineral metabolism.
When kidney function becomes impaired, waste products or electrolytes may accumulate or fall outside expected ranges.
Kidney disease often develops without noticeable symptoms, particularly in its early stages.
Blood and urine tests can identify abnormalities before symptoms become apparent.
However, abnormal results do not always indicate permanent kidney damage. Temporary illness, dehydration, medicines and other factors may influence laboratory measurements.
Kidney investigations can be divided into tests of filtration, urine abnormalities and complications.
| Kidney Test | What It Measures | Why It Matters |
|---|---|---|
| Serum Creatinine | Creatinine concentration in blood | Helps estimate kidney filtration |
| eGFR | Estimated kidney filtering function | Helps assess and classify reduced filtration |
| Urine ACR | Albumin relative to creatinine in urine | Helps detect albumin leakage |
| Urinalysis | Protein, blood and other urine findings | Helps identify urinary or kidney abnormalities |
| Blood Urea Nitrogen (BUN) | Urea nitrogen concentration in blood | Provides additional information alongside other findings |
| Potassium | Blood potassium concentration | Identifies potentially important electrolyte disturbances |
| Sodium | Blood sodium concentration | Helps assess water and electrolyte balance |
| Bicarbonate | Blood bicarbonate concentration | Helps evaluate acid–base balance |
| Calcium and Phosphorus | Mineral concentrations | May help assess complications of kidney disease |
Important: Not every person requires every test. The appropriate investigations depend on individual risk factors, symptoms and clinical findings.
Creatinine is a waste product formed during normal muscle metabolism.
The kidneys remove creatinine from the bloodstream, mainly through filtration.
Serum creatinine may increase because of reduced kidney filtration, dehydration, certain medicines or other factors. Read more about What Causes High Creatinine and how abnormal results are evaluated. measures its concentration in blood.
When kidney filtration declines, creatinine often increases.
However, serum creatinine is not a direct measurement of kidney damage.
Reference ranges vary according to laboratory methods and individual characteristics.
Illustrative adult ranges used by some laboratories include:
| Group | Approximate Creatinine Range |
|---|---|
| Adult Men | 0.7–1.3 mg/dL |
| Adult Women | 0.6–1.1 mg/dL |
Important: These values are general examples. The reference range on the laboratory report should be used for interpretation.
A creatinine result can be affected by:
– Muscle mass.
– Age.
– Recent intense physical activity.
– Cooked meat consumption.
– Creatine supplementation.
– Certain medicines.
– Kidney filtration and hydration status.
Someone with relatively low muscle mass may have reduced kidney function without a markedly elevated creatinine result.
Similarly, a person with high muscle mass may have a higher creatinine level without necessarily having kidney disease.
High creatinine may result from reduced kidney filtration associated with:
– Acute kidney injury.
– Chronic kidney disease.
– Significant dehydration.
– Urinary tract obstruction.
– Other medical conditions affecting kidney function.
It may also be influenced by non-kidney factors.
Read more about What Causes High Creatinine.
Important: A single high creatinine reading does not establish kidney failure or determine the need for dialysis.
The eGFR Kidney Function Test helps estimate kidney filtration and provides useful information when evaluating chronic kidney disease.
In adults, eGFR is commonly calculated using serum creatinine, age and sex through a validated estimating equation.
The result is usually reported in mL/min/1.73 m².
eGFR provides a more useful estimate of kidney filtration than serum creatinine alone in many clinical situations.
However, it remains an estimate and has limitations.
| eGFR (mL/min/1.73 m²) | Category | General interpretation |
|---|---|---|
| 90 or above | G1 | Normal or high |
| 60–89 | G2 | Mildly decreased |
| 45–59 | G3a | Mildly to moderately decreased |
| 30–44 | G3b | Moderately to severely decreased |
| 15–29 | G4 | Severely decreased |
| Below 15 | G5 | Kidney failure range |
An eGFR below 60 that persists for at least three months meets one criterion for chronic kidney disease.
However, an eGFR of 60 or above does not establish CKD unless there is other evidence of kidney damage.
Yes. eGFR may change because of:
– Acute illness.
– Changes in kidney function.
– Laboratory variation.
– Medicines.
– Changes in creatinine production.
– Hydration-related effects.
Small differences between test results do not always mean kidney disease is progressing.
Clinicians consider trends over time rather than interpreting every change in isolation.
Creatinine-based eGFR may be less accurate in certain situations, including:
– Unusually high or low muscle mass.
– Rapidly changing kidney function.
– Certain changes in diet or nutritional status.
– Selected medical conditions affecting creatinine production.
In some cases, clinicians may use cystatin C, another blood marker, to obtain an additional estimate of kidney filtration.
Combined creatinine and cystatin C equations can improve estimation accuracy in appropriate clinical circumstances.
Read more about the eGFR Kidney Function Test.
The urine albumin-to-creatinine ratio (uACR) measures the amount of albumin relative to creatinine in urine.
Albumin is a protein normally retained in the bloodstream by the kidneys’ filtering structures.
When these structures are affected by certain diseases, increased amounts of albumin may pass into urine.
This is called albuminuria.
Urine ACR is particularly useful in people with diabetes, hypertension or suspected chronic kidney disease.
| Urine ACR | Category | General interpretation |
|---|---|---|
| Below 30 mg/g | A1 | Normal to mildly increased |
| 30–300 mg/g | A2 | Moderately increased |
| Above 300 mg/g | A3 | Severely increased |
An ACR of 30 mg/g or above is considered increased albuminuria. Exact classification and interpretation require attention to the laboratory result and clinical context.
Yes.
Urine albumin may be increased even when serum creatinine is within the laboratory reference range and eGFR is relatively preserved.
This can occur in some people with early diabetic kidney disease or other kidney filtering disorders.
However, increased urine albumin does not automatically identify the underlying disease.
Yes. Albuminuria may be influenced by factors such as:
– Fever or acute illness.
– Urinary infection.
– Strenuous exercise.
– Menstruation or contamination of the sample.
– Temporarily elevated blood pressure or blood glucose.
Repeat testing may be necessary to determine whether albuminuria is persistent.
A first-morning urine specimen may be useful in selected situations.
Learn more about the Urine ACR Test.
Urinalysis is a commonly used investigation that examines urine for different abnormalities.
Depending on the method, it may help identify:
– Protein.
– Blood.
– Glucose.
– White blood cells.
– Nitrites.
– Changes in urine concentration.
– Crystals or other microscopic findings.
A urine dipstick and microscopic examination provide different types of information.
Protein in urine may indicate a kidney filtering abnormality, but it can also occur temporarily.
Urine ACR or protein-to-creatinine ratio testing may be recommended to quantify the finding.
Blood in urine can be associated with urinary infection, stones, kidney filtering diseases and other urinary tract conditions.
Visible blood in urine should be medically evaluated.
No.
Some kidney conditions may not produce detectable abnormalities on a routine urine dipstick.
eGFR, urine ACR and other investigations may still be necessary when kidney disease is suspected.
Urea is produced during the breakdown of protein and is removed partly through the kidneys.
Blood urea nitrogen measures the nitrogen component of urea in the bloodstream.
BUN levels may increase when kidney function is reduced.
However, BUN can also be influenced by:
– Dehydration.
– Dietary protein intake.
– Gastrointestinal bleeding.
– Certain medicines.
– Other medical conditions.
This makes BUN less specific for kidney filtration than eGFR.
Some laboratories use an adult reference range of approximately 7–20 mg/dL.
Reference intervals vary.
BUN and blood urea are not reported in identical units, so the numbers should not be directly compared without considering the laboratory measurement.
BUN is generally interpreted alongside creatinine, eGFR, symptoms and other clinical findings.
The kidneys help maintain appropriate levels of electrolytes in the bloodstream.
Electrolytes are essential for nerve activity, muscle contraction, fluid balance and many other body functions.
Potassium helps regulate muscle and heart electrical activity.
High potassium, called hyperkalemia, may occur when kidney function is impaired or because of certain medicines and other conditions.
Severe hyperkalemia can cause dangerous heart rhythm disturbances.
Low potassium can also occur due to medicines, gastrointestinal fluid losses or other medical problems.
Potassium results must be interpreted alongside kidney function, medication history and clinical findings.
Sodium is important for fluid and nerve function.
Low sodium, or hyponatremia, may occur when water balance is disturbed.
High sodium, or hypernatremia, often relates to a relative deficit of body water.
Abnormal sodium levels are not specific to kidney disease.
Bicarbonate helps maintain normal blood acid–base balance.
Reduced bicarbonate can be associated with metabolic acidosis.
Metabolic acidosis may occur in advanced kidney dysfunction, but it also has several other causes.
Calcium and phosphorus contribute to bone and mineral metabolism.
Chronic kidney disease can affect mineral regulation, particularly in more advanced stages.
Additional tests, such as parathyroid hormone, may be requested when clinically indicated.
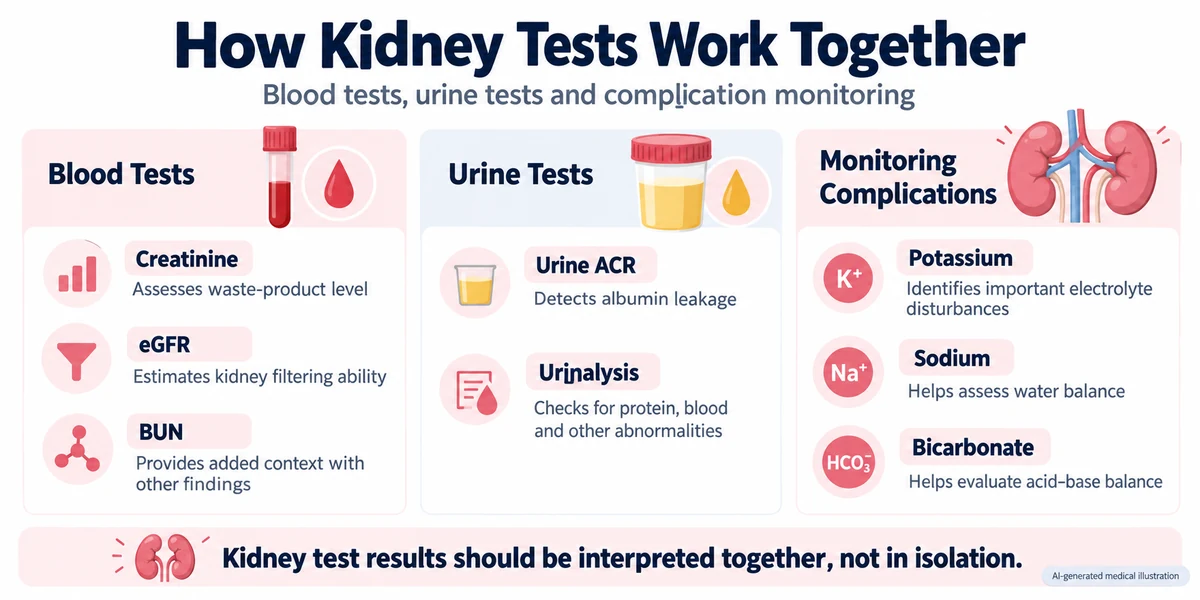
Each test measures a different aspect of kidney health.
Creatinine provides a blood concentration used to estimate kidney filtration.
eGFR estimates the rate at which the kidneys filter blood.
Urine ACR evaluates albumin leakage, which may indicate kidney damage.
For example, a person may have relatively preserved eGFR but persistently increased urine albumin.
Another person may have reduced eGFR without significantly increased albuminuria.
Both patterns may require evaluation, depending on the medical history and persistence of the findings.
This is why CKD classification incorporates the cause of kidney disease, eGFR category and albuminuria category.
The KDIGO CKD Evaluation and Management Guidelines describe how kidney function, albuminuria and clinical findings contribute to CKD diagnosis and risk assessment.The overall risk of kidney disease progression depends on more than one laboratory number.
Yes.
Serum creatinine alone may not identify some early kidney abnormalities.
Albuminuria may develop before a significant decrease in filtration becomes apparent.
In addition, creatinine levels depend on muscle mass and other factors.
A person with relatively low muscle mass may have impaired kidney function despite a creatinine value that appears normal.
Therefore, a normal creatinine result does not always exclude kidney disease.
Kidney testing is particularly important for people with medical conditions or risk factors associated with kidney disease.
These include:
– Diabetes.
– High blood pressure.
– Cardiovascular disease.
– A family history of kidney failure.
– Previously abnormal kidney function tests.
– Known chronic kidney disease.
– Conditions or medicines that may affect kidney function.
Routine kidney screening is not necessarily required at the same frequency for everyone.
A healthcare professional can determine appropriate investigations and intervals based on individual risks.
Testing frequency depends on the medical condition and previous results.
For many adults with diabetes, annual eGFR and urine ACR testing is recommended.
People with existing kidney disease or changing clinical findings may require more frequent monitoring.
Kidney function assessment may be appropriate for people with high blood pressure.
The frequency depends on kidney function, blood pressure control, medicines and other risk factors.
Monitoring depends on eGFR, urine albumin levels, disease progression and associated complications.
Some patients require testing more frequently than once a year.
Repeat testing may be needed sooner when acute kidney injury, significant electrolyte abnormalities or a rapid change in kidney function is suspected.
There is no universal schedule suitable for every patient.
Fasting is not usually required for serum creatinine, eGFR or urine ACR testing alone.
However, other blood tests collected at the same time may have different preparation requirements.
Patients should follow the instructions provided by their laboratory or healthcare professional.
Before testing, it may be helpful to mention:
– Current medicines.
– Recent strenuous exercise.
– Creatine supplements.
– Recent acute illness.
– Other factors that might influence results.
Do not stop prescribed medicines or deliberately increase or restrict fluid intake without medical instructions.
Not every abnormal laboratory finding reflects permanent kidney damage.
Possible contributing factors include:
– Dehydration.
– Temporary illness.
– Recent intense exercise.
– Certain medicines.
– Dietary influences on creatinine.
– Urinary infection.
– Laboratory variability.
– Acute kidney injury.
However, acute kidney injury itself can be serious and may need urgent treatment.
A healthcare professional considers the test result, previous measurements, symptoms and clinical history to determine its significance.
Further evaluation may be appropriate when:
– Serum creatinine increases unexpectedly.
– eGFR is persistently reduced.
– Urine ACR remains elevated.
– Protein or blood is repeatedly detected in urine.
– Electrolyte abnormalities persist.
– Kidney-related symptoms accompany abnormal laboratory results.
– Kidney function changes rapidly.
The urgency depends on how abnormal the result is, whether it is changing and whether serious complications are suspected.
Seek urgent emergency assessment for:
– Severe breathlessness.
– Chest pain.
– Confusion, seizures or loss of consciousness.
– Very little or no urine output with acute illness.
– Rapidly worsening swelling accompanied by breathing difficulty.
– Known dangerously elevated potassium or other critical laboratory results.
A routine online enquiry should not be used for medical emergencies.
Fact: Early kidney damage may be present despite creatinine being within the laboratory reference range.
Fact: eGFR may decrease temporarily during acute illness. Chronic kidney disease generally requires abnormalities persisting for at least three months.
Fact: Foamy urine has several possible causes. Urine testing is required to determine whether abnormal protein is present.
Fact: Dialysis decisions depend on clinical symptoms, complications, kidney function and overall medical assessment, not one test result.
Fact: Excessive water intake does not treat every cause of high creatinine and can be harmful in certain medical conditions.
The following checklist may help patients understand which reports are relevant.
| Test or Record | Why It May Be Useful |
|---|---|
| Previous Serum Creatinine | Helps identify changes over time. |
| eGFR | Estimates kidney filtering function. |
| Urine ACR | Assesses albumin leakage. |
| Urinalysis | Checks for blood, protein and other abnormalities. |
| BUN or Blood Urea | Provides additional information about waste-product levels. |
| Electrolytes | Helps identify potassium, sodium or bicarbonate disturbances. |
| Blood Pressure Records | Provides information about hypertension. |
| Diabetes-Related Results | Helps assess associated metabolic risk. |
| Current Medication List | Helps identify medicines affecting kidney function. |
Important: Not every person requires all these investigations. Testing should be selected according to individual clinical circumstances.
Kidney tests measure waste removal (creatinine, eGFR), protein leakage (uACR), and mineral balance (electrolytes). Together they reveal how well the kidneys filter blood and whether early damage is present.
The urine albumin‑to‑creatinine ratio (uACR) is the most sensitive early marker, often detecting damage before eGFR declines. Serum creatinine and eGFR confirm overall filtration capacity.
Persistent fatigue, swelling, changes in urine, high blood pressure, and unexplained muscle cramps should trigger a kidney panel, including creatinine, eGFR, uACR, and electrolytes.
Creatinine provides the raw waste level, while eGFR translates it into an estimated filtration rate adjusted for age, sex, and body size. A high creatinine with a normal eGFR may be due to muscle mass; a low eGFR with normal creatinine often signals early CKD.
See a nephrologist if eGFR falls below 60 mL/min/1.73 m², uACR is ≥30 mg/g, electrolytes stay abnormal, or creatinine rises rapidly. Early referral improves outcomes.
Myths include believing a normal creatinine rules out disease, that only diabetics need testing, or that low potassium always means kidney failure. In reality, multiple tests and risk factors guide accurate assessment.
Kidney function tests provide important information about filtration, urine protein leakage, electrolyte regulation and possible kidney-related complications.
Serum creatinine and eGFR help assess filtration, while urine ACR can identify increased albumin that may indicate kidney damage.
Electrolyte measurements, urinalysis and BUN provide additional information when clinically indicated.
No single laboratory test gives a complete picture of kidney health.
Results should be interpreted alongside previous measurements, symptoms, medical history and other clinical findings.
Appropriate testing and medical assessment help identify abnormalities and guide individual decisions about monitoring and treatment.
Medical Information: Dr. Jyoti Bansode | MBBS, MD Medicine, DM Nephrology | Medical Registration No.: 2011/06/1863 | Maharashtra Medical Council (MMC).
Disclaimer: Website content and visuals are for general informational, educational and representational purposes only, may not reflect individual patient conditions or outcomes, and do not replace personalised medical advice, diagnosis or clinical assessment.
Plot no 70, Moreshwar Heritage, Sector 5, Ulwe, Navi Mumbai, Maharashtra 410206
For Booking: +91 8591009591
Chat With Us
Mini Sea Shore Road, Juhu Nagar, Sector 10A, Vashi, Navi Mumbai, Maharashtra 400703
Chat With Us