
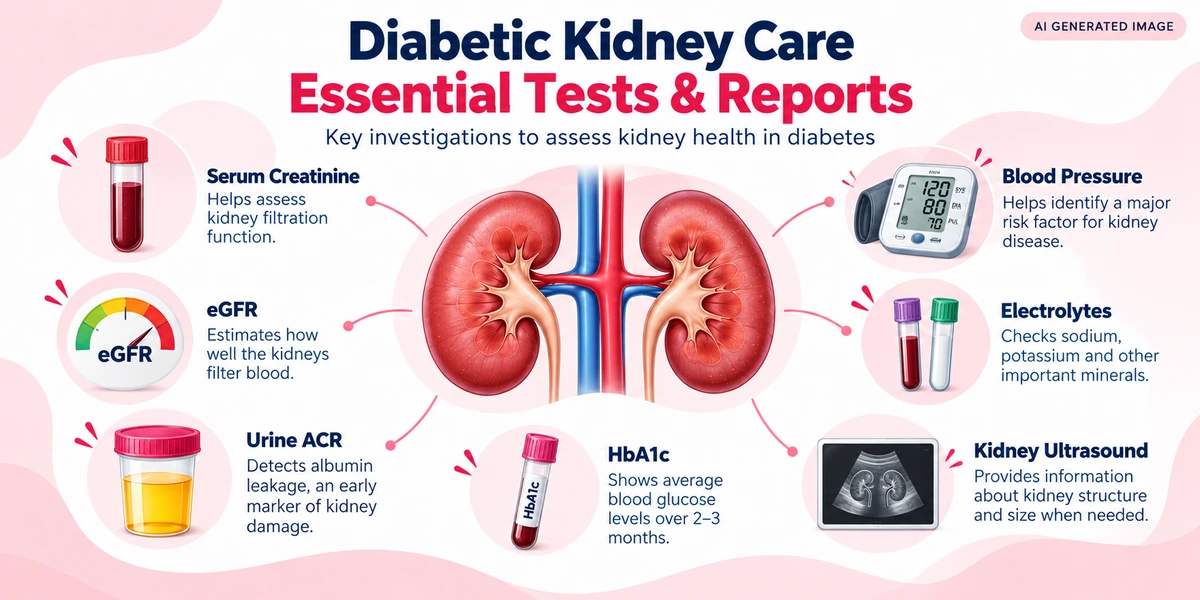
People with diabetes may develop kidney abnormalities even when they have no noticeable symptoms. Blood and urine investigations, particularly serum creatinine, estimated glomerular filtration rate (eGFR) and urine albumin-to-creatinine ratio (ACR), help assess kidney function and identify possible kidney damage.
Keeping previous kidney test reports, HbA1c results, blood pressure records and medication details can help healthcare professionals understand changes in kidney health over time.
Not everyone needs every investigation before a kidney consultation. Test selection depends on individual medical history, symptoms and clinical findings.
Diabetic kidney disease (DKD) refers to kidney damage associated with diabetes.
Over time, persistently elevated blood glucose can affect the small blood vessels and filtering structures inside the kidneys, known as glomeruli.
These changes may lead to increased albumin in urine, reduced kidney filtration or both.
Diabetic kidney disease is one of the important causes of chronic kidney disease (CKD). However, kidney abnormalities in a person with diabetes are not always caused by diabetes itself.
Other kidney conditions, medicines, infections or medical problems may also affect kidney function.
Related Reading: Diabetes and Kidney Diseases
Early diabetic kidney disease often develops without obvious symptoms.
A person may feel well while urine tests show increased albumin or blood tests reveal changes in kidney filtration.
Regular kidney assessment can help healthcare professionals:
Identify albumin leakage into urine.
Monitor kidney filtration.
Assess changes in kidney function over time.
Evaluate complications associated with diabetes and hypertension.
Review the suitability and safety of certain medicines.
Determine whether further investigations are necessary.
Kidney tests help guide medical decisions, but no single result provides a complete picture of kidney health.
The following reports may be useful when assessing kidney health in someone with diabetes.
Serum creatinine is a blood test measuring creatinine, a waste product produced during normal muscle metabolism.
The kidneys normally remove creatinine from the bloodstream.
Higher-than-expected creatinine may suggest reduced kidney filtration, but results can also be affected by muscle mass, diet, certain medicines and other factors.
A single creatinine result does not automatically establish chronic kidney disease.
Previous reports may help determine whether creatinine is stable, rising or improving.
Related Reading: What Causes High Creatinine?
Estimated glomerular filtration rate helps estimate how well the kidneys filter blood.
It is commonly calculated using serum creatinine, age and sex.
Some clinical situations may require additional testing, such as cystatin C, to improve estimation accuracy.
eGFR values are generally reported in mL/min/1.73 m².
A persistently reduced eGFR may indicate chronic kidney disease, but temporary illness, acute kidney injury and other factors can affect the result.
Doctors consider eGFR together with urine findings and previous reports.
Urine ACR measures the amount of albumin relative to creatinine in a urine sample.
Albumin is a protein normally retained mainly in the bloodstream.
Increased albumin in urine may indicate damage to the kidneys’ filtering structures.
Urine ACR is particularly useful in diabetes because albumin leakage can appear before a significant decrease in kidney filtration.
However, not everyone with diabetic kidney disease develops increased albuminuria.
Related Reading: Urine ACR Test Explained
HbA1c reflects average blood glucose levels over approximately the previous two to three months.
It helps assess longer-term diabetes management.
Persistently elevated blood glucose can contribute to kidney damage over time.
However, HbA1c may be less reliable in certain circumstances, including advanced chronic kidney disease, anaemia, altered red blood cell turnover and some medical treatments.
Doctors may use additional glucose measurements when appropriate.
Blood glucose targets should be individualised.
Blood pressure monitoring is important because diabetes and hypertension can both contribute to kidney disease.
High blood pressure may worsen existing kidney damage, while kidney disease can also make blood pressure more difficult to control.
Available home and clinic blood pressure readings can provide useful information.
The frequency of home monitoring and appropriate blood pressure targets depend on the individual’s medical condition.
The kidneys help regulate electrolytes and maintain fluid and acid-base balance.
Blood tests may assess:
– Potassium
– Sodium
– Bicarbonate
– Calcium
– Phosphate, when indicated
Electrolyte abnormalities may occur in kidney disease or as a result of certain medicines.
Not every person requires every electrolyte test at each assessment.
A lipid profile measures substances such as LDL cholesterol, HDL cholesterol and triglycerides.
People with diabetes and kidney disease may have an increased risk of cardiovascular complications.
Lipid testing may form part of broader cardiovascular risk assessment.
It is not a direct measure of kidney filtration.
A routine urine examination may help detect:
– Protein
– Blood
– Infection-related changes
– Glucose
– Other urine abnormalities
Urinalysis complements, but does not replace, quantitative urine ACR testing when assessing albuminuria.
Kidney ultrasound may provide information about kidney structure, size and possible urinary obstruction.
It may be considered when there are unexpected kidney abnormalities, suspected structural problems or other clinical indications.
A kidney ultrasound is not routinely necessary before every diabetes-related kidney assessment.
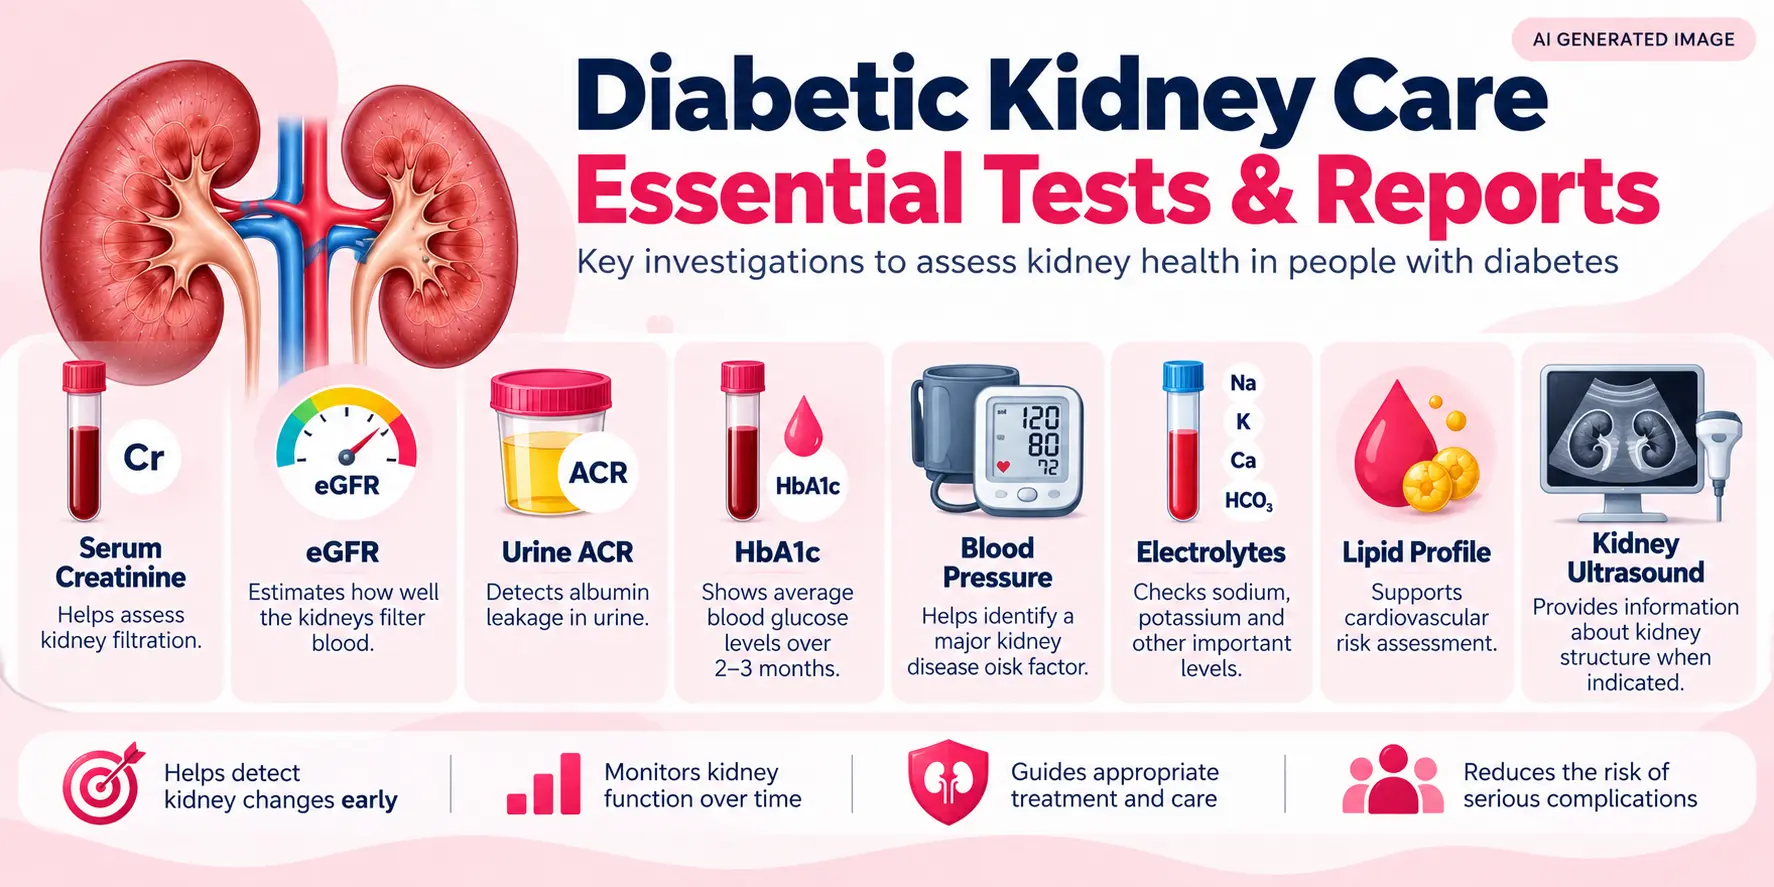
| Test | What it measures | Why it may be useful |
|---|---|---|
| Serum Creatinine | Creatinine concentration in blood | Helps assess kidney filtration |
| eGFR | Estimated kidney filtering function | Helps evaluate and monitor kidney function |
| Urine ACR | Albumin relative to creatinine in urine | Helps identify albumin leakage |
| HbA1c | Average glucose over approximately 2–3 months | Helps assess diabetes management |
| Blood Pressure | Pressure inside blood vessels | Helps identify a major kidney disease risk factor |
| Electrolytes | Potassium, sodium and related substances | Helps detect metabolic abnormalities |
| Lipid Profile | Cholesterol and triglycerides | Supports cardiovascular risk assessment |
| Urinalysis | Blood, protein and other urine findings | Helps investigate urinary abnormalities |
Important: These investigations provide different information. Their results must be interpreted together with medical history and clinical findings.
Urine ACR results are generally classified using the following categories.
| Urine ACR (mg/g) | Category | Meaning |
|---|---|---|
| Below 30 | A1 | Normal to mildly increased |
| 30 to less than 300 | A2 | Moderately increased |
| 300 or above | A3 | Severely increased |
An elevated urine ACR result may suggest kidney damage, but it does not identify the cause by itself.
Temporary factors such as fever, infection, strenuous exercise, menstruation and marked blood glucose or blood pressure elevation can influence urine albumin results.
Repeat testing may be needed to confirm persistent albuminuria.
eGFR categories help describe different levels of kidney filtration.
| eGFR (mL/min/1.73 m²) | GFR category |
|---|---|
| 90 or above | G1 – Normal or high |
| 60–89 | G2 – Mildly decreased |
| 45–59 | G3a – Mildly to moderately decreased |
| 30–44 | G3b – Moderately to severely decreased |
| 15–29 | G4 – Severely decreased |
| Below 15 | G5 – Kidney failure category |
An eGFR of 60 or above does not establish CKD unless another marker of kidney damage is present.
Chronic kidney disease generally requires abnormalities of kidney structure or function to persist for at least three months.
A single low eGFR may require earlier investigation to exclude acute kidney injury or another potentially serious problem.
Yes. Early diabetic kidney disease can occur even when serum creatinine remains within the laboratory reference range.
For example, a person may have relatively preserved kidney filtration while urine testing shows increased albumin leakage.
Other people may have reduced eGFR without increased albuminuria.
This is why eGFR and urine ACR are often assessed together.
Related Reading: Diabetes and Kidney Disease FAQs
Previous results help healthcare professionals assess trends rather than relying on a single measurement.
For example, a gradual decline in eGFR over several years may suggest a different pattern from a sudden rise in creatinine during an acute illness.
Changes may be related to chronic disease, dehydration, medicines, infection, urinary obstruction or other factors.
Comparing previous results can help determine whether further testing or closer monitoring is needed.
When available, retain reports showing:
Previous creatinine and eGFR values
Earlier urine ACR measurements
HbA1c trends
Blood pressure records
Relevant imaging findings
Previous hospital investigations
Do not delay medical assessment simply because an older report is unavailable.
According to the American Diabetes Association’s 2026 Standards of Care:
Type 2 diabetes: Assess urine ACR and eGFR at least annually from diagnosis.
Type 1 diabetes: Routine annual assessment generally begins after five years of diabetes.
Established chronic kidney disease: Urine ACR and eGFR may require monitoring approximately one to four times annually, depending on risk and disease stage.
More frequent testing may be appropriate in certain circumstances.
The schedule should be individualised according to kidney function, previous results, treatment changes and other clinical factors.
Additional evaluation may be appropriate when:
Urine ACR remains elevated.
eGFR is persistently reduced.
Kidney function is declining unexpectedly.
Creatinine rises rapidly.
Significant protein or blood is detected in urine.
Blood pressure remains difficult to control.
The cause of kidney abnormalities is uncertain.
Electrolyte abnormalities or other complications occur.
Some findings may require urgent assessment even without typical kidney-related symptoms.
A qualified healthcare professional can determine whether specialist evaluation is necessary.
A healthcare professional may ask about diabetes duration, blood glucose control, high blood pressure, other medical conditions, medicines and family history.
Questions may address swelling, changes in urination, fatigue, appetite and other concerns.
However, diabetic kidney disease may be present without noticeable symptoms.
Clinical assessment may include blood pressure measurement, evaluation for fluid retention and other relevant findings.
Creatinine, eGFR, urine ACR, HbA1c and previous investigations are reviewed together.
Repeat urine testing, blood tests, imaging or specialised investigations may be considered when clinically indicated.
Kidney biopsy is not routinely needed for every person with diabetic kidney disease.
The healthcare professional may discuss risk factors, monitoring requirements and appropriate management options.
Not every patient requires the same tests or treatments.
Preparing questions can help you understand medical reports and recommendations.
Useful questions include:
What do my creatinine and eGFR results indicate?
Is albumin present in my urine?
Have my kidney test results changed over time?
Could another condition be affecting my kidneys?
Do I need repeat blood or urine testing?
Are my current medicines appropriate for my kidney function?
What blood glucose and blood pressure targets are suitable for me?
Do I need dietary or fluid-intake changes?
How frequently should kidney function be monitored?
Which symptoms require urgent medical attention?
Answers depend on the individual’s medical condition and clinical findings.
Appropriate management may help reduce complications and slow kidney disease progression in some individuals.
Depending on the diagnosis, care may involve:
Blood Glucose Management
Individualised glucose targets may help reduce diabetes-related complications.
Blood Pressure Management
Appropriate blood pressure control is an important part of kidney and cardiovascular risk management.
Kidney-Protective Medicines
Selected patients may benefit from treatments such as ACE inhibitors, angiotensin receptor blockers, SGLT2 inhibitors or other medicines supported by clinical guidelines.
These treatments are not suitable for everyone and may require monitoring of kidney function, potassium and other factors.
Lifestyle and Nutrition
Physical activity, smoking cessation, suitable dietary sodium intake and individualised nutrition may form part of care.
Regular Monitoring
Follow-up blood and urine tests help assess kidney health and treatment-related changes.
There is no single treatment that guarantees recovery or prevents progression in every patient.
Do not start, stop or change prescribed medicines based on online information.
No. Protein requirements vary according to kidney disease stage, nutritional status and medical needs.
For many adults with non-dialysis CKD, a protein intake around 0.8 g/kg/day may be considered under professional guidance.
However, people receiving dialysis may require different amounts, and inappropriate restriction can cause nutritional problems.
Avoid self-prescribing a very low-protein diet.
Excessive water intake does not prevent every form of kidney damage.
Fluid requirements depend on hydration, kidney function, heart health, medicines and other medical conditions.
Some people with advanced kidney disease or heart failure may need fluid restrictions.
Follow individual medical advice rather than using a fixed water-intake target.
Seek urgent medical care for:
Very little or no urine, particularly when new
Severe breathlessness
Chest pain
Confusion or reduced consciousness
Rapidly worsening symptoms
Severe illness associated with sudden kidney function changes
Unexplained swelling, persistently abnormal kidney reports or urinary changes should also be evaluated, although they do not always indicate an emergency.
| Report or record | Why it may help |
|---|---|
| Serum Creatinine | Assesses a kidney filtration marker |
| eGFR | Estimates kidney filtration |
| Urine ACR | Measures albumin leakage |
| HbA1c | Reflects longer-term blood glucose |
| Blood Pressure Log | Helps evaluate blood pressure patterns |
| Electrolyte Results | Identifies relevant metabolic abnormalities |
| Medication List | Supports medicine safety review |
| Previous Kidney Reports | Helps identify trends |
| Imaging Reports | Provides information about structural abnormalities when relevant |
This checklist is for general education. It does not mean every test must be performed before medical evaluation.
Urine ACR and eGFR are two important screening tests. Serum creatinine is commonly used to calculate eGFR, while other investigations depend on individual clinical circumstances.
Yes. Early diabetic kidney disease often develops without obvious symptoms. Blood and urine tests may detect abnormalities before symptoms appear.
Yes. Increased urine albumin may occur while serum creatinine is still within the laboratory reference range.
A urine ACR of 30 mg/g or above is considered increased. Repeat testing may be necessary because temporary conditions can affect the result.
A reduced eGFR suggests lower estimated kidney filtration. Its significance depends on the actual value, previous results, duration and clinical context.
For most adults with type 2 diabetes, at least annual urine ACR and eGFR assessment is recommended. In type 1 diabetes, routine screening generally starts after five years. Established kidney disease may require more frequent monitoring.
HbA1c provides information about longer-term blood glucose, not kidney damage directly. Kidney function and albuminuria require additional testing.
No. Increased albuminuria indicates albumin leakage but does not establish kidney failure. Kidney function, medical history and other findings must be considered.
Understanding kidney function reports is an important part of diabetes-related kidney health assessment.
Serum creatinine, eGFR, urine ACR, HbA1c and blood pressure readings provide different types of information. Together with medical history and previous results, these investigations can help identify kidney abnormalities and guide appropriate monitoring.
Regular kidney screening and individualised medical management may help reduce complications and slow kidney disease progression in some people with diabetes.
Abnormal kidney test results should be interpreted by a qualified healthcare professional rather than used for self-diagnosis or independent treatment changes.
Disclaimer: Website content and visuals, including AI-generated illustrations, are provided for general informational, educational and representational purposes only. They do not replace personalised medical advice, diagnosis or clinical assessment.
For kidney-related concerns, consult a qualified medical practitioner or visit an appropriate healthcare facility. Seek immediate medical attention in an emergency.
Plot no 70, Moreshwar Heritage, Sector 5, Ulwe, Navi Mumbai, Maharashtra 410206
For Booking: +91 8591009591
Chat With Us
Mini Sea Shore Road, Juhu Nagar, Sector 10A, Vashi, Navi Mumbai, Maharashtra 400703
Chat With Us