
The urine albumin-to-creatinine ratio (urine ACR or uACR) test measures albumin relative to creatinine in a urine sample. It helps detect increased albumin leakage, which may be a marker of kidney damage even when serum creatinine and estimated glomerular filtration rate (eGFR) are relatively normal.
A urine ACR below 30 mg/g is classified as normal to mildly increased, 30–299 mg/g as moderately increased, and 300 mg/g or above as severely increased albuminuria.
However, a single high urine ACR result does not automatically confirm chronic kidney disease. Infection, fever, strenuous exercise and other medical conditions may temporarily affect urinary albumin levels.
This guide explains why urine ACR testing is performed, how samples are collected, what the results mean and when further evaluation may be necessary.
A urine ACR test measures two substances in urine:
Albumin: A protein normally found in the bloodstream that helps maintain fluid balance and performs other important functions.
Creatinine: A waste product formed through muscle metabolism and excreted through the kidneys.
The laboratory compares the amount of albumin with the amount of creatinine and reports the ratio.
The test is commonly expressed in milligrams of albumin per gram of creatinine (mg/g).
Because urine concentration changes throughout the day, using a ratio helps reduce the effect of urine dilution on the result.
Urine ACR provides information about albumin leakage, but it does not directly measure the kidneys’ overall filtering rate.
The kidneys contain microscopic filtering units called nephrons.
Within each nephron, a structure called the glomerulus filters blood, allowing waste products and excess fluid to pass into the forming urine while retaining most larger proteins.
The kidney tubules also help reabsorb certain filtered substances.
Healthy kidneys normally allow only small amounts of albumin to appear in urine.
When certain diseases affect kidney filtering structures, urinary albumin excretion may increase.
This condition is called albuminuria.
However, albuminuria can also occur temporarily during illness or other physiological changes.
Urine ACR helps identify abnormalities that may not be detected through serum creatinine alone.
Its clinical uses include:
Detecting increased albumin leakage.
Evaluating possible kidney damage.
Assessing kidney-related risk in people with diabetes.
Supporting the evaluation of hypertension-related kidney abnormalities.
Helping classify chronic kidney disease.
Monitoring changes in albuminuria over time.
Supporting assessment of kidney and cardiovascular risk.
Urine ACR is particularly useful when interpreted alongside eGFR.
An elevated urine ACR is a clinical finding, not a diagnosis of a particular kidney disease.
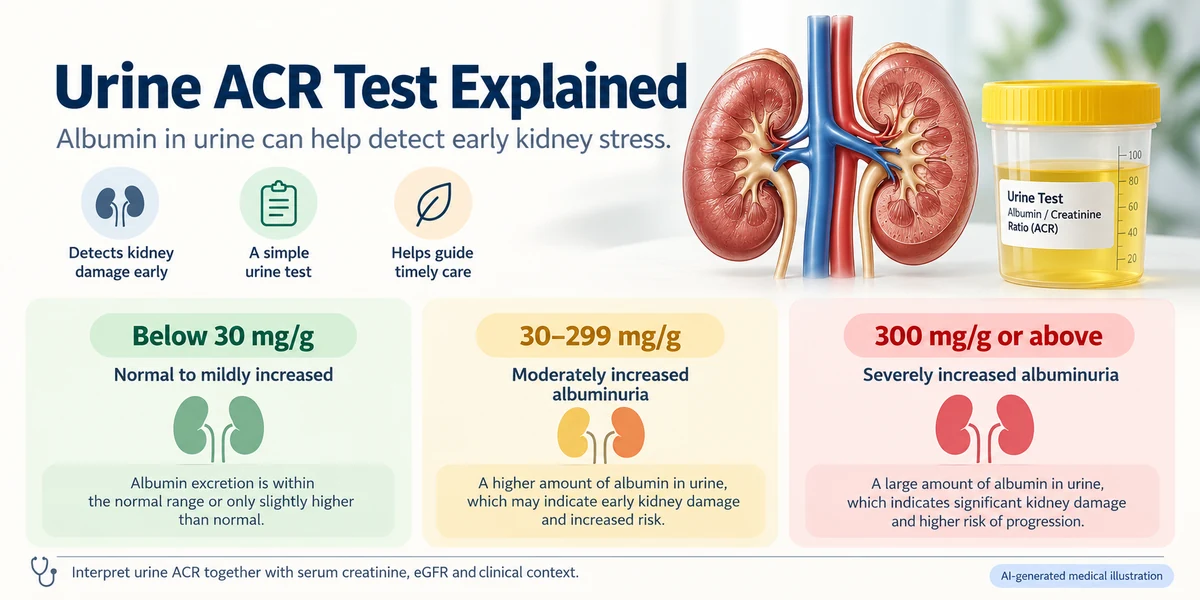
Urine ACR results are classified into three albuminuria categories.
| Urine ACR (mg/g) | Category | General interpretation |
|---|---|---|
| Below 30 | A1 | Normal to mildly increased |
| 30–299 | A2 | Moderately increased albuminuria |
| 300 or above | A3 | Severely increased albuminuria |
This category is described as normal to mildly increased albuminuria.
A result in this range is generally reassuring regarding albumin leakage, but it does not exclude all types of kidney disease.
Other abnormalities, including reduced eGFR, may still require evaluation.
This category indicates moderately increased albuminuria.
The older term microalbuminuria is sometimes used to describe this range.
Persistent albuminuria in this category may indicate kidney damage, particularly in people with diabetes or hypertension.
However, the underlying cause must be determined clinically.
This category indicates severely increased albuminuria.
It may be associated with a higher risk of kidney disease progression and cardiovascular complications.
Significant or persistent abnormalities may require additional investigations.
No.
A high urine ACR means that increased albumin has been detected in urine.
It does not independently determine the severity of kidney filtration impairment or establish that kidney failure is present.
eGFR, previous results, symptoms and other medical findings are needed for a broader assessment.
Albuminuria and proteinuria are related but different terms.
Albuminuria: Increased urinary excretion of albumin.
Proteinuria: Increased urinary excretion of protein, which may include albumin and other proteins.
Urine ACR measures albumin relative to creatinine.
Urine protein-to-creatinine ratio (PCR or UPCR) measures total protein relative to creatinine.
The choice of test depends on the suspected medical condition.
Some kidney disorders involve proteins other than albumin, so urine ACR alone may not identify every type of proteinuria.
Urine ACR usually requires a single urine specimen.
A urine sample is collected in a container provided by the laboratory.
Patients should follow the laboratory’s hygiene and collection instructions.
A clean-catch midstream sample may be requested when appropriate.
The laboratory measures urine albumin and urine creatinine.
The albumin-to-creatinine ratio is calculated.
A simplified formula is:
Urine ACR (mg/g) = Urine albumin (mg/dL) ÷ Urine creatinine (g/dL)
Both measurements must be expressed in compatible units.
The result is interpreted alongside previous measurements, serum creatinine, eGFR, medical history and other clinical findings.
A single test does not always establish a chronic condition.
A first-morning urine sample is often preferred, particularly when confirming an abnormal result.
It may reduce variation associated with daytime activity and changes in urine concentration.
However, a random spot urine sample is also commonly accepted for initial screening.
When urine ACR is elevated on a random sample, a first-morning specimen may be recommended for confirmation.
Usually not.
Spot urine ACR testing is commonly used for routine albuminuria assessment.
A 24-hour urine collection may be considered in selected circumstances when more detailed measurement is clinically necessary.
Fasting is not routinely required for urine ACR testing alone.
However, other blood or urine tests performed at the same time may have different preparation requirements.
Patients should follow the instructions provided by the laboratory or healthcare professional.
General considerations include:
Follow the laboratory’s urine collection instructions.
Mention recent fever or infection.
Inform the healthcare professional about menstruation or possible sample contamination.
Report recent strenuous physical activity.
Share relevant medication and supplement information.
Follow any specific instructions regarding sample delivery and storage.
Do not stop prescribed medicines or deliberately alter fluid intake without medical advice.

Increased urine albumin can be associated with several medical conditions.
Long-term elevated blood glucose can affect the kidneys’ small blood vessels and filtering structures.
In some people, albuminuria develops before a substantial reduction in eGFR.
However, not everyone with diabetes develops albuminuria, and not every abnormal kidney result in a person with diabetes is caused by diabetes.
Read more about Diabetic Kidney Disease Symptoms.
Persistent hypertension can damage small blood vessels in the kidneys.
Albuminuria and hypertension may occur together.
High blood pressure also contributes to cardiovascular risk.
Conditions involving injury or inflammation of the glomeruli may cause increased urinary albumin.
Examples include IgA nephropathy, membranous nephropathy and some other glomerular disorders.
Persistent albuminuria is one possible marker of CKD.
However, CKD can also be present without increased albumin excretion.
The diagnosis depends on the duration and significance of kidney abnormalities.
An elevated urine ACR may occur during fever, infection, strenuous exercise, markedly elevated blood glucose, significantly elevated blood pressure or other acute conditions.
These possibilities should be assessed before concluding that albuminuria is persistent.
Yes.
Urinary albumin excretion varies between measurements.
Factors that may influence the result include:
Fever or acute illness.
Urinary tract infection.
Strenuous physical activity.
Menstruation or urine sample contamination.
Markedly elevated blood glucose.
Markedly elevated blood pressure.
Certain episodes of heart failure or other acute illness.
Urine ACR helps account for differences in urine concentration, but it does not eliminate every source of biological or laboratory variation.
An abnormal result should not automatically be dismissed, even when a temporary cause is suspected.
Repeat testing may be appropriate.
Repeat testing is often necessary because urine albumin varies naturally and can be affected by temporary conditions.
KDIGO guidance recommends confirming a urine ACR of 30 mg/g or above found on a random specimen using a subsequent first-morning urine sample when feasible.
Additional measurements may be appropriate to establish persistence.
The timing depends on the clinical situation.
No.
Chronic kidney disease generally requires abnormalities of kidney structure or function persisting for at least three months and having implications for health.
Persistent albuminuria can be one of those abnormalities.
A single elevated ACR result may reflect a temporary condition or an underlying kidney disorder.
Previous laboratory results, repeat measurements and clinical evaluation are important.
Yes.
Serum creatinine is used to estimate kidney filtration.
Urine ACR measures albumin leakage.
These are different aspects of kidney health.
Some people have increased urine albumin while serum creatinine remains within the laboratory reference range.
A person may also have relatively preserved eGFR with persistent albuminuria.
This pattern may indicate kidney damage, but the cause and duration must be established.
For a related explanation, read Diabetic Kidney Disease With Normal Creatinine.
Urine ACR and eGFR provide complementary information.
| Test | What it evaluates | Main purpose |
|---|---|---|
| Urine ACR | Albumin leakage in urine | Helps identify kidney damage |
| Serum creatinine | Creatinine concentration in blood | Used to estimate kidney filtration |
| eGFR | Estimated kidney filtering function | Helps assess reduced filtration |
| Urinalysis | Blood, protein and other urine findings | Helps evaluate additional abnormalities |
| Urine PCR | Total protein relative to creatinine | Helps assess proteinuria when indicated |
This may indicate kidney damage despite preserved filtration.
However, a single abnormal ACR does not establish CKD.
This may indicate reduced kidney filtration without increased albumin leakage.
Further evaluation depends on the duration and cause.
Both albumin leakage and reduced filtration may be present.
The combination can be important for kidney risk assessment.
These results may be reassuring, but they do not exclude every type of kidney disorder.
Additional assessment may be appropriate when clinical concerns exist.
Learn more about Kidney Tests Explained.
Urine ACR testing is particularly useful for individuals at risk of kidney disease.
Relevant circumstances include:
Diabetes.
Hypertension.
Known chronic kidney disease.
Previously elevated urine albumin.
Other medical conditions associated with kidney damage.
Clinical findings suggesting a kidney filtering disorder.
The need for screening depends on age, medical history, risk factors and previous test results.
Urine ACR is not necessarily required at the same frequency for everyone.
General diabetes screening recommendations distinguish type 1 and type 2 diabetes.
For many adults with type 1 diabetes, annual urine ACR and eGFR testing is generally recommended once diabetes has been present for five years or longer.
Earlier evaluation may be appropriate when additional risk factors or kidney abnormalities are present.
For adults with type 2 diabetes, urine ACR and eGFR are generally checked at least annually beginning at diagnosis.
Testing may be required more frequently, depending on kidney function, urine albumin levels, disease progression and other clinical circumstances.
Children and adolescents require age-appropriate guidance.
Albuminuria may decrease when its underlying cause is appropriately managed.
The treatment approach varies according to diagnosis, kidney function and associated medical conditions.
Appropriate blood pressure control can help reduce kidney and cardiovascular risk.
ACE inhibitors or angiotensin receptor blockers (ARBs) may be suitable for selected patients.
These medicines have potential adverse effects and may require kidney function and potassium monitoring.
Blood glucose management is important for people with diabetes-related kidney abnormalities.
Individual glucose targets depend on diabetes type, age, other medical conditions and treatment risks.
Certain medicines, including SGLT2 inhibitors, may provide kidney benefits in eligible patients.
Treatment decisions depend on eGFR, diabetes type, albuminuria, cardiovascular risk and other clinical factors.
Individualised care may include:
Reducing excessive sodium intake.
Avoiding tobacco.
Appropriate physical activity.
Weight management when indicated.
Reviewing medicines and supplements.
Following dietary recommendations suited to the clinical condition.
A low-protein diet is not automatically appropriate for everyone with elevated urine ACR.
Dietary restrictions should be individualised.
No medicine, supplement, diet or lifestyle measure guarantees complete reversal of kidney damage.
Sometimes.
Temporary albuminuria may resolve when a contributing illness or condition improves.
Persistent albuminuria may also decrease with treatment of an underlying medical disorder.
However, a normal or improved urine ACR result does not necessarily prove that chronic kidney damage has completely reversed.
Ongoing assessment may be needed according to the underlying diagnosis.
Increased urine albumin is associated with higher cardiovascular risk in some populations, particularly people with diabetes or CKD.
However, an elevated urine ACR does not diagnose heart disease or predict that a particular person will experience a cardiovascular event.
A broader assessment considers blood pressure, diabetes, cholesterol, smoking status, kidney function and other factors.
Additional medical evaluation may be appropriate when:
Urine ACR remains elevated on repeat testing.
Albuminuria is significantly increased or rises rapidly.
eGFR declines.
Blood and protein are detected together in urine.
Blood pressure is persistently elevated.
Significant swelling develops.
Other findings suggest glomerular disease.
The underlying cause remains uncertain.
Not everyone with a mildly elevated urine ACR requires immediate nephrology referral.
The need for specialist assessment depends on persistence, severity, clinical findings and other kidney-related risks.
Seek emergency medical care for:
Severe breathlessness.
Chest pain.
Confusion or loss of consciousness.
Seizures.
Very little or no urine output accompanied by significant illness.
Rapidly worsening swelling with breathing difficulty.
Significant new swelling, visible blood in urine, severe flank pain with fever or rapidly changing kidney function also requires timely medical assessment.
These symptoms have multiple possible causes and should not automatically be attributed to albuminuria.
| Information | Why it may be useful |
|---|---|
| Latest urine ACR | Shows the current albuminuria category |
| Previous ACR results | Helps assess persistence and changes |
| Serum creatinine | Supports kidney filtration assessment |
| eGFR | Estimates overall kidney filtration |
| Blood pressure records | Helps assess hypertension |
| HbA1c or blood glucose results | May be relevant in diabetes |
| Urinalysis | Helps identify other urine abnormalities |
| Recent illness or exercise | May identify temporary influences |
| Current medication list | Supports medication review |
| Other medical history | Helps identify possible underlying causes |
Not all investigations are required for every patient. Testing should be selected according to clinical findings.
A urine ACR test compares the amount of albumin with creatinine in urine. It helps identify increased albumin leakage that may be associated with kidney damage.
A urine ACR below 30 mg/g is classified as normal to mildly increased. Results must still be interpreted alongside kidney function and medical history.
A high urine ACR indicates increased urinary albumin. It may be associated with kidney damage, but temporary factors and other medical conditions can also affect the result.
Yes. Increased urine albumin may be detected even when serum creatinine is within the laboratory reference range.
Fasting is not routinely required for urine ACR alone. Follow laboratory instructions if other investigations are being performed.
Yes. Fever, infection, intense exercise and other factors can temporarily influence urinary albumin. Repeat testing may be required
Urine ACR provides a quantitative measurement of albumin relative to creatinine and can detect lower levels of albumin than many routine protein dipsticks. Both tests have different clinical uses.
Urine albumin levels may improve with appropriate medical management. However, established chronic kidney damage may not be fully reversible.
The urine ACR test is an important investigation for detecting and monitoring increased urinary albumin.
It may identify kidney abnormalities even when serum creatinine and eGFR are relatively preserved.
However, a single high urine ACR result does not automatically establish chronic kidney disease or identify its underlying cause.
Repeat testing, eGFR, previous results and clinical assessment help determine whether albuminuria is persistent and clinically significant.
Appropriate testing and individualised medical management can help guide kidney-health decisions.
Medical Information: Dr. Jyoti Bansode | MBBS, MD Medicine, DM Nephrology | Medical Registration No.: 2011/06/1863 | Maharashtra Medical Council (MMC).
Medical Disclaimer: Website content and visuals are for general informational, educational and representational purposes only, may not reflect individual patient conditions or outcomes, and do not replace personalised medical advice, diagnosis or clinical assessment.
Plot no 70, Moreshwar Heritage, Sector 5, Ulwe, Navi Mumbai, Maharashtra 410206
For Booking: +91 8591009591
Chat With Us
Mini Sea Shore Road, Juhu Nagar, Sector 10A, Vashi, Navi Mumbai, Maharashtra 400703
Chat With Us