+91 8691888178 / 8850999397 dr.jyotibansode.01@gmail.com Monday to Saturday : 05:00PM TO 06:00PM

Diabetes Kidney Disease FAQ: Creatinine, eGFR, ACR & Swelling

Diabetes can affect kidney health even before symptoms appear. Long-term elevated blood glucose may damage the kidneys’ small blood vessels and filtering structures, resulting in albumin leakage, reduced kidney filtration or both. Two important tests used to assess kidney health in people with diabetes are the urine albumin-to-creatinine ratio (uACR) and estimated glomerular filtration rate (eGFR). A person may have normal serum creatinine but still have evidence of kidney damage. Conversely, some people have reduced kidney filtration without increased urine albumin. This frequently asked questions guide explains how diabetes affects the kidneys, how to interpret common laboratory findings, what symptoms may occur and when further medical assessment may be necessary. Understanding Diabetes and Kidney Health 1. How does diabetes affect the kidneys? Persistently elevated blood glucose can damage the kidneys’ small blood vessels and filtering structures, called glomeruli. Over time, some people develop increased albumin in urine, reduced kidney filtration or other kidney abnormalities. High blood pressure may further contribute to kidney-related damage. However, not everyone with diabetes develops kidney disease, and the extent of damage varies between individuals. 2. What is diabetic kidney disease? Diabetic kidney disease (DKD) refers to kidney damage associated with diabetes. It may involve persistent albuminuria, reduced eGFR or both. The term diabetic nephropathy is also used, particularly when describing characteristic kidney changes associated with diabetes. Not every kidney abnormality in someone with diabetes is necessarily caused by diabetes. Other kidney disorders may require consideration. 3. Can diabetes cause kidney damage without symptoms? Yes. Early diabetic kidney disease frequently causes no noticeable symptoms. A person may feel well while urine ACR is elevated or kidney filtration has started to decline. Regular blood and urine testing can help identify abnormalities before noticeable symptoms develop. 4. Will everyone with diabetes eventually develop kidney failure? No. Diabetes increases the risk of chronic kidney disease, but not everyone with diabetes develops serious kidney problems. The risk depends on factors including blood glucose management, blood pressure, diabetes duration, cardiovascular health and other medical conditions. Appropriate monitoring and treatment may reduce the likelihood of kidney disease progression, but outcomes cannot be guaranteed. Creatinine and Kidney Function Questions 5. What does a serum creatinine test measure? Serum creatinine measures the concentration of creatinine in blood. Creatinine is a waste product formed during normal muscle metabolism. The kidneys remove creatinine from the bloodstream, so its measurement can help assess kidney filtration. However, the result is also influenced by muscle mass, diet, certain medicines and other factors. 6. Can diabetic kidney disease occur with normal creatinine? Yes. Early kidney abnormalities may occur while serum creatinine remains within the laboratory reference range. For example, increased urine albumin may be detected before a substantial decrease in kidney filtration develops. Serum creatinine alone cannot identify every form of kidney damage. Urine ACR and eGFR provide complementary information. Read more about Diabetic Kidney Disease With Normal Creatinine. 7. Does high creatinine always mean kidney failure? No. An elevated creatinine result may indicate reduced kidney filtration, but it does not automatically mean kidney failure. Possible contributing factors include acute kidney injury, chronic kidney disease, dehydration, certain medicines and other medical conditions. Previous measurements, eGFR, urine findings and clinical assessment help determine the significance. 8. What is eGFR? The estimated glomerular filtration rate (eGFR) is an estimate of how well the kidneys filter blood. It is commonly calculated using serum creatinine together with age and sex. eGFR is usually reported in mL/min/1.73 m². It provides a more useful estimate of kidney filtration than interpreting serum creatinine alone in many clinical situations. 9. What is the difference between serum creatinine and eGFR? Serum creatinine is a measured blood concentration. eGFR is a calculated estimate of kidney filtering function, commonly derived from serum creatinine and other relevant factors. A normal laboratory creatinine result does not always mean that eGFR is normal. Both measurements should be interpreted in the context of previous results and clinical findings. 10. Can eGFR be normal when kidney damage is present? Yes. Some people have an eGFR of 90 mL/min/1.73 m² or above while urine testing shows persistent albuminuria. When albuminuria or another marker of kidney damage persists, chronic kidney disease may be present even with relatively preserved filtration. However, one abnormal urine result does not automatically establish CKD. 11. What do the different eGFR categories mean? The commonly used KDIGO GFR categories are: eGFR (mL/min/1.73 m²) Category Description 90 or above G1 Normal or high 60–89 G2 Mildly decreased 45–59 G3a Mildly to moderately decreased 30–44 G3b Moderately to severely decreased 15–29 G4 Severely decreased Below 15 G5 Kidney failure range G1 and G2 alone do not establish chronic kidney disease without other evidence of kidney damage. CKD generally requires abnormalities persisting for at least three months. A single eGFR result should not be interpreted without considering the clinical situation. Urine ACR and Albuminuria Questions 12. What is a urine ACR test? The urine albumin-to-creatinine ratio (uACR) measures albumin relative to creatinine in a urine sample. Albumin is a blood protein that may appear in increased amounts in urine when the kidneys’ filtering structures are affected. Urine ACR helps detect albumin leakage that may not be identified through serum creatinine alone. A single spot urine sample is commonly used. 13. What is the normal urine ACR range? Urine ACR results are classified into three categories: Urine ACR (mg/g) Category Interpretation Below 30 A1 Normal to mildly increased 30–299 A2 Moderately increased albuminuria 300 or above A3 Severely increased albuminuria The older term microalbuminuria generally refers to the A2 category. These categories describe albumin excretion rather than the exact cause of kidney disease. For further information, read Urine ACR Test Explained. 14. What does a high urine ACR mean? A high urine ACR indicates increased albumin in urine. Persistent albuminuria may be a marker of kidney damage and is associated with increased kidney and cardiovascular risk. However, a single elevated result may be temporary. The underlying cause and clinical significance require assessment. 15. Can a high urine
Diabetic Kidney Care: Essential Tests, Reports & Kidney Health Checklist

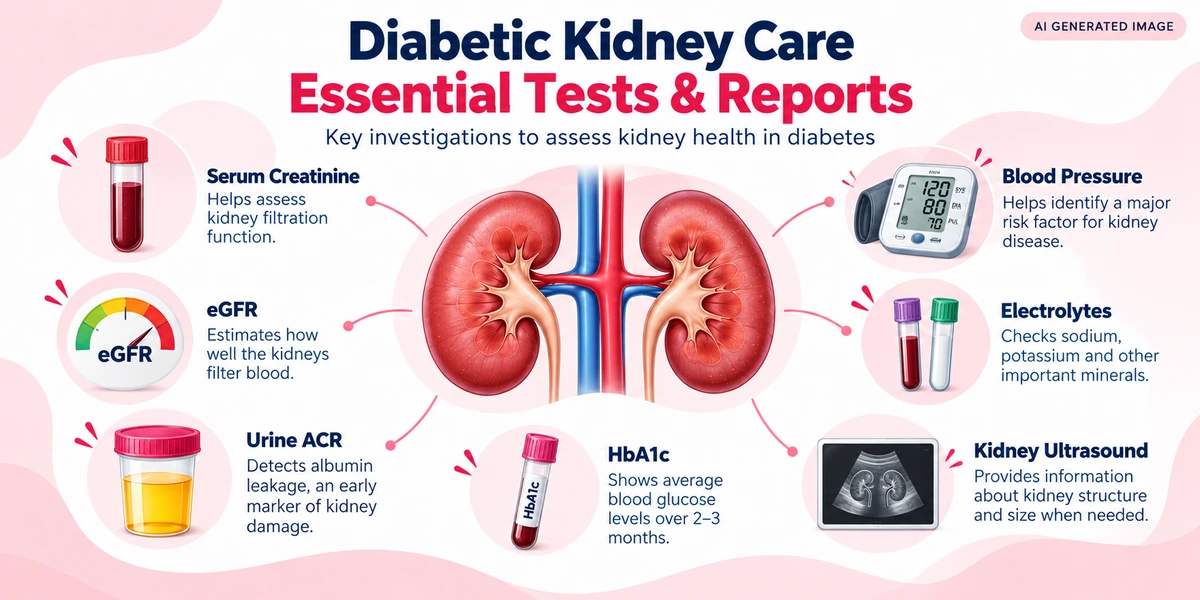
People with diabetes may develop kidney abnormalities even when they have no noticeable symptoms. Blood and urine investigations, particularly serum creatinine, estimated glomerular filtration rate (eGFR) and urine albumin-to-creatinine ratio (ACR), help assess kidney function and identify possible kidney damage. Keeping previous kidney test reports, HbA1c results, blood pressure records and medication details can help healthcare professionals understand changes in kidney health over time. Not everyone needs every investigation before a kidney consultation. Test selection depends on individual medical history, symptoms and clinical findings. What Is Diabetic Kidney Disease? Diabetic kidney disease (DKD) refers to kidney damage associated with diabetes. Over time, persistently elevated blood glucose can affect the small blood vessels and filtering structures inside the kidneys, known as glomeruli. These changes may lead to increased albumin in urine, reduced kidney filtration or both. Diabetic kidney disease is one of the important causes of chronic kidney disease (CKD). However, kidney abnormalities in a person with diabetes are not always caused by diabetes itself. Other kidney conditions, medicines, infections or medical problems may also affect kidney function. Related Reading: Diabetes and Kidney Diseases Why Are Regular Kidney Tests Important in Diabetes? Early diabetic kidney disease often develops without obvious symptoms. A person may feel well while urine tests show increased albumin or blood tests reveal changes in kidney filtration. Regular kidney assessment can help healthcare professionals: Identify albumin leakage into urine. Monitor kidney filtration. Assess changes in kidney function over time. Evaluate complications associated with diabetes and hypertension. Review the suitability and safety of certain medicines. Determine whether further investigations are necessary. Kidney tests help guide medical decisions, but no single result provides a complete picture of kidney health. What Reports Are Important for Diabetic Kidney Care? The following reports may be useful when assessing kidney health in someone with diabetes. 1. Serum Creatinine Serum creatinine is a blood test measuring creatinine, a waste product produced during normal muscle metabolism. The kidneys normally remove creatinine from the bloodstream. Higher-than-expected creatinine may suggest reduced kidney filtration, but results can also be affected by muscle mass, diet, certain medicines and other factors. A single creatinine result does not automatically establish chronic kidney disease. Previous reports may help determine whether creatinine is stable, rising or improving. Related Reading: What Causes High Creatinine? 2. Estimated Glomerular Filtration Rate (eGFR) Estimated glomerular filtration rate helps estimate how well the kidneys filter blood. It is commonly calculated using serum creatinine, age and sex. Some clinical situations may require additional testing, such as cystatin C, to improve estimation accuracy. eGFR values are generally reported in mL/min/1.73 m². A persistently reduced eGFR may indicate chronic kidney disease, but temporary illness, acute kidney injury and other factors can affect the result. Doctors consider eGFR together with urine findings and previous reports. 3. Urine Albumin-to-Creatinine Ratio (ACR) Urine ACR measures the amount of albumin relative to creatinine in a urine sample. Albumin is a protein normally retained mainly in the bloodstream. Increased albumin in urine may indicate damage to the kidneys’ filtering structures. Urine ACR is particularly useful in diabetes because albumin leakage can appear before a significant decrease in kidney filtration. However, not everyone with diabetic kidney disease develops increased albuminuria. Related Reading: Urine ACR Test Explained 4. HbA1c Test HbA1c reflects average blood glucose levels over approximately the previous two to three months. It helps assess longer-term diabetes management. Persistently elevated blood glucose can contribute to kidney damage over time. However, HbA1c may be less reliable in certain circumstances, including advanced chronic kidney disease, anaemia, altered red blood cell turnover and some medical treatments. Doctors may use additional glucose measurements when appropriate. Blood glucose targets should be individualised. 5. Blood Pressure Records Blood pressure monitoring is important because diabetes and hypertension can both contribute to kidney disease. High blood pressure may worsen existing kidney damage, while kidney disease can also make blood pressure more difficult to control. Available home and clinic blood pressure readings can provide useful information. The frequency of home monitoring and appropriate blood pressure targets depend on the individual’s medical condition. 6. Blood Electrolyte Tests The kidneys help regulate electrolytes and maintain fluid and acid-base balance. Blood tests may assess:  – Potassium  – Sodium  – Bicarbonate  – Calcium  – Phosphate, when indicated Electrolyte abnormalities may occur in kidney disease or as a result of certain medicines. Not every person requires every electrolyte test at each assessment. 7. Lipid Profile A lipid profile measures substances such as LDL cholesterol, HDL cholesterol and triglycerides. People with diabetes and kidney disease may have an increased risk of cardiovascular complications. Lipid testing may form part of broader cardiovascular risk assessment. It is not a direct measure of kidney filtration. 8. Urinalysis A routine urine examination may help detect:  – Protein  – Blood  – Infection-related changes  – Glucose  – Other urine abnormalities Urinalysis complements, but does not replace, quantitative urine ACR testing when assessing albuminuria. 9. Kidney Ultrasound and Imaging Kidney ultrasound may provide information about kidney structure, size and possible urinary obstruction. It may be considered when there are unexpected kidney abnormalities, suspected structural problems or other clinical indications. A kidney ultrasound is not routinely necessary before every diabetes-related kidney assessment. Quick Comparison of Essential Diabetic Kidney Tests Test What it measures Why it may be useful Serum Creatinine Creatinine concentration in blood Helps assess kidney filtration eGFR Estimated kidney filtering function Helps evaluate and monitor kidney function Urine ACR Albumin relative to creatinine in urine Helps identify albumin leakage HbA1c Average glucose over approximately 2–3 months Helps assess diabetes management Blood Pressure Pressure inside blood vessels Helps identify a major kidney disease risk factor Electrolytes Potassium, sodium and related substances Helps detect metabolic abnormalities Lipid Profile Cholesterol and triglycerides Supports cardiovascular risk assessment Urinalysis Blood, protein and other urine findings Helps investigate urinary abnormalities Important: These investigations provide different information. Their results must be interpreted together with medical history and clinical findings. What Is the Normal Urine ACR Range in Diabetes? Urine ACR results are generally classified

When Should a Person With Diabetes See a Kidney Specialist in Navi Mumbai?

A person with diabetes may need evaluation by a kidney specialist (nephrologist) when urine albumin remains elevated, kidney filtration declines, creatinine changes unexpectedly, blood pressure is difficult to control or the cause of abnormal kidney tests is uncertain. Diabetes can damage the kidneys gradually, often without noticeable symptoms. However, not every abnormal kidney test requires immediate specialist referral, and not every kidney problem in someone with diabetes is caused by diabetes. Regular assessment using the urine albumin-to-creatinine ratio (uACR) and estimated glomerular filtration rate (eGFR) helps detect kidney abnormalities and identify individuals who may benefit from additional investigations. This article explains when nephrology assessment may be appropriate, which test results matter, how kidney disease is evaluated and what symptoms require urgent medical attention. How Does Diabetes Affect Kidney Function? The kidneys contain millions of microscopic filtering units called nephrons. Within each nephron, the glomerulus helps filter waste products and excess fluid from the bloodstream while retaining most essential proteins. Over time, elevated blood glucose can damage small blood vessels and affect these filtering structures. Possible consequences include: Increased albumin leakage into urine. Changes in the kidney’s filtering ability. Reduced eGFR in some individuals. Fluid and electrolyte disturbances as kidney dysfunction advances. Development or progression of chronic kidney disease (CKD). High blood pressure can further contribute to kidney damage. Kidney disease associated with diabetes is commonly called diabetic kidney disease (DKD). However, some people with diabetes develop kidney abnormalities from other causes, including glomerular diseases, urinary obstruction or medication-related kidney injury. For more information, read Diabetic Kidney Disease Symptoms. Why Is Regular Kidney Screening Important in Diabetes? Early diabetic kidney disease often has no noticeable symptoms. A person may have: Normal-looking urine. No swelling or pain. No obvious change in urination. Serum creatinine within the laboratory reference range. Relatively preserved eGFR. Despite this, urine testing may reveal increased albumin. Other people may develop reduced filtration without increased urine albumin. Therefore, urine ACR and eGFR provide complementary information about kidney health. Blood pressure, diabetes history, previous reports and other clinical findings also contribute to assessment. When Should a Person With Diabetes See a Nephrologist? Nephrology evaluation may be appropriate when kidney abnormalities are significant, progressive, difficult to explain or associated with complications. 1. Persistent or Rapidly Increasing Albuminuria Albumin is a protein normally retained in the bloodstream. An increased urine ACR indicates that more albumin than expected is being detected in urine. Persistent albuminuria may indicate kidney damage, even when eGFR remains relatively preserved. However, one elevated result does not automatically mean diabetic kidney disease is present. Repeat testing may be necessary because urinary albumin can temporarily increase during fever, infection, strenuous exercise or other medical conditions. Nephrology evaluation may be particularly relevant when albuminuria is severely increased, rises rapidly or remains unexplained. 2. Progressive Decline in eGFR eGFR estimates how effectively the kidneys filter blood. A sustained decline may indicate worsening kidney function. The rate of change, previous results, accompanying urine findings and other medical factors are important. A single slightly reduced eGFR does not automatically require immediate specialist referral. However, a progressive or unexplained decline may warrant nephrology assessment. 3. Unexpected Changes in Serum Creatinine Serum creatinine is a blood marker used to estimate kidney filtration. An elevated result may occur with acute kidney injury, chronic kidney disease, dehydration, certain medicines or other medical conditions. An unexpected rise should be assessed according to its degree, timing and associated symptoms. Rapid changes may require urgent clinical assessment rather than routine follow-up. 4. Difficult-to-Control High Blood Pressure Hypertension can contribute to kidney damage and may also develop or worsen because of kidney disease. Specialist evaluation may be appropriate when blood pressure remains difficult to control despite an appropriately assessed treatment plan, particularly when kidney abnormalities are present. Individual blood pressure targets depend on medical history, treatment tolerance and other clinical circumstances. 5. Blood and Protein Detected Together in Urine Proteinuria accompanied by hematuria (blood in urine) can sometimes suggest a glomerular disorder. Additional investigation may be needed, especially when urine microscopy shows concerning findings or kidney function is declining. Blood in urine may also have causes outside the kidneys, so evaluation should consider possible urinary tract conditions. 6. Significant Electrolyte Abnormalities Reduced kidney function can affect the balance of potassium, sodium and bicarbonate. Certain treatments can also influence these measurements. Significant abnormalities, especially elevated potassium or acid–base disturbances, may require specialist assessment. Severe electrolyte disturbances can be medical emergencies. 7. Suspected Advanced Chronic Kidney Disease People with advanced CKD may benefit from nephrology assessment for complications, medication review, disease monitoring and discussion of possible future treatment needs. An eGFR below 30 mL/min/1.73 m² is a commonly recognised reason to consider nephrology referral, although referral may be appropriate at higher eGFR levels depending on the clinical situation. 8. Uncertainty About the Cause of Kidney Disease Diabetes is an important cause of CKD, but it is not the only cause. Another diagnosis may be considered when there is: Sudden deterioration in kidney function. Rapidly increasing proteinuria. Blood in urine with concerning microscopic findings. Nephrotic syndrome. Other findings suggesting immune-mediated or structural kidney disease. Kidney abnormalities that do not fit the expected clinical pattern. Further blood tests, imaging or occasionally kidney biopsy may be considered when clinically indicated. Which Kidney Tests Matter in People With Diabetes? Kidney function evaluation commonly combines blood tests, urine investigations and blood pressure assessment. Test What it measures Why it matters Serum creatinine Creatinine concentration in blood Helps estimate kidney filtration eGFR Estimated kidney filtering function Helps identify reduced filtration Urine ACR Albumin relative to creatinine in urine Helps detect albumin leakage Urinalysis Blood, protein and other urine findings Helps identify additional abnormalities HbA1c Average blood glucose over approximately 2–3 months Supports diabetes management Blood pressure Pressure within the arteries Helps evaluate hypertension-related risks Electrolytes Potassium, sodium and bicarbonate concentrations May identify kidney-related complications Not every patient requires all these tests at the same frequency. Testing should be based on individual medical circumstances. Read more about Kidney Tests Explained.

Rising Creatinine in Diabetes: What It Means and What to Do

Rising creatinine in a person with diabetes may indicate a change in kidney filtration, but it does not automatically mean permanent kidney damage or kidney failure. Possible causes include acute kidney injury, dehydration, long-term diabetic kidney disease, high blood pressure, urinary obstruction and certain medication effects. Serum creatinine is a waste product measured in blood. Its concentration is influenced by kidney function as well as muscle mass, diet and other factors. An unexpected increase should be interpreted alongside previous creatinine results, estimated glomerular filtration rate (eGFR), urine albumin-to-creatinine ratio (uACR), medical history and symptoms. The size and speed of the creatinine change can be more important than one isolated value. This article explains why creatinine may rise in diabetes, how kidney tests are interpreted, which conditions require assessment and what symptoms should prompt urgent medical care. What Is Creatinine and Why Is It Important? Creatinine is a waste product produced through normal muscle metabolism. The kidneys remove creatinine from the bloodstream, primarily through filtration, and it is then excreted in urine. Serum creatinine testing helps assess kidney function, but it does not directly measure the amount of kidney damage. Its interpretation depends on factors including:  – Age and body composition.  – Muscle mass.  – Recent strenuous exercise.  – Recent meat consumption.  – Certain medicines and supplements.  –  Kidney filtration.  – Changes in hydration and circulation. A creatinine result within the laboratory reference range does not always exclude kidney disease. Similarly, an elevated result does not independently establish the cause or permanence of kidney dysfunction. How Does Diabetes Affect Kidney Function? Diabetes may affect the kidneys’ small blood vessels and filtering structures over time. Within each kidney, microscopic structures called glomeruli help filter blood while retaining most essential proteins. Persistently elevated blood glucose can contribute to structural and functional changes in these filtering units. Possible consequences include:  – Increased urinary albumin.  – Changes in glomerular filtration.  – Gradual reduction in eGFR.  – Increased kidney-related and cardiovascular risk.  – Development of chronic kidney disease in some individuals. This condition is commonly described as diabetic kidney disease. However, not every person with diabetes develops kidney disease. Importantly, not every rise in creatinine in someone with diabetes is caused by diabetic kidney disease. Read more about Diabetic Kidney Disease Symptoms. What Are the Common Causes of Rising Creatinine in Diabetes? A rising creatinine level can have several possible explanations. 1. Diabetic Kidney Disease Long-term diabetes may contribute to kidney damage and declining filtration. In some individuals, urine albumin increases before eGFR declines. Others experience reduced kidney filtration without significantly increased albuminuria. Diabetic kidney disease often develops gradually, but changes in kidney function should not automatically be attributed to diabetes without considering other causes. 2. Dehydration or Reduced Circulating Fluid Volume Fluid loss from vomiting, diarrhoea, fever or other causes may reduce blood flow to the kidneys. Significant dehydration can contribute to acute kidney injury and increased serum creatinine. People with markedly elevated blood glucose may lose additional fluid through increased urination. However, drinking large amounts of water is not an appropriate treatment for every cause of high creatinine. Fluid management depends on the underlying medical condition. 3. Acute Kidney Injury Acute kidney injury (AKI) involves a relatively sudden deterioration in kidney function. Possible triggers include:  – Severe infection or sepsis.  – Significant dehydration.  – Reduced blood pressure or circulation.  – Certain medicines.  – Urinary tract obstruction.  – Other acute medical conditions. AKI may develop in someone who previously had normal kidney function or in someone with established CKD. An abrupt rise in creatinine warrants timely medical assessment. 4. High Blood Pressure Persistently elevated blood pressure can contribute to kidney blood vessel injury. Diabetes and hypertension may occur together, increasing the importance of kidney and cardiovascular risk assessment. Kidney dysfunction can also make blood pressure more difficult to manage. 5. Medication-Related Changes Certain medicines may affect serum creatinine or kidney function. Examples include:  – Non-steroidal anti-inflammatory drugs (NSAIDs).  – Some antibiotics and other medicines with potential kidney toxicity.  – Medicines that affect kidney blood flow.  – Certain medicines that alter creatinine secretion without necessarily reducing filtration. ACE inhibitors and angiotensin receptor blockers (ARBs) may cause a modest creatinine rise after initiation because they change pressure within the glomeruli. This does not automatically mean the medicine is causing harmful kidney injury. Such treatments may provide kidney benefits in eligible patients. The significance of a creatinine change depends on its magnitude, timing, potassium level, fluid status and other clinical findings. Never stop or change prescribed medicines independently because of a creatinine result. 6. Urinary Tract Obstruction A blockage affecting urine drainage can impair kidney function. Possible causes include:  – Certain urinary stones.  – Prostate enlargement.  – Urinary tract narrowing.  – Other structural conditions. Additional investigations, including ultrasound, may be appropriate when obstruction is suspected. 7. Strenuous Exercise, Diet and Supplements Recent intense exercise, muscle injury, cooked meat consumption or creatine supplements may influence serum creatinine. These factors do not always indicate kidney damage. However, severe muscle injury can itself cause acute kidney injury, so symptoms and associated findings remain important. Does Rising Creatinine Always Mean Kidney Failure? No. An increase in creatinine may indicate reduced filtration, but it does not automatically mean kidney failure. Creatinine may increase because of temporary conditions, acute kidney injury, chronic kidney disease or non-kidney factors. Kidney failure is assessed using kidney function, symptoms, complications and other findings. One creatinine number alone cannot establish whether dialysis is needed. Is a Sudden Rise in Creatinine Different From a Gradual Rise? Yes. The timing of a change provides important diagnostic information. Feature Sudden Creatinine Rise Gradual Creatinine Rise Pattern Develops over hours or days. Develops over months or years. Possible Causes Acute kidney injury (AKI), severe illness, dehydration, obstruction or medicine-related changes. CKD progression or other longer-term conditions. Importance of Previous Tests Helps identify an acute change. Helps determine trends and chronicity. Evaluation May require urgent assessment. Depends on rate of progression and associated findings. Possible Outcome May improve if a reversible cause is

How to Slow Diabetic Kidney Disease Progression Effectively

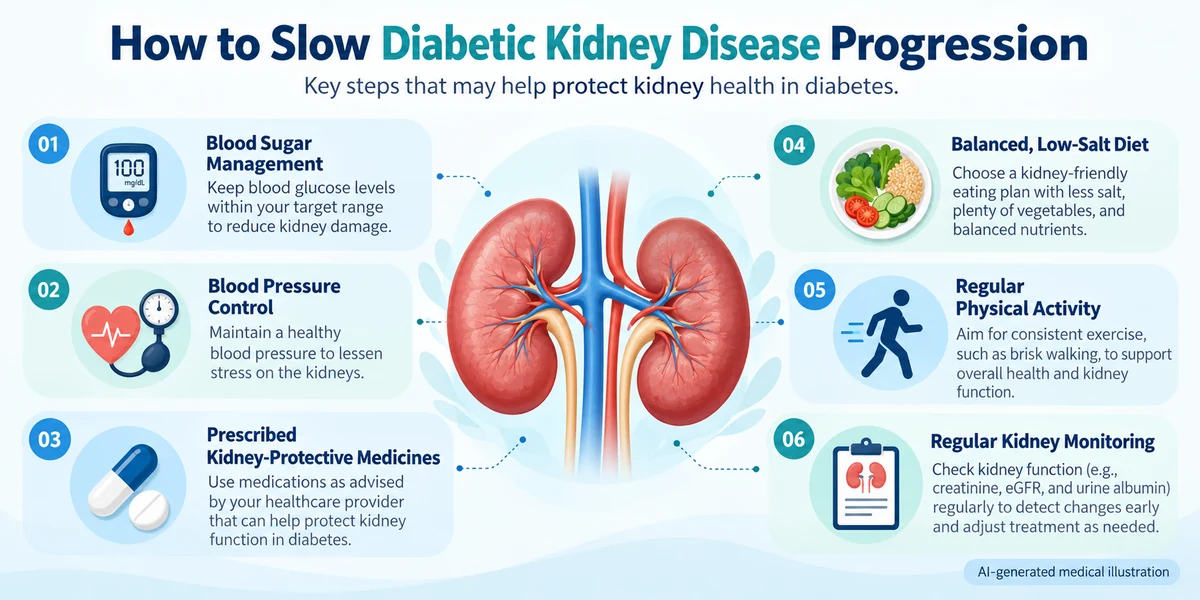
Diabetic kidney disease progression can often be slowed through appropriate blood glucose management, blood pressure control, kidney-protective medicines, dietary measures, physical activity and regular kidney monitoring. However, treatment outcomes vary, and no approach guarantees that kidney damage will stop or reverse completely. Diabetic kidney disease (DKD) can develop gradually, sometimes without noticeable symptoms. Early abnormalities may appear as increased albumin in urine, reduced estimated glomerular filtration rate (eGFR), or both. Monitoring urine albumin-to-creatinine ratio (uACR) and eGFR helps identify kidney abnormalities and track changes over time. This article explains ten evidence-based approaches to managing diabetic kidney disease, including treatment considerations, diet, kidney testing and warning signs. What Is Diabetic Kidney Disease? Diabetic kidney disease refers to kidney damage associated with diabetes. The kidneys contain microscopic filtering structures called glomeruli. These structures help remove waste products and excess fluid from the bloodstream while retaining most essential proteins. Long-term elevated blood glucose can affect the kidneys’ blood vessels and filtering structures. Possible changes include: Increased albumin leakage into urine. Injury to the glomerular filtration barrier. Gradual reduction in kidney filtration. Changes in fluid and electrolyte balance as dysfunction advances. Increased risk of cardiovascular complications. High blood pressure may contribute to further kidney injury. However, not everyone with diabetes develops kidney disease, and not every abnormal kidney result in someone with diabetes is caused by diabetes. For related information, read Diabetic Kidney Disease Symptoms. Can Diabetic Kidney Disease Progression Be Slowed? Yes. Appropriate medical management can reduce the risk of kidney disease progression in eligible patients. Treatment may help reduce albuminuria, slow the decline in eGFR and lower the risk of certain cardiovascular complications. However, the response depends on several factors: Existing kidney function. Urine albumin levels. Duration and type of diabetes. Blood pressure. Cardiovascular health. Other kidney disorders. Current medicines and treatment tolerance. Some people experience stable kidney function or improved urine albumin measurements. Others may continue to experience declining kidney function despite appropriate treatment. Slowing progression is not the same as curing established chronic kidney disease. What Increases the Risk of Diabetic Kidney Disease Progression? Several factors may contribute to kidney-related risk. Persistently Elevated Blood Glucose Long-term hyperglycaemia may contribute to blood vessel injury and changes in kidney filtration. High Blood Pressure Hypertension can worsen kidney damage and increase cardiovascular risk. Increased Urine Albumin Persistent albuminuria is associated with kidney damage and may indicate an increased risk of progression. Declining eGFR A sustained decline in eGFR may suggest worsening kidney filtration. Cardiovascular Disease Heart and blood vessel conditions frequently coexist with chronic kidney disease. Tobacco Use Smoking increases vascular and cardiovascular risks. Other medical conditions, certain medicines, acute kidney injury and urinary obstruction may also affect kidney function. The overall risk should be assessed using clinical findings and changes in laboratory results over time. 10 Evidence-Based Ways to Slow Diabetic Kidney Disease Progression 1. Manage Blood Glucose According to Individual Targets Appropriate blood glucose management is important for reducing diabetes-related complications. HbA1c reflects average blood glucose over approximately the previous two to three months. A target near 7% may be suitable for many non-pregnant adults with diabetes, but it is not appropriate for everyone. Individual HbA1c targets depend on: Age and general health. Risk of hypoglycaemia. Kidney function. Diabetes duration. Cardiovascular disease. Other medical conditions. Current treatment. In people with advanced kidney disease, HbA1c interpretation may sometimes be affected by anaemia and changes in red blood cell turnover. Home glucose monitoring or continuous glucose monitoring may provide additional information when appropriate. Patients should not adjust prescribed diabetes medicines independently to reach a particular HbA1c target. 2. Control Blood Pressure High blood pressure is an important contributor to kidney and cardiovascular complications. Blood pressure management may help reduce the risk of diabetic kidney disease progression. For many adults with diabetes, a blood pressure target below 130/80 mmHg may be considered when safely achievable. However, targets should be individualised according to clinical circumstances and treatment tolerance. Excessively aggressive treatment can cause problems such as dizziness, low blood pressure or reduced circulation in susceptible individuals. Management may include: Appropriate prescribed medicines. Reducing excessive dietary sodium. Physical activity. Weight management when indicated. Home blood pressure monitoring where appropriate. Not everyone needs the same monitoring frequency or medicine combination. 3. Use Kidney-Protective Medicines When Appropriate Certain medicines have demonstrated kidney or cardiovascular benefits in eligible patients. Their suitability depends on diabetes type, eGFR, urine albumin, blood pressure, associated conditions and potential adverse effects. ACE Inhibitors and ARBs Angiotensin-converting enzyme inhibitors (ACE inhibitors) and angiotensin receptor blockers (ARBs) may reduce albuminuria and kidney-related risk in selected people, particularly when hypertension and albuminuria are present. They can affect serum creatinine, potassium and blood pressure. Monitoring may be needed after starting treatment or adjusting the dose. ACE inhibitors and ARBs should not routinely be combined. SGLT2 Inhibitors Certain sodium-glucose cotransporter-2 (SGLT2) inhibitors have demonstrated benefits in reducing kidney disease progression and cardiovascular events. They are recommended for many eligible people with type 2 diabetes and CKD. Potential adverse effects include genital infections, volume depletion and, rarely, ketoacidosis. Medication management during acute illness or around certain procedures may require specific medical guidance. GLP-1 Receptor Agonists Selected glucagon-like peptide-1 receptor agonists may offer kidney and cardiovascular benefits in people with type 2 diabetes and CKD. Potential adverse effects and contraindications must be considered. Nonsteroidal Mineralocorticoid Receptor Antagonists Finerenone may benefit selected people with type 2 diabetes, CKD and persistent albuminuria. It can increase potassium and requires appropriate clinical and laboratory monitoring. Important: Not everyone requires every kidney-protective medicine. Prescribing decisions should be made by a qualified healthcare professional. 4. Reduce Excessive Salt Intake Excess dietary sodium can contribute to high blood pressure and fluid retention. Reducing excessive salt intake may support blood pressure and kidney management. KDIGO guidance suggests sodium intake below approximately 2 grams per day, equivalent to about 5 grams of salt, for many adults with CKD. However, dietary advice should be individualised. Certain medical conditions may require a different approach. Practical measures include: Reducing added salt during

Diabetic Kidney Disease Symptoms: Early Signs & Tests

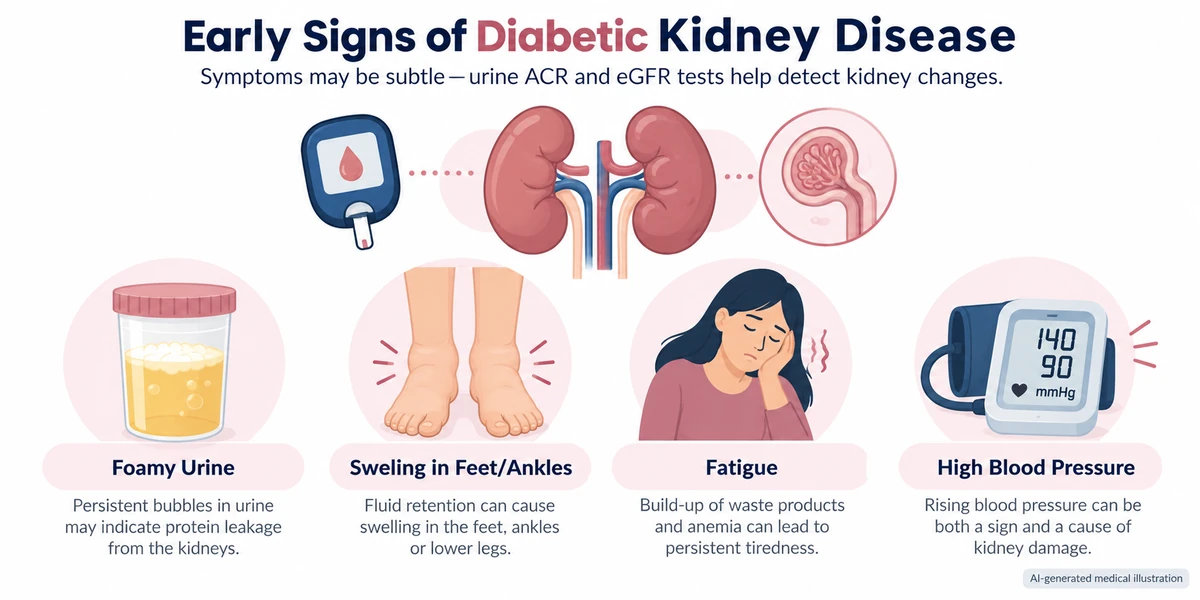
Diabetic kidney disease (DKD) is a form of kidney damage associated with diabetes. Over time, high blood glucose can affect the kidneys’ filtering structures, sometimes causing albumin to leak into urine or reducing kidney filtration. Early diabetic kidney disease often develops without noticeable symptoms. Urine albumin-to-creatinine ratio (uACR) and estimated glomerular filtration rate (eGFR) tests help identify and monitor kidney abnormalities. Not everyone with diabetes develops kidney disease. Individual risk depends on diabetes duration, blood glucose management, blood pressure and other medical factors. Quick Answer: What Are the Early Symptoms of Diabetic Kidney Disease? Early diabetic kidney disease often causes no obvious symptoms. The first signs may appear on kidney tests, such as increased albumin in urine or changes in eGFR. As kidney disease progresses, possible symptoms may include:  – Foamy or unusually bubbly urine  – Swelling in the feet, ankles or around the eyes  – Fatigue or weakness  – Changes in urination  – Nausea or reduced appetite  – Itching or muscle cramps  – Increasing or difficult-to-control blood pressure Because early diabetic kidney disease is often silent, blood and urine tests are more reliable than waiting for symptoms to appear.  What Is Diabetic Kidney Disease? Diabetic kidney disease develops when diabetes damages the small blood vessels and filtering structures inside the kidneys. The kidneys contain microscopic filtering units called glomeruli. Over time, persistently high blood glucose can damage these filters, allowing albumin to leak into the urine and gradually reducing the kidneys’ ability to remove waste from the blood. High blood pressure can further increase stress on the kidneys and accelerate kidney damage. For a broader explanation, read about diabetes and kidney diseases. Why Can Diabetic Kidney Disease Develop Without Symptoms? Kidneys have significant reserve capacity. Early kidney damage may therefore develop while a person still feels completely well. NIDDK notes that most people with diabetic kidney disease do not have symptoms in the early stages. Kidney problems are usually detected through blood and urine tests.  A patient can have: No pain + no swelling + normal-looking urine and still have albuminuria or another early kidney abnormality. Who Is at Higher Risk? Not everyone with diabetes develops diabetic kidney disease. Risk may be greater in people who have: Diabetes for many years Persistently high blood glucose High blood pressure Cardiovascular disease Smoking habits Excess body weight Family history of kidney failure Existing kidney abnormalities NIDDK identifies poor blood-glucose control and high blood pressure as especially important risk factors.  Type 1 vs Type 2 Diabetes: When Should Kidney Testing Begin? Type 1 Diabetes Current ADA 2026 recommendations advise checking urine ACR and eGFR at least annually once a person has had type 1 diabetes for five years or more.  Type 2 Diabetes People with type 2 diabetes should generally have urine ACR and eGFR checked at least once a year from diagnosis, regardless of treatment. Diabetes Journals This difference matters because type 2 diabetes may have been present for years before it is diagnosed. What Are the Earliest Signs of Kidney Damage in Diabetes? The earliest signs are often found on laboratory tests. 1. Albumin in the Urine Albumin is a protein that normally remains in the bloodstream. When the kidney filters are damaged, albumin can begin leaking into urine. This is called albuminuria. The standard test used to measure this is the urine albumin-to-creatinine ratio (UACR). For more detail, see the Urine ACR Test Guide. 2. Changes in eGFR The estimated glomerular filtration rate (eGFR) estimates how well the kidneys are filtering blood. A declining eGFR can indicate reduced kidney function. 3. Changes in Serum Creatinine Creatinine is a waste product normally filtered from the blood by the kidneys. As filtration worsens, serum creatinine may increase. However, creatinine alone is not enough to assess early diabetic kidney disease. 4. Increasing Blood Pressure High blood pressure can damage kidney blood vessels, while kidney disease can also make blood pressure more difficult to control. Patients with persistent blood-pressure problems can read more about resistant hypertension. The Two Most Important Tests for Diabetic Kidney Disease The two key kidney markers are: Urine ACR (UACR) eGFR NIDDK specifically identifies urine albumin and eGFR as the two major markers used to detect and monitor chronic kidney disease.  Urine Albumin-to-Creatinine Ratio (UACR) UACR measures albumin in urine relative to creatinine. A random spot urine sample is usually sufficient, meaning a 24-hour urine collection is generally unnecessary for routine screening.  Typical categories include: An increased urine ACR may indicate kidney damage, but one abnormal result does not automatically establish chronic kidney disease. Albumin levels can be temporarily affected by fever, infection, strenuous exercise, menstruation, markedly elevated blood glucose and other factors. Repeat testing and clinical assessment may be required to determine whether albuminuria is persistent. A UACR above 30 mg/g is considered abnormal, but the result should be interpreted with other kidney tests and, when appropriate, repeat measurements.  eGFR eGFR estimates kidney filtration. In general: 60 or above: may be within an acceptable range depending on the clinical situation Below 60: may indicate kidney disease if the reduction persists 15 or below: represents severely reduced kidney function and may indicate kidney failure The result should always be interpreted alongside urine albumin and the patient’s medical history. Can You Have Diabetic Kidney Disease with a Normal eGFR? Yes. A person may have: Normal or relatively preserved eGFR + elevated urine ACR and still have evidence of kidney damage. Albuminuria can appear before significant changes in eGFR. This is why checking only creatinine or eGFR may miss early kidney damage.  How to Understand UACR and eGFR Together How to Understand UACR and eGFR Together UACR eGFR What It May Suggest Normal Normal Current kidney markers may be reassuring. High Normal Possible early kidney damage. Normal Low Reduced kidney filtration requiring evaluation. High Low Kidney damage with reduced filtration may be present. This table is a general guide only. Diagnosis depends on repeat testing, trends over time and the patient’s overall clinical condition. Learn more about combined kidney testing

How to Prevent Kidney Stones Recurrence: Diet & Tips

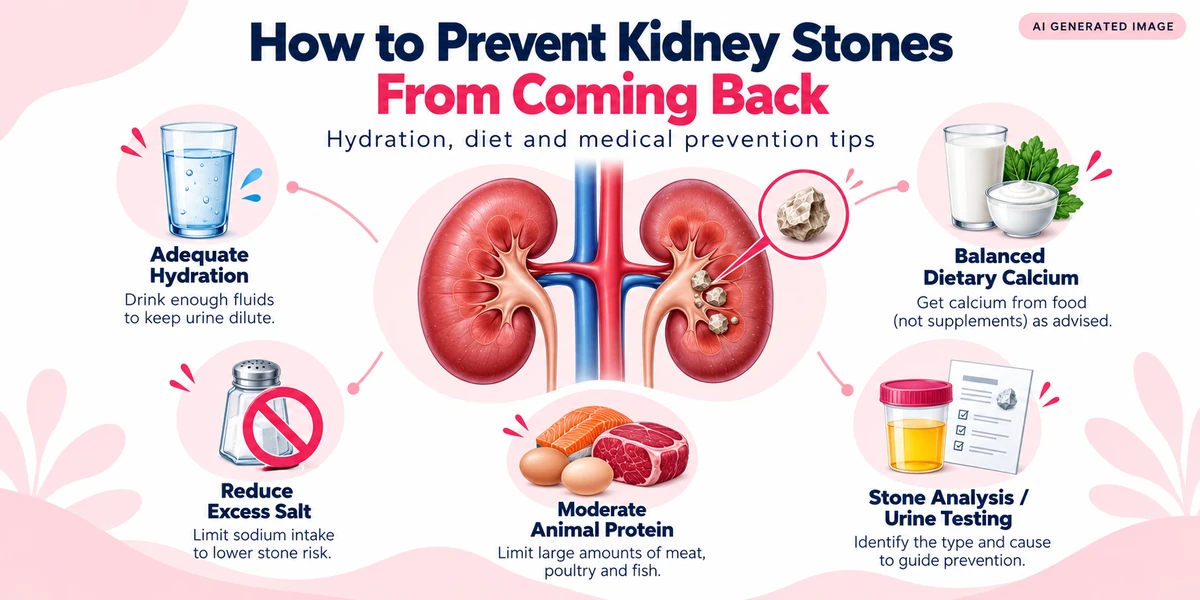
Kidney stones can return after a previous episode, but appropriate hydration, dietary changes and medical evaluation may help reduce the risk of recurrence. Prevention depends on factors such as stone composition, urine chemistry, fluid intake, medical conditions and family history. Common preventive measures include maintaining adequate hydration, reducing excessive sodium intake, consuming appropriate amounts of dietary calcium and avoiding unnecessarily high animal protein intake. People who experience repeated kidney stones may benefit from stone analysis and metabolic testing to identify factors contributing to stone formation. What Are Kidney Stones? Kidney stones are solid deposits formed when certain minerals and substances become concentrated in urine and crystallise. Stones may develop in one or both kidneys and vary in size, composition and clinical significance. Some small stones cause no symptoms, while others can produce pain, bleeding, urinary obstruction or infection. A previous kidney stone increases the likelihood of developing another stone, although recurrence risk varies considerably between individuals.For additional information about stone formation, types and general preventive measures, read Kidney Stone Prevention. Why Do Kidney Stones Come Back? Kidney stones may recur when conditions that favour crystal formation remain present. These include concentrated urine, high urinary calcium or oxalate levels, low urinary citrate, increased uric acid, certain medical conditions and inherited risk factors. Common contributors include: – Inadequate fluid intake or excessive fluid loss – High dietary sodium intake – Excessive animal protein consumption – Certain metabolic abnormalities – A family history of kidney stones – Obesity and some associated medical conditions – Recurrent urinary tract infections in selected stone types – Certain medicines or supplements The cause of recurrence cannot always be determined from symptoms alone. What Are the Different Types of Kidney Stones? Identifying the stone type can help guide prevention. 1. Calcium Oxalate Stones Calcium oxalate stones are among the most common kidney stone types. They may be associated with increased urinary calcium or oxalate, low urine volume or reduced urinary citrate. Dietary recommendations depend on individual risk factors. 2. Calcium Phosphate Stones Calcium phosphate stones may occur in association with certain metabolic conditions and changes in urine chemistry. Evaluation may include assessment of urine pH, calcium excretion and relevant medical conditions. 3. Uric Acid Stones Uric acid stones are more likely to form in persistently acidic urine. They may be associated with metabolic factors, gout and certain dietary patterns. Management may involve changes in urine chemistry under medical supervision. 4. Struvite Stones Struvite stones may form in association with urinary tract infections caused by particular bacteria. Prevention generally requires attention to the underlying infection and any remaining stone material. 5. Cystine Stones Cystine stones occur in people with cystinuria, an inherited condition that causes increased cystine excretion in urine. They may require specialist evaluation and a targeted prevention plan. Important: Not every dietary recommendation applies to every kidney stone type. How Can You Reduce the Risk of Kidney Stone Recurrence? 1. Maintain Adequate Hydration Drinking sufficient fluid helps dilute substances in urine that may contribute to stone formation. For many adults with recurrent kidney stones who do not require fluid restriction, guidelines commonly recommend fluid intake sufficient to produce approximately 2.5 litres or more of urine per day. The amount of fluid required varies according to climate, sweating, physical activity and medical conditions. Water is generally the preferred beverage. People with heart failure, advanced kidney disease or prescribed fluid restrictions should not increase fluid intake without medical advice. 2. Reduce Excess Sodium Intake A high-sodium diet can increase urinary calcium excretion and contribute to calcium stone formation in susceptible individuals. Dietary sodium comes from table salt as well as packaged foods, processed snacks, pickles, sauces and restaurant meals. For many adults, limiting sodium to approximately 2,300 mg per day or less may be appropriate, although individual targets vary. Practical approaches include choosing less processed food, checking food labels and reducing added salt. 3. Consume Appropriate Amounts of Dietary Calcium A common misconception is that people with calcium kidney stones should avoid calcium-rich foods. In fact, very low dietary calcium intake may increase calcium oxalate stone risk because calcium in the digestive tract helps bind dietary oxalate. Many adults require approximately 1,000–1,200 mg of calcium daily, depending on age and other health factors. Calcium is preferably obtained through a balanced diet when possible. Calcium supplements should be discussed with a healthcare professional because their appropriateness depends on individual circumstances. 4. Avoid Excessive Animal Protein Intake Excessive animal protein consumption may increase the likelihood of certain kidney stones by affecting urinary calcium, uric acid, citrate or acidity. Animal protein sources include meat, poultry, fish and eggs. The appropriate amount depends on overall nutritional needs, stone type and existing medical conditions. A balanced eating pattern with suitable plant-based protein sources may be helpful for some individuals. Do not start a severely protein-restricted diet without medical guidance. 5. Consider Oxalate Intake When Relevant Oxalate is a naturally occurring substance found in many foods. For people with calcium oxalate stones and increased urinary oxalate, a clinician may recommend moderating certain high-oxalate foods. Examples include: – Spinach – Rhubarb – Certain nuts – Wheat bran – Some other concentrated oxalate sources However, not everyone with kidney stones needs a low-oxalate diet. Combining oxalate-containing foods with an appropriate amount of dietary calcium can help reduce oxalate absorption. 6. Maintain a Balanced Eating Pattern A varied diet containing suitable portions of vegetables, fruits, whole grains and other nutritious foods may support general health and kidney stone prevention. A DASH-style dietary pattern has been associated with reduced kidney stone risk in research. Dietary modifications may be necessary for people with chronic kidney disease, high potassium levels or other medical conditions. 7. Review Sugary Drinks and Supplements Frequent consumption of sugar-sweetened beverages may contribute to stone risk in some individuals. High-dose vitamin C supplementation can increase urinary oxalate in susceptible individuals. Certain other supplements may also influence urine chemistry. Discuss supplements with a qualified healthcare professional rather than assuming that a product labelled natural is harmless. 8.

When Should You See a Nephrologist in Navi Mumbai?

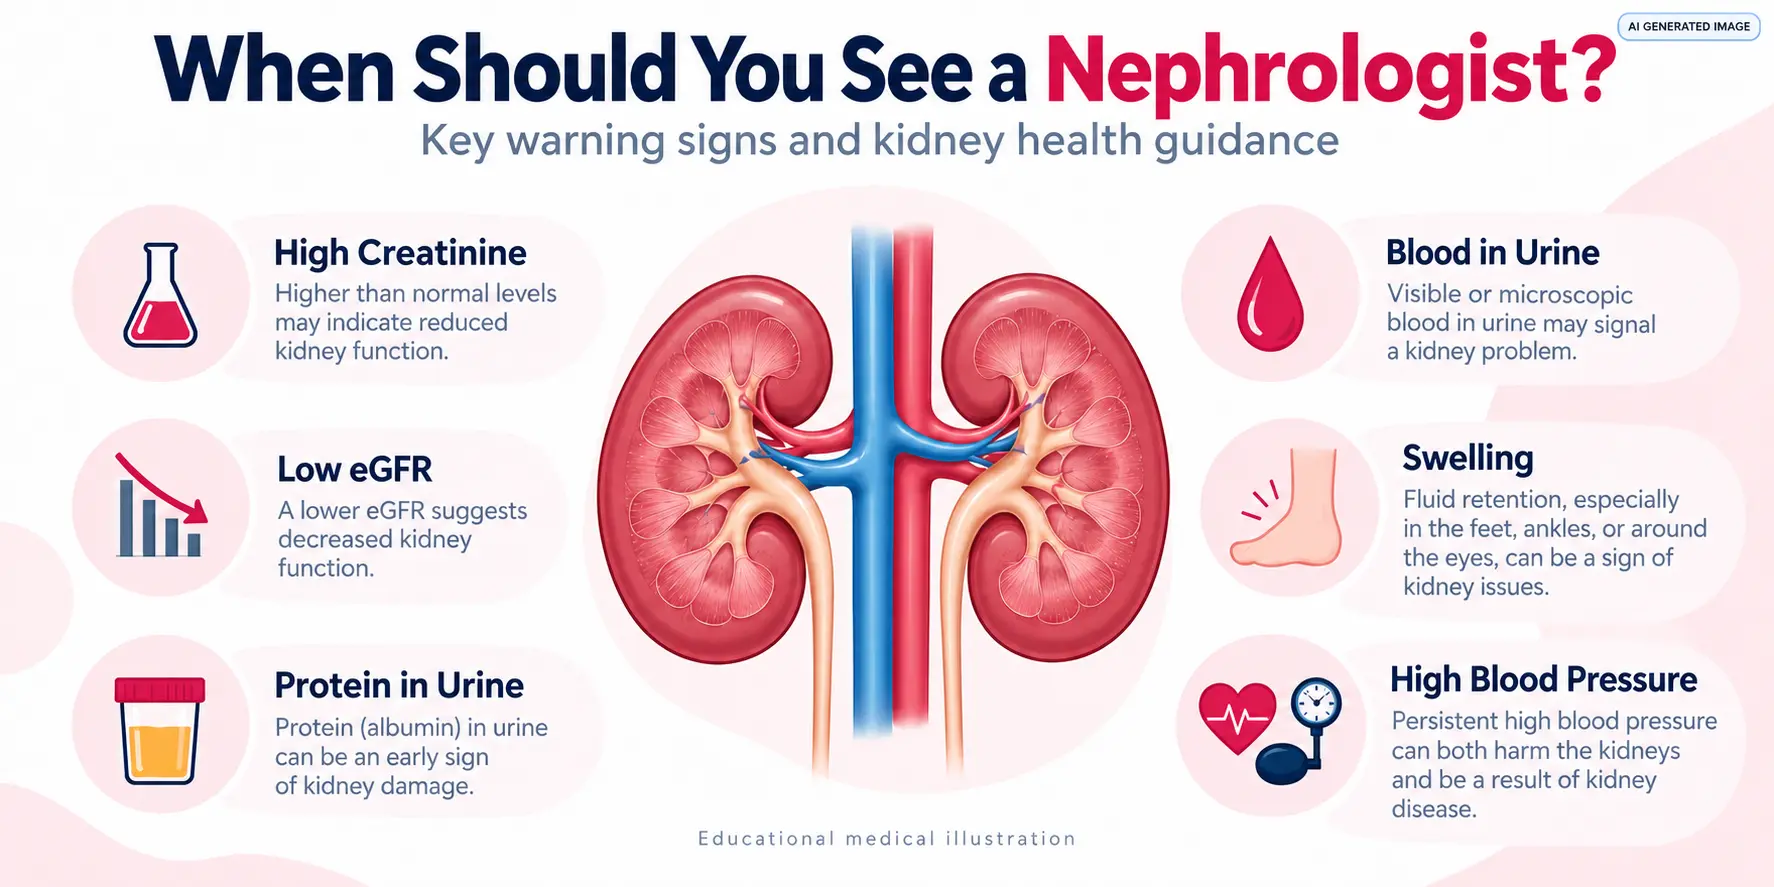
When Should You See a Nephrologist? 10 Warning Signs, Kidney Tests & Medical Guidance You may need to see a nephrologist if kidney function tests remain abnormal, protein or blood is repeatedly detected in urine, kidney function declines, or high blood pressure is difficult to control. People with diabetes, certain autoimmune disorders or a family history of kidney disease may also require kidney health monitoring and specialist evaluation. Kidney diseases can develop without noticeable symptoms. Blood tests, urine investigations and clinical assessment help identify abnormalities and determine whether specialist care is appropriate. What Is a Nephrologist? A nephrologist is a medical doctor specialising in the evaluation and management of conditions affecting the kidneys. The kidneys perform several important functions, including filtering waste products from blood, regulating fluid and electrolyte balance, helping control blood pressure and supporting red blood cell production. Nephrology covers conditions such as: Acute kidney injury (AKI) Chronic kidney disease (CKD) Diabetic kidney disease Glomerulonephritis Kidney-related hypertension Protein or blood in urine Fluid and electrolyte disorders Dialysis-related medical care Kidney transplant-related assessment Not every abnormal kidney test requires immediate specialist care. The need for a nephrologist depends on the medical findings, severity, rate of change and underlying condition. What Are the 10 Signs You May Need to See a Nephrologist? 1. Persistently High Creatinine Levels Creatinine is a waste product normally removed from the blood by the kidneys. An elevated serum creatinine level may indicate reduced kidney filtration. However, dehydration, muscle mass, certain medicines, strenuous exercise and dietary factors can also influence the result. Persistently elevated or rapidly increasing creatinine requires medical evaluation to identify the possible cause. A single abnormal creatinine reading does not automatically mean kidney failure. Related Reading: What Causes High Creatinine? 2. Reduced or Declining eGFR Estimated glomerular filtration rate (eGFR) helps estimate how effectively the kidneys filter blood. An eGFR below 60 mL/min/1.73 m² that persists for at least three months may indicate chronic kidney disease. A single reduced result does not always establish CKD. Temporary illness, acute kidney injury and other factors may influence kidney function. An eGFR below 30 mL/min/1.73 m² is an important reason to consider nephrology referral, while a rapid decline in eGFR may require assessment even at higher values. 3. Persistent Protein in Urine Protein in urine, also called proteinuria, may indicate changes in the kidneys’ filtering structures. The urine albumin-to-creatinine ratio (ACR) is commonly used to detect albumin leakage. Persistent or substantial albuminuria may require additional investigations, particularly when associated with diabetes, hypertension or reduced eGFR. Temporary albuminuria can occur during illness or after strenuous exercise, so repeat testing may be necessary. Related Reading: Understanding the Urine ACR Test 4. Blood in Urine Without a Clear Cause Blood in urine, called haematuria, may be visible or detected only through laboratory testing. Possible causes include urinary tract infections, stones, kidney inflammation and other urinary tract conditions. Persistent haematuria, especially when accompanied by proteinuria, reduced kidney function or high blood pressure, may suggest a kidney-related disorder. Depending on the cause, evaluation by a nephrologist, urologist or another appropriate clinician may be necessary. Visible blood in urine should receive medical assessment even when there is no pain. 5. High Blood Pressure That Is Difficult to Control The kidneys help regulate blood pressure. Kidney disease can contribute to hypertension, while persistently high blood pressure can damage kidney blood vessels. Blood pressure that remains above the individual treatment target despite an appropriate medication regimen may require further evaluation. A healthcare professional may assess kidney function, urine abnormalities, medication use and possible secondary causes of hypertension. 6. Diabetes With Abnormal Kidney Tests Diabetes can damage the kidneys’ small filtering structures over time. Diabetic kidney disease may develop without symptoms, and serum creatinine can remain within the laboratory reference range during earlier stages. Kidney health assessment commonly includes eGFR and urine ACR testing. People with diabetes who develop persistent albuminuria, declining eGFR or unexplained kidney abnormalities may require specialist assessment. Related Reading: Diabetes & Kidney Diseases 7. Unexplained Swelling of the Feet, Ankles or Face Swelling, also called oedema, may occur when fluid accumulates in body tissues. Kidney-related conditions can contribute to fluid retention or loss of protein through urine. However, swelling may also result from heart disease, liver disorders, venous problems, certain medicines or other causes. Persistent or unexplained swelling should be medically evaluated. Sudden swelling associated with severe breathlessness requires emergency medical attention. 8. Recurrent Kidney Stones or Complex Kidney-Related Problems Kidney stones can sometimes cause urinary obstruction, infection or changes in kidney function. Many kidney stones are assessed and treated by urologists. Nephrologists may be involved in evaluating recurrent stone formation, metabolic risk factors or associated kidney disease. The appropriate specialist depends on the individual’s condition and treatment requirements. 9. Family History of Kidney Disease A family history of certain kidney disorders may increase an individual’s risk of developing kidney disease. Examples include polycystic kidney disease and some inherited glomerular or tubular disorders. Family history, blood pressure, urine testing and kidney function results can help healthcare professionals determine whether additional assessment is appropriate. Genetic evaluation may be considered in selected cases. 10. Known Kidney Disease or Complicated Medical Conditions People with diagnosed kidney disease may require specialist input when kidney function worsens, urine abnormalities increase or complications develop. Some autoimmune diseases, serious infections and conditions affecting multiple organs can also involve the kidneys. Nephrology assessment may help clarify the diagnosis, evaluate complications and guide appropriate monitoring. When Is Nephrology Referral Recommended Based on Kidney Tests? Kidney function results are considered together rather than interpreted as isolated numbers. Finding General clinical significance Persistently elevated creatinine May indicate reduced filtration or another contributing factor eGFR below 60 for at least 3 months May indicate CKD eGFR below 30 Important reason to consider specialist referral Rapidly declining eGFR Requires assessment; urgency depends on the situation Persistently elevated urine ACR May indicate kidney damage Persistent haematuria with proteinuria May suggest a glomerular disorder Significant electrolyte abnormalities May require prompt or specialist evaluation The KDIGO

Nephrologist vs Urologist: Which Specialist Should You See?

The main difference between a nephrologist and a urologist is the type of conditions they diagnose and manage. A nephrologist specialises in the medical evaluation and treatment of kidney diseases, while a urologist focuses on conditions affecting the urinary tract and male reproductive system, including those that may require surgery. Both specialists may evaluate kidney-related concerns, but their roles are different and sometimes overlap. For example, a person with persistent high creatinine or protein in urine may require nephrology evaluation. Someone with an obstructing kidney stone, urinary retention or a prostate problem may require urological assessment. Understanding these differences can help patients recognise when specialist evaluation may be appropriate. What Is a Nephrologist? A nephrologist is a medical doctor who specialises in diagnosing and managing diseases that affect kidney function. The kidneys remove waste products and excess fluid from the bloodstream. They also help regulate electrolytes, blood pressure, acid–base balance and processes involved in red blood cell production and bone health. Nephrologists evaluate conditions that interfere with these functions. Their work generally focuses on medical treatment, monitoring and the management of kidney-related complications rather than urinary tract surgery. What Conditions Does a Nephrologist Treat? Nephrologists commonly evaluate and manage: Chronic kidney disease (CKD): Long-term abnormalities of kidney structure or function. Acute kidney injury (AKI): A sudden decline in kidney function. Diabetic kidney disease: Kidney damage associated with diabetes. Hypertension-related kidney disease: Kidney problems associated with high blood pressure. Proteinuria and albuminuria: Abnormal protein or albumin in urine. Glomerular diseases: Disorders affecting the kidneys’ filtering structures. Fluid and electrolyte abnormalities: Conditions involving potassium, sodium, fluid balance or acid–base regulation. Dialysis-related conditions: Assessment and ongoing medical management of patients requiring dialysis. Kidney transplant-related care: Medical evaluation and follow-up before and after transplantation. A nephrologist may also evaluate unexplained changes in kidney function or persistent abnormalities in blood and urine test results. What Is a Urologist? A urologist is a medical specialist who diagnoses and treats conditions affecting the urinary tract in people of all sexes and the male reproductive system. The urinary tract includes the kidneys, ureters, bladder and urethra. Urology includes both medical and surgical treatments. Although many urological conditions can be managed without surgery, urologists have specialised training in procedures involving the urinary tract. What Conditions Does a Urologist Treat? Urologists commonly evaluate and manage: Kidney and ureteric stones: Particularly stones causing obstruction, pain or other complications. Urinary tract obstruction: Blockages affecting normal urine drainage. Enlarged prostate: Prostate enlargement that may cause urinary symptoms or retention. Bladder disorders: Conditions affecting urine storage and emptying. Urinary incontinence: Difficulty controlling urination. Recurrent urinary tract infections: Particularly when anatomical or functional abnormalities are suspected. Blood in urine: Evaluation for possible structural, inflammatory or other urinary tract conditions. Urinary tract tumours: Conditions affecting the kidneys, bladder or other urinary organs. Male reproductive and sexual health disorders: Selected conditions involving the prostate, testes and reproductive system. The appropriate treatment depends on the diagnosis, disease severity and individual clinical findings. Nephrologist vs Urologist: Key Differences The following table explains how the two medical specialties differ. Feature Nephrologist Urologist Primary focus Medical conditions affecting kidney function Diseases of the urinary tract and male reproductive system Type of care Mainly medical diagnosis, treatment and monitoring Medical, procedural and surgical management Chronic kidney disease Common area of care May be involved when structural or surgical problems contribute High creatinine Evaluates possible kidney dysfunction May be involved if an obstruction or other urological cause is suspected Kidney stones May assess kidney function and stone prevention May treat stones requiring procedures or surgery Protein in urine Evaluates possible kidney filtering disorders May participate when another urinary tract problem is suspected Dialysis Medical management and monitoring May assist with selected surgical or access-related procedures Kidney transplantation Medical evaluation and transplant follow-up Transplant surgery is performed by appropriately trained transplant surgeons, who may have urological training Important: These are common areas of practice, not exclusive boundaries. The appropriate specialist depends on the patient’s clinical findings, and collaborative care may be needed. When Should You See a Nephrologist? A nephrology evaluation may be appropriate when symptoms, medical conditions or laboratory findings suggest impaired kidney function. 1. Persistently High Creatinine Creatinine is a waste product that the kidneys normally remove from the bloodstream. An elevated result may indicate reduced kidney filtration, but it can also be influenced by dehydration, medicines, muscle mass and other factors. A nephrologist may assess serum creatinine alongside eGFR, urine tests, previous results and medical history to investigate its significance. For additional information, read What Causes High Creatinine. 2. Reduced eGFR Estimated glomerular filtration rate (eGFR) helps assess how effectively the kidneys filter blood. A persistently reduced eGFR may indicate chronic kidney disease. However, a single abnormal result does not necessarily establish a chronic diagnosis. A nephrologist may evaluate the cause, changes over time and associated complications. 3. Protein or Albumin in Urine Albuminuria or proteinuria may indicate damage to the kidney’s filtering structures. Evaluation may include urine albumin-to-creatinine ratio (ACR), urine protein measurements, kidney function tests and other investigations. Foamy urine may sometimes accompany proteinuria, but foam alone does not confirm kidney disease. 4. Kidney Problems Associated With Diabetes Diabetes can damage the small filtering structures in the kidneys. Early diabetic kidney disease may develop without noticeable symptoms. Nephrology assessment may be considered when urine albumin is persistently elevated, kidney function declines or the clinical condition becomes more complex. 5. Difficult-to-Control Blood Pressure With Kidney Abnormalities Persistent hypertension can contribute to kidney damage, while impaired kidney function can make blood pressure harder to manage. A nephrologist may help evaluate kidney involvement and associated electrolyte or fluid abnormalities. 6. Advanced Chronic Kidney Disease People with advanced kidney disease may require evaluation of anaemia, mineral and bone disorders, electrolyte abnormalities and the potential need for kidney replacement treatment. Nephrologists also help patients understand dialysis, transplantation and conservative kidney management. When Should You See a Urologist? Urological evaluation may be appropriate when symptoms or investigations suggest a disorder affecting urine drainage, bladder