
Diabetic nephropathy is kidney damage attributed to diabetes, while chronic kidney disease (CKD) is a broader medical diagnosis describing abnormalities of kidney structure or function that persist for at least three months and have implications for health.
Diabetes is one of the possible causes of CKD, but CKD can also result from high blood pressure, glomerular diseases, inherited conditions and other kidney disorders.
A person with diabetes may develop CKD because of diabetes, an unrelated kidney disease or a combination of conditions.
The distinction is important because the underlying cause, urine findings, kidney filtration and other clinical factors help determine appropriate investigations and treatment.
This article explains the differences between diabetic nephropathy and CKD, their symptoms, diagnostic tests, stages, treatment considerations and warning signs.
Diabetic nephropathy refers to kidney damage associated with diabetes.
The term is often used alongside diabetic kidney disease (DKD), although diabetic nephropathy can also refer more specifically to characteristic structural changes caused by diabetes.
The kidneys contain microscopic filtering structures called glomeruli.
Over time, elevated blood glucose can affect the small blood vessels and filtering barrier within these structures.
Possible changes include:
Thickening of the glomerular basement membrane.
Changes in the supporting tissue within the glomeruli.
Increased albumin leakage into urine.
Injury to kidney blood vessels.
Progressive reduction in kidney filtration in some individuals.
High blood pressure may contribute to further kidney damage.
However, diabetic kidney disease does not follow the same pattern in everyone.
Some people develop increased urinary albumin before eGFR declines, while others develop reduced eGFR without significant albuminuria.
Not every person with diabetes develops diabetic nephropathy.
Chronic kidney disease is a condition involving abnormalities of kidney structure or function that persist for at least three months and have implications for health.
CKD may be present when there is:
Persistently reduced eGFR.
Persistent albuminuria.
Certain abnormalities in urine sediment.
Structural kidney abnormalities.
Other recognised evidence of chronic kidney damage.
An eGFR below 60 mL/min/1.73 m² persisting for at least three months is one criterion for CKD.
CKD may also be present with an eGFR of 60 or above when other evidence of persistent kidney damage exists.
Possible causes include:
Diabetes.
High blood pressure.
Glomerulonephritis and other glomerular disorders.
Polycystic kidney disease and other inherited conditions.
Certain autoimmune disorders.
Chronic urinary obstruction.
Other vascular, inflammatory or structural kidney conditions.
Determining the underlying cause is an important part of kidney disease evaluation.
Diabetic Nephropathy vs CKD: Key Differences
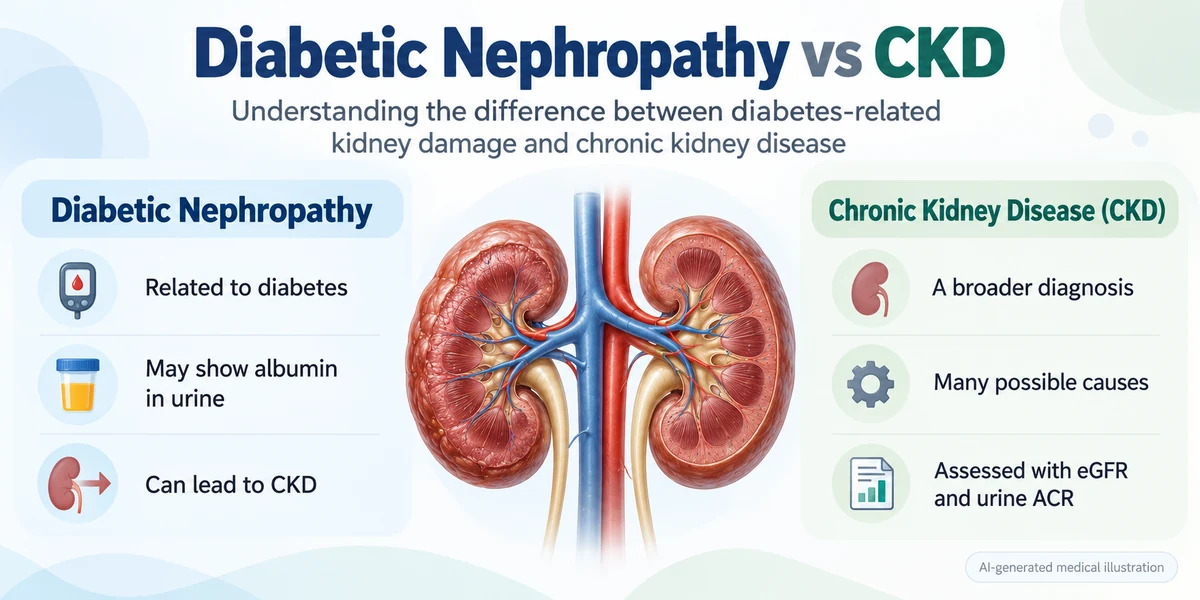
Although the conditions are closely related, they are not interchangeable.
| Feature | Diabetic nephropathy | Chronic kidney disease (CKD) |
|---|---|---|
| Meaning | Kidney damage attributed to diabetes | Persistent kidney abnormalities lasting at least three months |
| Underlying cause | Diabetes-associated kidney injury | Diabetes or various other causes |
| Relationship | May be a cause of CKD | Includes diabetic and non-diabetic kidney diseases |
| Urine albumin | May be increased or normal | May be increased or normal |
| eGFR | May be preserved or reduced | May be preserved when other kidney-damage markers exist, or reduced |
| Symptoms | Often absent early | Often absent early |
| Diagnosis | Based on diabetes history, kidney findings and assessment of other causes | Based on persistent kidney structure or function abnormalities |
| Management | Diabetes care plus kidney and cardiovascular risk management | Depends on underlying cause, kidney function and complications |
| Progression | Variable | Variable |
Key point: Diabetic nephropathy can fall within the broader category of CKD, but CKD is not always caused by diabetes.
Long-term diabetes may affect kidney blood vessels, glomeruli and other kidney structures.
In some people, the earliest detected abnormality is increased urine albumin.
Over time, ongoing injury may contribute to reduced kidney filtration.
However, this sequence is not inevitable.
Some people experience:
Persistent albuminuria with preserved eGFR.
Reduced eGFR without increased albuminuria.
Both increased albuminuria and reduced filtration.
Stable kidney function over prolonged periods.
Improvement in certain laboratory abnormalities after appropriate treatment.
An abnormal test result should be interpreted alongside previous results, diabetes duration, blood pressure and other clinical findings.
Yes.
Diabetes is not required for a diagnosis of chronic kidney disease.
CKD may result from hypertension, inherited kidney conditions, autoimmune disorders, glomerulonephritis or other causes.
A person without diabetes may have persistent albuminuria, reduced eGFR or structural kidney abnormalities.
The clinical evaluation focuses on identifying the underlying cause and determining the degree of kidney dysfunction.
No.
Kidney disease in someone with diabetes may have another underlying cause.
Examples include:
IgA nephropathy.
Lupus nephritis.
Other glomerular diseases.
Urinary obstruction.
Certain medication-associated kidney disorders.
Inherited kidney conditions.
Sometimes more than one cause contributes to kidney dysfunction.
An alternative or additional diagnosis may be considered when there is:
Rapidly declining eGFR.
Rapidly increasing or substantial proteinuria.
Blood in urine with concerning microscopic findings.
Active urinary sediment or cellular casts.
Sudden changes in kidney function.
Nephrotic syndrome.
A clinical pattern that does not fit the expected course of diabetic kidney disease.
The absence of diabetic retinopathy may also contribute to diagnostic assessment, particularly in certain people with type 1 diabetes, but it does not independently determine the cause.
Additional investigations or kidney biopsy may be considered when findings are atypical.
Both conditions may develop without symptoms in the early stages.
As kidney dysfunction progresses, possible findings include:
Persistent foamy urine may sometimes be associated with increased urinary protein.
However, foam alone does not confirm kidney disease.
Fluid retention or substantial urinary protein loss may contribute to swelling.
Swelling can also result from heart, liver, vascular or other medical conditions.
Fatigue may occur with reduced kidney function, anaemia or other associated conditions.
It is not specific to CKD.
Hypertension can contribute to kidney damage, while kidney dysfunction may make blood pressure more difficult to control.
Some individuals experience changes in urine volume or frequency.
However, such changes can also occur because of high blood glucose and urinary tract disorders.
These symptoms may occur in more advanced kidney dysfunction but can have several unrelated causes.
Important: The absence of symptoms does not exclude CKD or diabetic kidney disease.
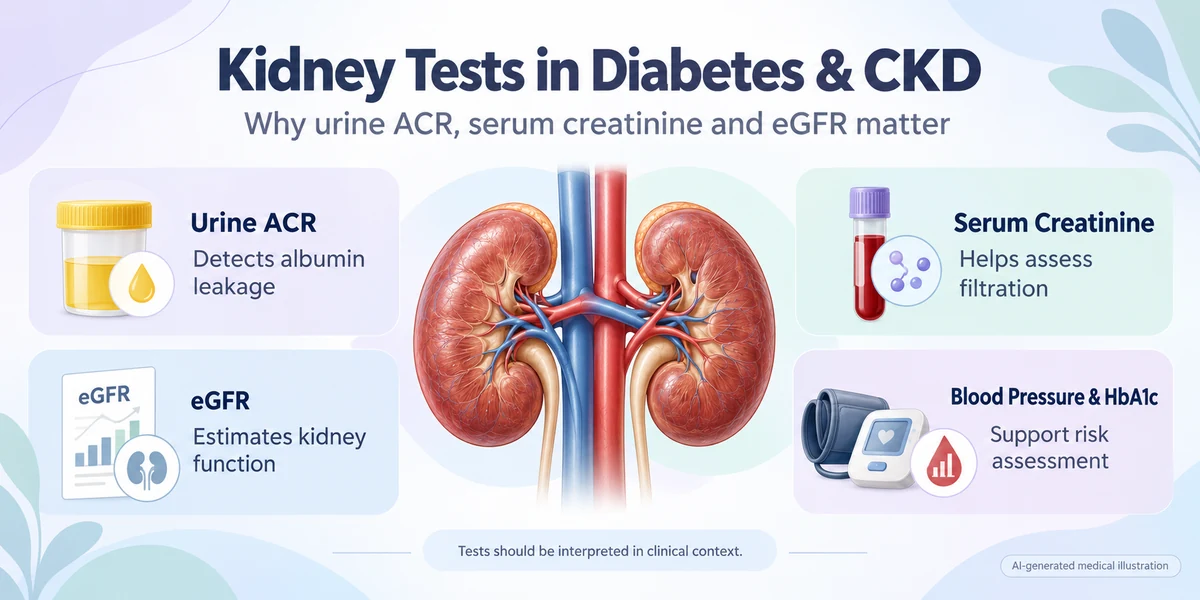
Kidney evaluation commonly includes both blood and urine investigations.
Serum creatinine measures the concentration of creatinine in blood.
It helps estimate kidney filtration but does not directly detect albumin leakage.
Creatinine levels are influenced by muscle mass, certain medicines and other factors.
A normal serum creatinine result does not rule out early kidney abnormalities.
eGFR estimates how effectively the kidneys filter blood.
It is commonly calculated using serum creatinine, age and sex through a validated equation.
Changes in eGFR over time may help assess kidney function.
Urine ACR measures albumin relative to creatinine in urine.
It can identify increased albumin leakage even when serum creatinine remains within the laboratory reference range.
A single high urine ACR does not automatically confirm CKD or identify the cause.
Urinalysis may help detect blood, protein and other urine abnormalities.
Microscopic examination may provide evidence suggesting glomerular disease or another urinary condition.
Blood pressure measurement helps evaluate hypertension and associated kidney and cardiovascular risks.
HbA1c provides information about average blood glucose over approximately the previous two to three months.
It supports diabetes management but is not a direct kidney function test.
Ultrasound may be considered when structural abnormalities, obstruction or other anatomical conditions are suspected.
Not every patient requires every investigation.
Read more about Kidney Tests Explained.
Urine ACR is commonly reported in milligrams of albumin per gram of creatinine (mg/g).
| Urine ACR (mg/g) | Category | General interpretation |
|---|---|---|
| Below 30 | A1 | Normal to mildly increased |
| 30–299 | A2 | Moderately increased albuminuria |
| 300 or above | A3 | Severely increased albuminuria |
A2 is the category previously called microalbuminuria.
A3 is sometimes referred to using the older term macroalbuminuria.
However, current clinical classification generally prefers A1, A2 and A3.
No.
Increased urine albumin may be associated with diabetes, hypertension, glomerular disease or temporary medical conditions.
Factors such as fever, urinary infection, strenuous exercise, markedly elevated blood glucose and menstruation-related specimen contamination may influence urine test results.
Persistent albuminuria requires appropriate interpretation.
For more details, see Urine ACR Test Explained.
CKD is classified partly according to eGFR.
| eGFR (mL/min/1.73 m²) | Category | General interpretation |
|---|---|---|
| 90 or above | G1 | Normal or high |
| 60–89 | G2 | Mildly decreased |
| 45–59 | G3a | Mildly to moderately decreased |
| 30–44 | G3b | Moderately to severely decreased |
| 15–29 | G4 | Severely decreased |
| Below 15 | G5 | Kidney failure range |
No.
G1 and G2 do not establish chronic kidney disease without other evidence of persistent kidney damage.
For example, someone with eGFR above 90 and persistently increased urine ACR may meet CKD criteria when chronicity is established.
Conversely, a person with eGFR above 90 and no other markers of kidney damage may not have CKD.
No.
An eGFR below 15 is within the G5 category, but dialysis decisions depend on symptoms, complications, laboratory results, fluid balance, patient circumstances and clinical assessment.
Dialysis is not automatically initiated because of one eGFR number.
Yes.
Some people with diabetic kidney disease have increased urine albumin while serum creatinine remains within the laboratory reference range.
This can occur when the kidney’s filtering barrier is affected before a substantial reduction in overall filtration develops.
However, reduced eGFR may also develop without increased albuminuria.
Urine ACR and eGFR provide complementary information.
Learn more about Diabetic Kidney Disease With Normal Creatinine.
CKD generally requires evidence of kidney abnormalities persisting for at least three months.
Evidence may include:
– Persistently reduced eGFR.
– Persistent albuminuria.
– Certain urine sediment abnormalities.
– Structural abnormalities.
– Other recognised markers of kidney damage.
Previous laboratory reports can help establish chronicity.
When earlier results are unavailable, repeat testing or additional assessment may be needed.
A single abnormal creatinine, eGFR or urine ACR does not automatically establish CKD.
Rapidly changing kidney function may indicate acute kidney injury or another condition requiring earlier evaluation.
The American Diabetes Association Standards of Care in Diabetes—2026 recommends kidney assessment using urine ACR and eGFR.
People with type 1 diabetes generally undergo annual testing after diabetes has been present for five years or longer.
Earlier evaluation may be appropriate in selected circumstances.
People with type 2 diabetes generally undergo urine ACR and eGFR testing at least annually beginning at diagnosis.
Urine albumin and eGFR may be monitored approximately one to four times per year, or more frequently when clinically indicated.
The frequency depends on CKD stage, progression risk, medical treatment and associated conditions.
Children and adolescents require age-appropriate recommendations.
Management depends on the underlying cause, kidney function, albuminuria, medical history and associated complications.
For people with diabetes, appropriate blood glucose management is an important part of reducing kidney-related risks.
HbA1c targets should be individualised.
Blood pressure control can reduce kidney and cardiovascular risk.
Target blood pressure depends on individual clinical circumstances and treatment tolerance.
Certain medicines may provide kidney or cardiovascular benefits in eligible patients.
These include:
ACE inhibitors and ARBs: May be appropriate for selected patients with hypertension and albuminuria.
SGLT2 inhibitors: May reduce kidney disease progression and cardiovascular risk in eligible patients with type 2 diabetes and CKD, as well as selected patients with CKD from other causes.
GLP-1 receptor agonists: Certain agents may provide cardiovascular and kidney-related benefits in selected people with type 2 diabetes.
Other treatments may be considered based on the underlying disease.
These medicines have potential adverse effects, contraindications and monitoring requirements.
Patients should not start, stop or change prescribed medicines independently.
Individualised advice may include:
Reducing excessive sodium intake.
Avoiding tobacco.
Appropriate physical activity.
Weight management when indicated.
Reviewing over-the-counter medicines and supplements.
Following a balanced eating pattern suitable for kidney function.
Protein, potassium, phosphorus and fluid restrictions are not automatically necessary for everyone with CKD.
Dietary recommendations depend on laboratory findings, nutritional needs and other medical conditions.
CKD caused by glomerulonephritis, inherited disorders, obstruction or another specific condition may require different investigations and treatment.
This is one reason identifying the underlying cause is important.
Some early abnormalities, including increased urinary albumin, may improve with appropriate management.
However, established chronic kidney scarring may not be fully reversible.
A decrease in albuminuria or improvement in creatinine does not necessarily establish that an underlying chronic kidney disease has been cured.
The aim of care is to address reversible factors, manage the underlying disease, preserve kidney function when possible and reduce complications.
No treatment guarantees complete recovery or prevention of kidney failure.
Further kidney assessment may be appropriate when:
Urine ACR is severely increased or rises rapidly.
eGFR declines progressively.
Kidney function changes unexpectedly.
Blood and protein are present together in urine.
Active urine sediment suggests glomerular disease.
Blood pressure remains difficult to control with kidney abnormalities.
Significant electrolyte disturbances occur.
Advanced CKD is suspected.
The underlying cause of kidney disease remains uncertain.
Not every mildly elevated urine ACR result requires immediate specialist referral.
The decision depends on persistence, severity, progression risk and clinical findings.
Seek emergency medical care for:
Severe breathlessness.
Chest pain.
Confusion or loss of consciousness.
Seizures.
Very little or no urine output with significant illness.
– Rapidly worsening swelling accompanied by breathing difficulty.
Severe flank pain with fever, visible blood in urine or rapidly changing kidney function may also require timely evaluation.
These symptoms have several possible causes and should not automatically be attributed to diabetic nephropathy or CKD.
The following information may be useful during clinical assessment.
| Report or information | Why it may be useful |
|---|---|
| Previous serum creatinine | Helps identify changes over time |
| eGFR | Estimates kidney filtration |
| Urine ACR | Assesses albumin leakage |
| Urinalysis | May identify blood, protein or other abnormalities |
| Blood pressure records | Helps evaluate hypertension |
| HbA1c or glucose records | Supports diabetes management assessment |
| Current medication list | Supports medicine safety review |
| Previous imaging | May provide structural kidney information |
| Medical and family history | May help identify underlying causes |
| Previous kidney test results | Helps establish chronicity and progression |
Not every person requires all these investigations.
Not exactly. Diabetic nephropathy refers to kidney damage attributed to diabetes, while CKD includes persistent kidney abnormalities caused by diabetes or many other conditions.
Yes. Hypertension, glomerular disease, inherited kidney conditions and other disorders can cause CKD.
No. Kidney disease in a person with diabetes may result from diabetes, another condition or multiple contributing causes.
No. Proteinuria can occur with hypertension, glomerular disorders, certain temporary conditions and other causes.
Urine ACR, serum creatinine, eGFR, urinalysis and relevant clinical investigations help assess kidney damage and filtration.
Some abnormalities may improve with treatment, but established chronic kidney damage may not be fully reversible.
No. Many people with CKD do not need dialysis. The need depends on kidney function, symptoms, complications and individual clinical assessment.
Diabetic nephropathy and chronic kidney disease are related but different medical concepts.
Diabetic nephropathy describes kidney damage attributed to diabetes, while CKD is a broader diagnosis covering persistent kidney abnormalities from different causes.
Diabetes is an important cause of CKD, but the presence of diabetes does not automatically establish the cause of kidney dysfunction.
Urine ACR, eGFR, previous laboratory results and clinical assessment help determine the type, severity and progression of kidney disease.
Appropriate monitoring and individualised management may reduce the risk of complications, but outcomes vary between individuals.
Medical Information: Dr. Jyoti Bansode | MBBS, MD Medicine, DM Nephrology | Medical Registration No.: 2011/06/1863 | Maharashtra Medical Council (MMC).
Medical Review Status: Pending review and approval by Dr. Jyoti Bansode.
Medical Disclaimer: Website content and visuals are for general informational, educational and representational purposes only, may not reflect individual patient conditions or outcomes, and do not replace personalised medical advice, diagnosis or clinical assessment.
Plot no 70, Moreshwar Heritage, Sector 5, Ulwe, Navi Mumbai, Maharashtra 410206
For Booking: +91 8591009591
Chat With Us
Mini Sea Shore Road, Juhu Nagar, Sector 10A, Vashi, Navi Mumbai, Maharashtra 400703
Chat With Us