
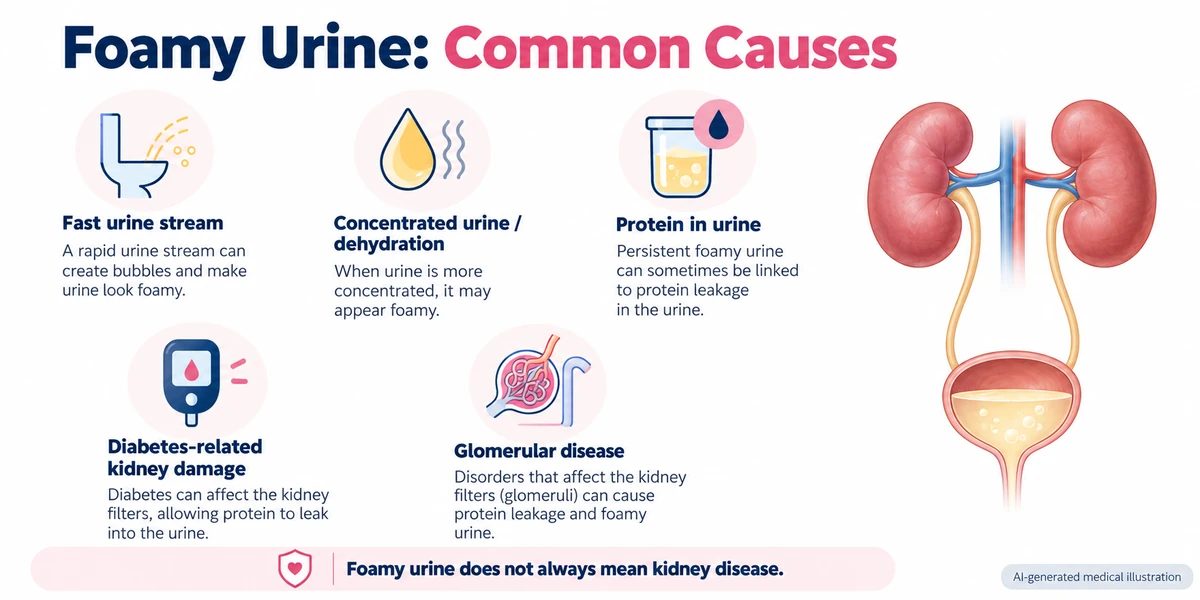
Foamy urine does not always indicate kidney disease. Bubbles can sometimes appear because of forceful urination, concentrated urine or substances in toilet water. However, persistent or repeatedly foamy urine may occasionally be associated with excess protein in urine, known as proteinuria.
Proteinuria can be a sign of kidney damage, but urine appearance alone cannot confirm or exclude kidney disease. Urinalysis, urine albumin-to-creatinine ratio (uACR) and blood tests for kidney function can help identify abnormalities.
Occasional bubbles in urine do not necessarily mean kidney disease.
Persistent foam may sometimes be associated with proteinuria or albuminuria.
Diabetes, hypertension and glomerular diseases can cause protein leakage into urine.
Urine ACR and eGFR are important tests for evaluating kidney health.
Early chronic kidney disease may have no noticeable symptoms.
Persistent foamy urine with swelling, blood in urine or abnormal kidney tests warrants medical evaluation.
Foamy urine refers to urine that produces visible bubbles or foam after entering the toilet.
The appearance may vary depending on:
Urine flow: A strong stream may create temporary bubbles.
Urine concentration: Concentrated urine may sometimes appear more bubbly.
Toilet water: Cleaning agents and other substances may produce foam.
Urine composition: Increased urinary protein can sometimes contribute to persistent foam.
Foamy urine is a visible finding, not a medical diagnosis.
The National Kidney Foundation identifies foamy urine as a possible finding in certain kidney conditions associated with proteinuria.
Several factors can affect urine appearance. Some are temporary, while others may require investigation.
A strong urine stream can trap air when urine strikes the toilet water.
Possible features include:
Bubbles appearing immediately after urination.
Foam that disappears relatively quickly.
No associated urinary or general symptoms.
This can occur without underlying kidney disease.
Urine may become more concentrated when fluid intake decreases or fluid loss increases.
Possible contributing factors include:
Inadequate fluid intake.
Excessive sweating.
Vomiting or diarrhoea.
Increased fluid loss during illness.
Concentrated urine can sometimes influence its appearance. However, persistent foam should not automatically be attributed to dehydration.
Proteinuria occurs when an increased amount of protein passes into urine.
Healthy kidney filters normally prevent most blood proteins, including albumin, from entering urine. Damage to these filtering structures may allow proteins to leak into the urine.
Important points include:
Proteinuria may indicate kidney damage.
Significant protein leakage can sometimes produce persistent foam.
Proteinuria may occur without visible urine changes.
Urine appearance cannot reliably measure protein levels.
The NIDDK guide to albuminuria explains why albumin in urine is an important marker of kidney health.
Read more about Protein in Urine: Causes and Kidney Health.
Long-term diabetes can affect the small blood vessels and filtering structures within the kidneys.
As kidney damage develops:
Albumin may leak into urine.
Kidney function may remain relatively preserved during early disease.
Abnormalities may occur without noticeable symptoms.
Kidney filtration may decline over time in some people.
Not everyone with diabetes develops kidney disease. Regular testing is more reliable than monitoring urine appearance alone.
Long-standing hypertension can damage kidney blood vessels.
Some people develop albuminuria or reduced kidney function as a result of kidney damage associated with high blood pressure.
However, hypertension does not necessarily cause foamy urine, and foam alone cannot establish a connection.
The glomeruli are tiny filtering structures within the kidneys.
Diseases affecting these structures may lead to:
Protein in urine.
Blood in urine.
Swelling.
High blood pressure.
Changes in kidney function.
Examples include minimal change disease, focal segmental glomerulosclerosis and membranous nephropathy.
These conditions have different causes, treatments and outcomes. Diagnosis requires appropriate medical investigations.
No. Foamy urine alone does not confirm kidney disease.
Occasional bubbles may occur for harmless reasons.
However, medical assessment may be appropriate when foamy urine:
Occurs repeatedly or persists.
Is associated with abnormal urine protein results.
Appears alongside swelling.
Occurs with visible blood in urine.
Is accompanied by reduced urine output.
Occurs in someone with diabetes or hypertension.
Is associated with abnormal kidney function tests.
Early kidney disease may also occur without foamy urine.
Therefore, both symptoms and laboratory findings must be considered.
Foamy urine may warrant greater attention when accompanied by other abnormalities.
Possible warning signs include:
Swelling: Puffiness around the eyes or swelling in the feet and ankles.
Blood in urine: Pink, red or brown urine.
High blood pressure: Persistent or difficult-to-control hypertension.
Urination changes: Unexplained changes in frequency or urine volume.
Fatigue: Persistent tiredness or weakness.
Fluid retention: Unexplained weight gain associated with swelling.
Abnormal kidney tests: Reduced eGFR, elevated creatinine or increased urine albumin.
These findings are not specific to kidney disease. Medical assessment is needed to determine their cause.
Certain conditions increase the likelihood of kidney abnormalities.
These include:
Diabetes mellitus.
High blood pressure.
Cardiovascular disease.
Previous kidney injury.
Family history of kidney failure.
Known glomerular disorders.
Certain autoimmune conditions.
Persistent albuminuria or proteinuria.
People with these risk factors may require kidney screening according to their individual clinical circumstances.
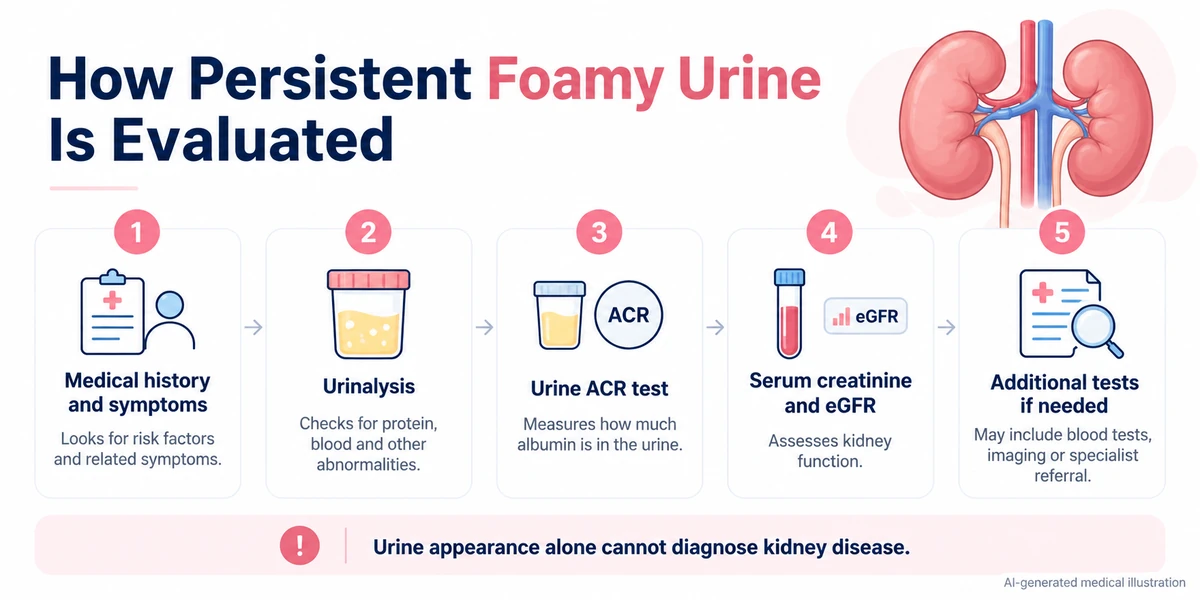
Evaluation generally begins with a review of symptoms, medical history, medicines, blood pressure and previous test results.
Depending on the findings, a healthcare professional may recommend urine and blood investigations.
Urinalysis examines a urine sample for abnormalities.
It may help detect:
Protein.
Blood.
Possible signs of urinary tract infection.
Other findings requiring investigation.
A urine dipstick may detect protein, but additional testing may be necessary to quantify the amount.
The urine ACR test compares albumin with creatinine in a urine sample.
It is used to:
Detect albuminuria.
Assess possible kidney damage.
Monitor albumin levels over time.
Help classify kidney disease risk alongside eGFR.
Understanding urine ACR results
| Urine ACR (mg/g) | Interpretation |
|---|---|
| Below 30 | Normal to mildly increased |
| 30–299 | Moderately increased |
| 300 or above | Severely increased |
An abnormal result may need confirmation because temporary factors can affect urinary albumin.
These may include:
Fever.
Urinary tract infection.
Intense exercise.
Temporary illness or other clinical factors.
For additional information, read about the Urine ACR Test.
Serum creatinine is a blood marker used to estimate kidney filtration.
The estimated glomerular filtration rate (eGFR) helps assess how effectively the kidneys filter blood.
These tests can help identify:
Reduced kidney filtration.
Changes in kidney function over time.
The need for additional investigations.
Kidney disease progression in some patients.
Serum creatinine and eGFR results should be interpreted alongside urine findings and medical history.
The NIDDK guide to kidney disease tests and diagnosis provides further information on kidney assessment.
A urine protein-to-creatinine ratio may be recommended in certain situations.
Unlike urine ACR, which measures albumin, uPCR helps estimate total urine protein.
The choice of test depends on the suspected condition and clinical findings.
Additional investigations may include:
Kidney ultrasound to assess kidney structure.
Further blood tests when systemic disease is suspected.
Additional urine studies.
Kidney biopsy in selected cases.
A kidney biopsy is not routinely performed for foamy urine alone. It may be considered when clinical findings suggest a kidney disorder requiring tissue examination.
Kidney disease cannot be diagnosed from one symptom or a single isolated abnormal result in every case.
Healthcare professionals consider:
Urine albumin or protein levels.
eGFR.
Previous laboratory results.
Blood pressure.
Diabetes and other medical conditions.
Evidence of persistent kidney abnormalities.
Chronic kidney disease generally requires abnormalities of kidney structure or function to be present for at least three months.
An eGFR below 60 mL/min/1.73 m² that persists for at least three months is one criterion for CKD.
Persistent albuminuria can also indicate CKD even when eGFR is 60 or higher.
The KDIGO CKD Evaluation and Management Guideline explains how kidney disease is assessed using filtration and albuminuria categories.
Treatment depends on the underlying cause.
Temporary bubbles caused by urine flow or toilet water may not require treatment.
Management may include:
Blood pressure management.
Individualised diabetes care.
Kidney-protective medicines when appropriate.
Monitoring of urine protein and kidney function.
Treatment of specific kidney diseases.
Dietary adjustments according to medical needs.
Some medicines can reduce albuminuria or slow kidney disease progression in eligible patients.
However, treatments have limitations, may cause side effects and require individual medical assessment. No treatment guarantees complete recovery.
General measures that may support kidney health include:
Following an individualised diabetes management plan when applicable.
Monitoring blood pressure when recommended.
Maintaining fluid intake appropriate to personal medical needs.
Following dietary advice based on kidney function and other health conditions.
Avoiding unnecessary medicines or supplements that may affect the kidneys.
Completing recommended blood and urine tests.
Do not begin a very high-protein diet or make major dietary changes without appropriate guidance if significant kidney disease is present.
Avoid assuming that urine appearance alone identifies the cause.
In particular:
Do not drink excessive water in an attempt to treat proteinuria.
Do not use unverified kidney-cleansing remedies.
Do not stop prescribed medicines without medical advice.
Do not assume all foam indicates protein leakage.
Do not ignore persistent proteinuria or worsening kidney function results.
Fluid intake and medication recommendations vary depending on the person’s health conditions.
Foamy urine itself does not damage the kidneys.
The concern is whether there is an underlying condition causing persistent protein leakage.
Depending on the cause, untreated kidney disease may be associated with:
Increasing albuminuria or proteinuria.
Declining kidney function.
High blood pressure.
Fluid retention.
Increased cardiovascular risk.
Progression to advanced kidney disease in some patients.
These complications are not inevitable. The risk depends on the underlying condition and individual clinical circumstances.
Medical evaluation is appropriate when foamy urine repeatedly occurs, particularly with:
Persistent abnormal urine protein results.
Visible blood in urine.
Swelling in the feet, ankles or around the eyes.
Abnormal creatinine or eGFR results.
High blood pressure.
Diabetes or a known kidney condition.
Significant changes in urination.
A primary care physician may initiate the evaluation, and nephrology assessment may be appropriate depending on the findings.
Seek urgent medical attention for severe breathlessness, chest pain, confusion, very low or absent urine output, or rapidly worsening symptoms.
Occasional bubbles may occur because of forceful urination or other temporary factors. Persistent changes may require urine testing.
Dehydration concentrates urine, which can increase foam, but the foam typically clears quickly; persistent foam still warrants testing.
Any visible blood (hematuria) should prompt a medical visit within 24‑48 hours to rule out infection, stones, or kidney disease.
Some supplements, especially high‑dose vitamin C or protein powders, can temporarily increase urine protein, but persistent foam still requires evaluation.
Reducing sodium can lower blood pressure and reduce kidney strain, which may help lessen protein leakage over time.
Adequate hydration may help when urine is concentrated, but drinking extra water does not treat proteinuria or underlying kidney disease.
Foamy urine is a common observation that does not automatically indicate kidney disease.
Occasional bubbles may occur for temporary reasons, while persistent or recurrent foam can sometimes be associated with excess protein in urine.
Urinalysis, urine ACR and kidney function tests provide more useful information than urine appearance alone.
When abnormalities persist, medical evaluation can help identify the cause and determine whether monitoring or treatment is appropriate.
Medical Information: Dr. Jyoti Bansode, MBBS, MD Medicine, DM Nephrology | Medical Registration No.: 2011/06/1863 | Maharashtra Medical Council (MMC).
Disclaimer: General website information is educational and does not replace individual medical advice. Treatment suitability and clinical decisions require clinical assessment
Plot no 70, Moreshwar Heritage, Sector 5, Ulwe, Navi Mumbai, Maharashtra 410206
For Booking: +91 8591009591
Chat With Us
Mini Sea Shore Road, Juhu Nagar, Sector 10A, Vashi, Navi Mumbai, Maharashtra 400703
Chat With Us