+91 8691888178 / 8850999397 dr.jyotibansode.01@gmail.com Monday to Saturday : 05:00PM TO 06:00PM

How to Protect Kidneys with Diabetes – Practical Daily Tips

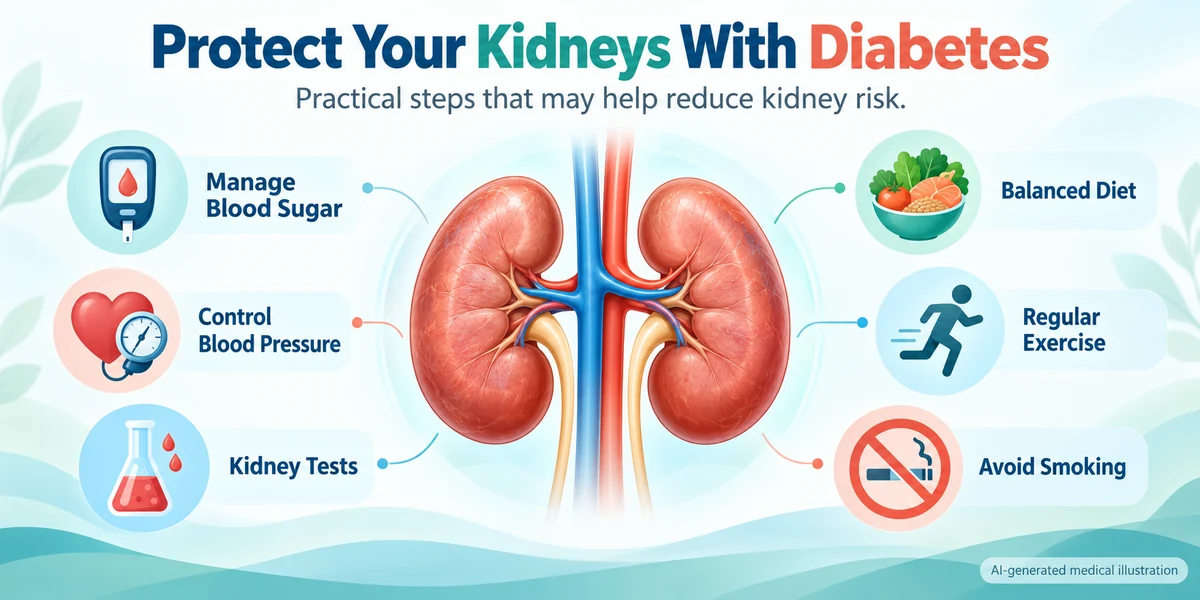
Protecting kidney health with diabetes involves appropriate blood glucose management, blood pressure control, regular kidney tests, a balanced diet, physical activity and safe use of medicines. These measures can reduce the risk of diabetes-related kidney complications, although no strategy guarantees complete prevention. Diabetes can affect the kidneys gradually, often without noticeable symptoms. Kidney damage may sometimes be detected through an increased urine albumin-to-creatinine ratio (uACR) before a substantial reduction in kidney filtration occurs. Regular assessment using urine ACR and estimated glomerular filtration rate (eGFR) is important because normal serum creatinine alone does not always exclude early kidney disease. This article explains practical steps that may help people with diabetes maintain kidney health, recognise potential risks and understand when additional medical evaluation may be appropriate. How Does Diabetes Affect the Kidneys? The kidneys contain microscopic filtering units called nephrons. Within each nephron, tiny blood vessels form a structure called the glomerulus. These structures help remove waste products and excess fluid while retaining proteins and other substances needed by the body. Persistently elevated blood glucose can affect the blood vessels and filtering structures within the kidneys. Over time, some people develop:  – Increased albumin leakage into urine.  – Changes in kidney filtration.  – High blood pressure or difficulty controlling existing hypertension.  – Impaired fluid and electrolyte regulation.  – Chronic kidney disease. This form of kidney damage is commonly called diabetic kidney disease (DKD). However, not every person with diabetes develops kidney disease, and kidney abnormalities in someone with diabetes may have causes unrelated to diabetes. For related information, read Diabetic Kidney Disease Symptoms. Why Is Kidney Protection Important for People With Diabetes? Early diabetic kidney disease often causes no noticeable symptoms. A person may feel well even when urine albumin levels are elevated or kidney filtration has changed. Kidney disease is also associated with an increased risk of cardiovascular complications. Appropriate diabetes management and kidney monitoring may help:  – Reduce the risk of kidney damage developing.  – Identify abnormalities before noticeable symptoms appear.  – Slow kidney disease progression in eligible patients.  – Support blood pressure and cardiovascular risk management.  – Guide safer use of medicines.  – Identify complications that require medical attention. The degree of benefit varies according to individual clinical circumstances. Who Is at Greater Risk of Diabetic Kidney Disease? Several factors are associated with greater kidney-related risk in people with diabetes: Longer duration of diabetes. Persistently elevated blood glucose. High blood pressure. Cardiovascular disease. Tobacco use. Excess body weight. Family history of kidney disease. Existing albuminuria or reduced eGFR. These factors do not mean kidney disease will definitely develop. Kidney-related risk depends on the overall medical condition and changes in laboratory results over time. 10 Practical Ways to Protect Your Kidneys With Diabetes The following measures may help support kidney health and reduce associated risks. 1. Manage Blood Glucose According to Individual Targets Appropriate blood glucose management is an important part of preventing diabetes-related complications. Persistently elevated blood glucose can contribute to kidney blood vessel injury. HbA1c is a blood test that reflects average blood glucose over approximately the previous two to three months. A suitable HbA1c target depends on factors such as:  – Age.  – Type and duration of diabetes.  – Risk of low blood glucose (hypoglycaemia).  – Cardiovascular disease.  – Kidney function.  – Other medical conditions.  – Current treatment. A single HbA1c target is not appropriate for everyone. Some patients benefit from home glucose monitoring or continuous glucose monitoring, depending on their medicines and diabetes-management needs. Important: Diabetes medicines should not be adjusted independently based on one glucose reading. 2. Monitor and Manage Blood Pressure High blood pressure can damage small blood vessels in the kidneys. Diabetes and hypertension together may increase the risk of kidney and cardiovascular complications. Blood pressure assessment is therefore an important part of diabetes care. Management may involve dietary changes, physical activity, weight management and medicines when indicated. The appropriate blood pressure target depends on the individual’s medical condition, treatment tolerance and risks. Home blood pressure monitoring may be useful for some people, but daily measurement is not necessary for every patient. A healthcare professional can advise on an appropriate monitoring schedule. 3. Take Prescribed Medicines Safely Certain medicines may help reduce kidney-related risk or slow the progression of established kidney disease in eligible patients. Examples include: ACE inhibitors and angiotensin receptor blockers (ARBs): These may be appropriate for selected people with diabetes, high blood pressure and albuminuria. SGLT2 inhibitors: These may reduce kidney disease progression and cardiovascular complications in eligible people with type 2 diabetes and chronic kidney disease. GLP-1 receptor agonists: Certain medicines in this class may provide cardiovascular and kidney-related benefits in selected patients. Other medicines may also be appropriate according to the clinical condition. However, not every medicine is suitable for every person with diabetes. Possible risks can include low blood pressure, changes in kidney function, electrolyte disturbances, dehydration or other medicine-specific adverse effects. Kidney function and potassium may require monitoring during certain treatments. ACE inhibitors and ARBs should not automatically be prescribed solely to prevent CKD in people with normal blood pressure, normal urine ACR and normal eGFR. Never start, stop or change prescribed medicines without guidance from a qualified healthcare professional. 4. Reduce Excessive Salt Intake Consuming excessive sodium may contribute to high blood pressure and fluid retention. Reducing excessive dietary salt can be useful for people with diabetes, particularly when hypertension or kidney disease is present. Practical measures include:  – Limiting frequently consumed salty packaged foods.  – Reducing added salt during cooking.  – Checking sodium information on packaged foods.  -Using herbs, spices and lemon juice for flavour.  – Choosing less processed foods when practical. Some foods, such as pickles, papad, namkeen and packaged snacks, can contain substantial amounts of sodium. However, dietary recommendations must consider individual nutritional needs and medical conditions. People with advanced kidney disease may require additional dietary guidance. 5. Follow a Balanced, Kidney-Appropriate Diet A balanced eating pattern can support diabetes management, blood pressure control and overall health. Depending on individual requirements,
Diabetic Kidney Disease with Normal Creatinine – What You Need to Know

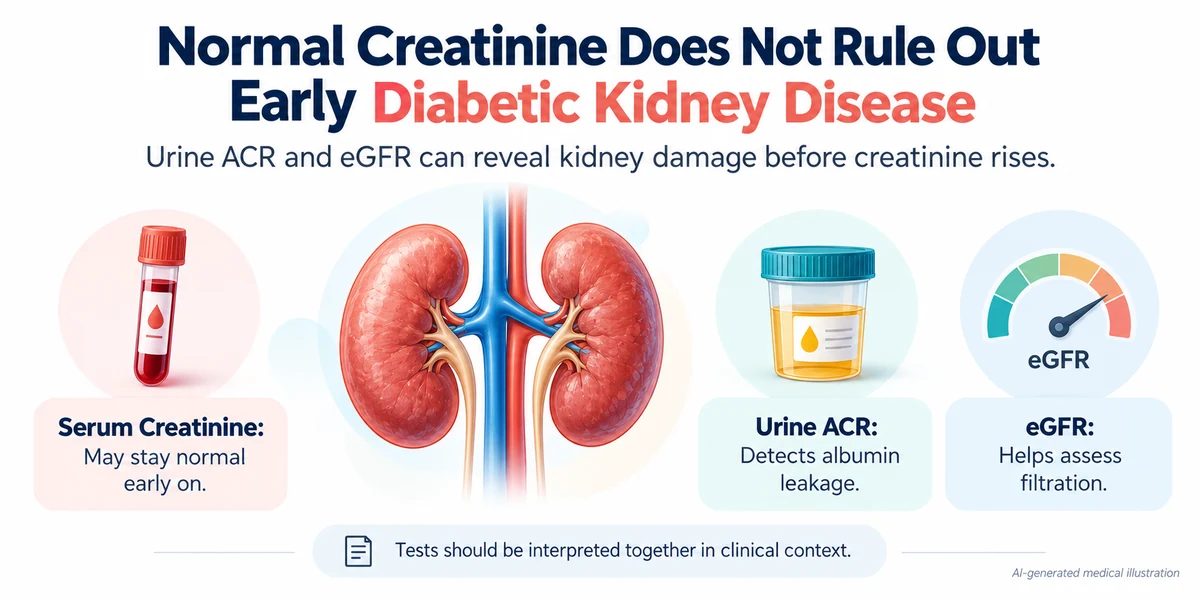
Yes. Diabetic kidney disease can develop even when serum creatinine remains within the normal laboratory range. Early kidney damage may cause increased albumin leakage into urine before a substantial decline in kidney filtration occurs. Serum creatinine alone cannot detect every form of kidney damage. Urine albumin-to-creatinine ratio (uACR) and estimated glomerular filtration rate (eGFR) provide complementary information. Some people with diabetic kidney disease may have preserved eGFR and increased urine albumin, while others may develop reduced eGFR without significantly increased albuminuria. Early diabetic kidney disease often causes no noticeable symptoms. Why Creatinine Can Remain Normal in Early Diabetic Kidney Disease Serum creatinine is a blood marker used to estimate kidney filtration. However, it does not directly measure albumin leakage or identify every form of early kidney damage. In some people with diabetes, changes in the kidney’s filtering barrier allow albumin to pass into urine while overall filtration remains relatively preserved. Creatinine levels are also influenced by age, muscle mass, diet and certain medicines. Therefore, a person may have: Serum creatinine within the laboratory reference range. Relatively preserved eGFR. Persistently increased urine ACR. This combination may indicate kidney damage, although the underlying cause and persistence of the abnormalities require clinical assessment.How Does Diabetes Affect the Kidney’s Filtering Structures? The kidneys contain microscopic filtering structures called glomeruli. Long-term exposure to elevated blood glucose can damage the small blood vessels and filtering structures within the kidneys. These changes may lead to: Injury to the glomerular filtration barrier. Increased albumin leakage into urine. Alterations in kidney filtration. Gradual decline in kidney function in some people. However, diabetic kidney disease does not follow the same pattern in everyone. Some people develop albuminuria before eGFR declines. Others may experience reduced kidney filtration without substantial albuminuria. The term moderately increased albuminuria is generally preferred over the older term microalbuminuria. Kidney test results must be interpreted alongside diabetes history, blood pressure and other clinical findings. Creatinine vs eGFR vs Urine ACR Each test answers a different question about kidney health. Understanding their roles helps catch disease early. Test What it measures Why it matters Serum Creatinine Creatinine concentration in blood Helps assess kidney filtration eGFR Estimated kidney filtration, commonly calculated using creatinine, age and sex Helps identify reduced kidney function Urine ACR Albumin relative to creatinine in urine Helps identify  Because they assess different aspects, clinicians interpret them together rather than in isolation. Can eGFR Be Normal in Early Diabetic Kidney Disease? An eGFR of 90 mL/min/1.73 m² or above does not independently confirm that the kidneys are healthy. Persistently increased urine ACR may indicate kidney damage even when eGFR is relatively preserved. However, an increased urine ACR result does not automatically establish that diabetes is the underlying cause. Repeat testing and clinical interpretation may be necessary. Current Screening Guidance for Diabetes Guidelines from the American Diabetes Association and KDIGO recommend: People with type 2 diabetes: urine ACR and eGFR testing at least once a year from the time of diagnosis. People with type 1 diabetes: begin annual kidney screening after about five years of diabetes duration, unless other risk factors call for earlier testing. Regular monitoring helps detect changes before symptoms appear. Early Warning Signs (Often Absent) Early diabetic kidney disease usually has no noticeable symptoms. When it progresses, patients may notice: Foamy or frothy urine (protein) Swelling of the feet or ankles Increasing blood pressure Fatigue or reduced energy Changes in urination frequency Nausea or loss of appetite Can a High Urine ACR Be Temporary? Transient factors can raise urine albumin, including intense exercise, fever, urinary‑tract infection, marked hyperglycaemia, menstruation, heart failure, or a sudden spike in blood pressure. One abnormal ACR result does not automatically confirm chronic kidney disease;An elevated urine ACR can sometimes be temporary. Possible contributing factors include fever, urinary tract infection, strenuous exercise, menstruation, markedly elevated blood glucose, significantly elevated blood pressure and certain acute illnesses. A single abnormal urine ACR result does not automatically establish chronic kidney disease. Repeat testing may be recommended to confirm persistent albuminuria. The timing depends on the clinical circumstances. Chronic kidney disease generally requires evidence of kidney abnormalities persisting for at least three months. What Test Results May Suggest Early Kidney Damage? Look for patterns such as: Normal serum creatinine + elevated urine ACR. Preserved eGFR + elevated urine ACR. Gradual decline in eGFR over months or years. Increasing albumin levels on consecutive ACR tests. These patterns may indicate kidney abnormalities that require further evaluation. However, they do not independently establish diabetic kidney disease. The significance depends on repeat measurements, changes over time, other possible causes and the individual’s clinical condition. What Should You Do If Creatinine Is Normal but You Have Diabetes? Discuss the following with your clinician: Request a urine ACR test. Ask for an eGFR calculation based on your latest labs. Review previous creatinine results to spot trends. Review prior urine ACR results, if available. Check your blood pressure readings. Know your most recent HbA1c level. Ask whether repeat urine testing is needed to confirm any abnormality. Inquire if your kidney‑function numbers are changing over time. When Should Nephrology Evaluation Be Considered? Nephrology evaluation may be appropriate when kidney test abnormalities are persistent, progressive, unexplained or associated with significant complications. Possible reasons include: Persistently elevated or rapidly increasing urine ACR. Progressively declining eGFR. Unexplained changes in serum creatinine. Protein and blood detected together in urine. Difficult-to-control blood pressure with kidney abnormalities. Significant swelling associated with suspected kidney disease. Abnormal electrolyte levels. Uncertainty about the underlying cause of kidney dysfunction. Suspected advanced chronic kidney disease. Not everyone with mildly increased urine ACR requires immediate specialist referral. The need for nephrology evaluation depends on the severity, persistence and overall clinical findings. For related information, read Protein in Urine: Causes and Tests and Acute and Chronic Kidney Diseases. Why Is Early Detection of Diabetic Kidney Disease Important? Early diabetic kidney disease may develop without noticeable symptoms. Urine ACR and eGFR testing can help identify kidney abnormalities before significant symptoms occur. Appropriate blood glucose management, blood pressure control, selected medicines and regular

Urine ACR Test Explained: Why Albumin in Urine Matters

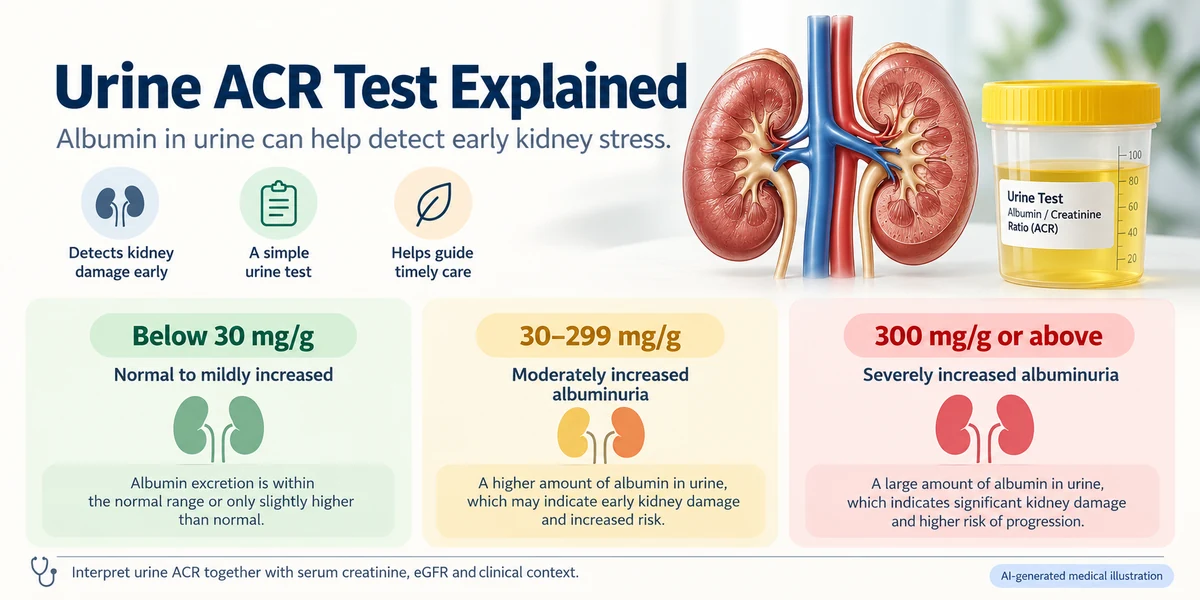
The urine albumin-to-creatinine ratio (urine ACR or uACR) test measures albumin relative to creatinine in a urine sample. It helps detect increased albumin leakage, which may be a marker of kidney damage even when serum creatinine and estimated glomerular filtration rate (eGFR) are relatively normal. A urine ACR below 30 mg/g is classified as normal to mildly increased, 30–299 mg/g as moderately increased, and 300 mg/g or above as severely increased albuminuria. However, a single high urine ACR result does not automatically confirm chronic kidney disease. Infection, fever, strenuous exercise and other medical conditions may temporarily affect urinary albumin levels. This guide explains why urine ACR testing is performed, how samples are collected, what the results mean and when further evaluation may be necessary. What Is a Urine ACR Test? A urine ACR test measures two substances in urine: Albumin: A protein normally found in the bloodstream that helps maintain fluid balance and performs other important functions. Creatinine: A waste product formed through muscle metabolism and excreted through the kidneys. The laboratory compares the amount of albumin with the amount of creatinine and reports the ratio. The test is commonly expressed in milligrams of albumin per gram of creatinine (mg/g). Because urine concentration changes throughout the day, using a ratio helps reduce the effect of urine dilution on the result. Urine ACR provides information about albumin leakage, but it does not directly measure the kidneys’ overall filtering rate. How Do Healthy Kidneys Prevent Albumin Loss? The kidneys contain microscopic filtering units called nephrons. Within each nephron, a structure called the glomerulus filters blood, allowing waste products and excess fluid to pass into the forming urine while retaining most larger proteins. The kidney tubules also help reabsorb certain filtered substances. Healthy kidneys normally allow only small amounts of albumin to appear in urine. When certain diseases affect kidney filtering structures, urinary albumin excretion may increase. This condition is called albuminuria. However, albuminuria can also occur temporarily during illness or other physiological changes. Why Is the Urine ACR Test Important? Urine ACR helps identify abnormalities that may not be detected through serum creatinine alone. Its clinical uses include: Detecting increased albumin leakage. Evaluating possible kidney damage. Assessing kidney-related risk in people with diabetes. Supporting the evaluation of hypertension-related kidney abnormalities. Helping classify chronic kidney disease. Monitoring changes in albuminuria over time. Supporting assessment of kidney and cardiovascular risk. Urine ACR is particularly useful when interpreted alongside eGFR. An elevated urine ACR is a clinical finding, not a diagnosis of a particular kidney disease. What Is the Normal Urine ACR Range? Urine ACR results are classified into three albuminuria categories. Urine ACR (mg/g) Category General interpretation Below 30 A1 Normal to mildly increased 30–299 A2 Moderately increased albuminuria 300 or above A3 Severely increased albuminuria A1: Below 30 mg/g This category is described as normal to mildly increased albuminuria. A result in this range is generally reassuring regarding albumin leakage, but it does not exclude all types of kidney disease. Other abnormalities, including reduced eGFR, may still require evaluation. A2: 30–299 mg/g This category indicates moderately increased albuminuria. The older term microalbuminuria is sometimes used to describe this range. Persistent albuminuria in this category may indicate kidney damage, particularly in people with diabetes or hypertension. However, the underlying cause must be determined clinically. A3: 300 mg/g or Above This category indicates severely increased albuminuria. It may be associated with a higher risk of kidney disease progression and cardiovascular complications. Significant or persistent abnormalities may require additional investigations. Does a High ACR Mean Kidney Failure? No. A high urine ACR means that increased albumin has been detected in urine. It does not independently determine the severity of kidney filtration impairment or establish that kidney failure is present. eGFR, previous results, symptoms and other medical findings are needed for a broader assessment. What Is the Difference Between Albuminuria and Proteinuria? Albuminuria and proteinuria are related but different terms. Albuminuria: Increased urinary excretion of albumin. Proteinuria: Increased urinary excretion of protein, which may include albumin and other proteins. Urine ACR measures albumin relative to creatinine. Urine protein-to-creatinine ratio (PCR or UPCR) measures total protein relative to creatinine. The choice of test depends on the suspected medical condition. Some kidney disorders involve proteins other than albumin, so urine ACR alone may not identify every type of proteinuria. How Is the Urine ACR Test Performed? Urine ACR usually requires a single urine specimen. Step 1: Urine Sample Collection A urine sample is collected in a container provided by the laboratory. Patients should follow the laboratory’s hygiene and collection instructions. A clean-catch midstream sample may be requested when appropriate. Step 2: Laboratory Measurement The laboratory measures urine albumin and urine creatinine. Step 3: Ratio Calculation The albumin-to-creatinine ratio is calculated. A simplified formula is: Urine ACR (mg/g) = Urine albumin (mg/dL) ÷ Urine creatinine (g/dL) Both measurements must be expressed in compatible units. Step 4: Clinical Interpretation The result is interpreted alongside previous measurements, serum creatinine, eGFR, medical history and other clinical findings. A single test does not always establish a chronic condition. Is a First-Morning Urine Sample Better? A first-morning urine sample is often preferred, particularly when confirming an abnormal result. It may reduce variation associated with daytime activity and changes in urine concentration. However, a random spot urine sample is also commonly accepted for initial screening. When urine ACR is elevated on a random sample, a first-morning specimen may be recommended for confirmation. Is a 24-Hour Urine Collection Necessary? Usually not. Spot urine ACR testing is commonly used for routine albuminuria assessment. A 24-hour urine collection may be considered in selected circumstances when more detailed measurement is clinically necessary. Do You Need to Fast Before a Urine ACR Test? Fasting is not routinely required for urine ACR testing alone. However, other blood or urine tests performed at the same time may have different preparation requirements. Patients should follow the instructions provided by the laboratory or healthcare professional. How Should You Prepare for the Test? General considerations

Kidney Biopsy Preparation & Recovery: What to Expect

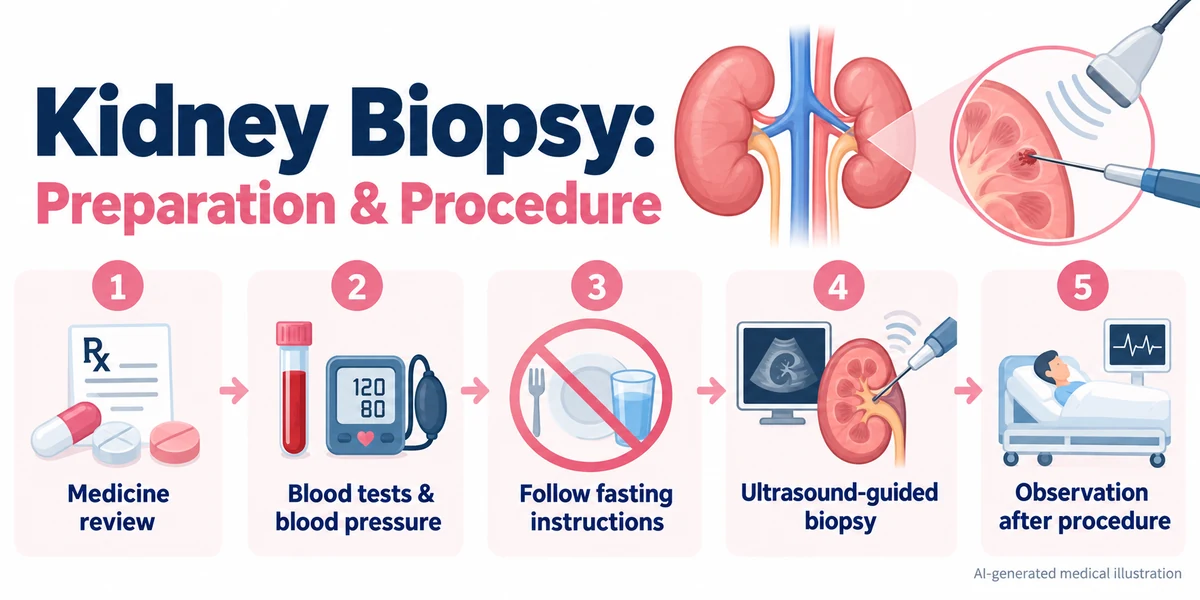
A kidney biopsy is a medical procedure in which a small tissue sample is collected from the kidney for examination under a microscope. It may help identify the cause of unexplained kidney abnormalities, assess certain types of kidney disease or evaluate a transplanted kidney when clinically indicated. Most native kidney biopsies are performed using a needle guided by ultrasound imaging. Preparation includes reviewing medicines, checking blood pressure and bleeding risk, and following instructions about eating, drinking and recovery. Although kidney biopsy can provide valuable diagnostic information, it involves risks, particularly bleeding. The decision to perform a biopsy depends on the individual’s medical condition, expected diagnostic benefit and possible complications. What Is a Kidney Biopsy? A kidney biopsy, also called a renal biopsy, involves obtaining one or more small samples of kidney tissue. The tissue is examined by a pathologist using specialised techniques to look for changes such as: – Inflammation: Signs of inflammatory activity within kidney tissue. – Scarring: Areas of long-term kidney damage. – Glomerular abnormalities: Changes affecting the kidney’s filtering units. – Tubulointerstitial abnormalities: Changes involving kidney tubules and surrounding tissue. – Blood vessel changes: Findings involving the small vessels within the kidney. – Transplant-related abnormalities: Changes that may affect the function of a transplanted kidney. These findings can sometimes clarify a diagnosis when blood tests, urine tests and imaging do not provide sufficient information. According to the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), kidney biopsies may help diagnose kidney conditions and guide clinical decisions. Why Might a Kidney Biopsy Be Recommended? A kidney biopsy is not necessary for every person with kidney disease. Doctors may consider it when the result is likely to provide information that could influence diagnosis, prognosis or treatment. 1. Unexplained Protein in Urine Persistent or significant proteinuria may indicate damage to the kidney’s filtering structures. A biopsy may be considered when the pattern or amount of protein leakage raises concern for a specific kidney disorder. 2. Blood in Urine With Other Abnormal Findings Blood in urine, particularly when accompanied by proteinuria or declining kidney function, may indicate a glomerular condition. However, not every person with blood in urine requires a kidney biopsy. 3. Unexplained Decline in Kidney Function Rapid or otherwise unexplained deterioration in kidney function may require further assessment. A biopsy may help distinguish certain inflammatory, immune-related or other kidney diseases. 4. Suspected Glomerular or Autoimmune Disease A biopsy may be used to investigate conditions such as: – IgA nephropathy. – Lupus nephritis. – Membranous nephropathy. – Certain forms of glomerulonephritis. – Other conditions affecting kidney tissue. The need for a biopsy varies according to the suspected diagnosis and available test results. 5. Evaluation of a Transplanted Kidney A biopsy may sometimes be recommended when a transplanted kidney is not functioning as expected. It can help investigate possible rejection, medication-related injury or other causes of graft dysfunction. Important: Kidney masses are generally evaluated through a separate diagnostic pathway. Biopsy of a kidney mass differs from a routine biopsy performed to investigate medical kidney disease. Is a Kidney Biopsy Always Necessary? No. Many kidney conditions can be evaluated using blood tests, urine tests, ultrasound and medical history without collecting kidney tissue. Before recommending a biopsy, doctors may consider: – Whether the likely diagnosis is already sufficiently clear. – Whether biopsy findings could change treatment. – How much protein or blood is present in urine. – The severity and pattern of kidney function changes. – Bleeding risk and other medical conditions. – Whether a safer or more suitable alternative investigation is available. The benefits and risks should be discussed before proceeding. For related information, read about Acute & Chronic Kidney Diseases. How Should You Prepare for a Kidney Biopsy? Preparation focuses on reducing avoidable risks and ensuring the procedure is appropriate. Your healthcare team will provide instructions based on your medicines, medical conditions and planned biopsy technique. 1. Review Your Medicines Tell your healthcare team about all medicines and supplements you take. These may include: – Blood-thinning medicines such as warfarin or apixaban. – Antiplatelet medicines such as aspirin or clopidogrel. – Painkillers such as ibuprofen or naproxen. – Diabetes medicines, including insulin. – Herbal products and dietary supplements. Some medicines may need to be temporarily adjusted before or after the biopsy. Do not stop aspirin, anticoagulants or any prescribed medicine without explicit instructions from the treating healthcare professional. Stopping certain medicines can increase the risk of stroke, blood clots or other complications. 2. Complete Recommended Blood and Urine Tests Before a biopsy, doctors may recommend investigations such as: – Complete blood count. – Haemoglobin level. – Platelet count. – Blood-clotting tests. – Serum creatinine and kidney function tests. – Urinalysis when indicated. – Other investigations according to clinical findings. These tests help assess bleeding risk, kidney function and possible conditions that may affect the procedure. 3. Check Blood Pressure Blood pressure is assessed before a kidney biopsy because uncontrolled hypertension may increase bleeding risk. If blood pressure is not adequately controlled, the procedure may need to be delayed until it can be performed more safely. 4. Follow Fasting Instructions Fasting requirements depend on whether sedation or anaesthesia is planned and on local procedural protocols. Some patients may be asked not to eat or drink for a specified period. Follow the exact instructions provided by your healthcare team rather than fasting independently for a fixed number of hours. 5. Inform the Team About Other Medical Conditions Before the procedure, tell the team about: – Previous unusual bleeding. – Known blood-clotting disorders. – Medicine or anaesthetic allergies. – Recent infections or fever. – Pregnancy or possible pregnancy. – Previous kidney procedures. – Other important health conditions. 6. Arrange Transportation and Support Arrange for someone to accompany you or take you home if instructed. Driving restrictions depend on the procedure, sedation and hospital discharge policy. Having a responsible adult available during early recovery may be recommended. What Happens During a Kidney Biopsy? Most biopsies performed for medical kidney disease use a percutaneous technique, meaning that the tissue sample is collected through the skin using a needle. Step 1: Patient Positioning For a native kidney biopsy, the person usually lies on their stomach or in another position selected