+91 8691888178 / 8850999397 dr.jyotibansode.01@gmail.com Monday to Saturday : 05:00PM TO 06:00PM

Diabetic Kidney Disease Symptoms: Early Signs & Tests

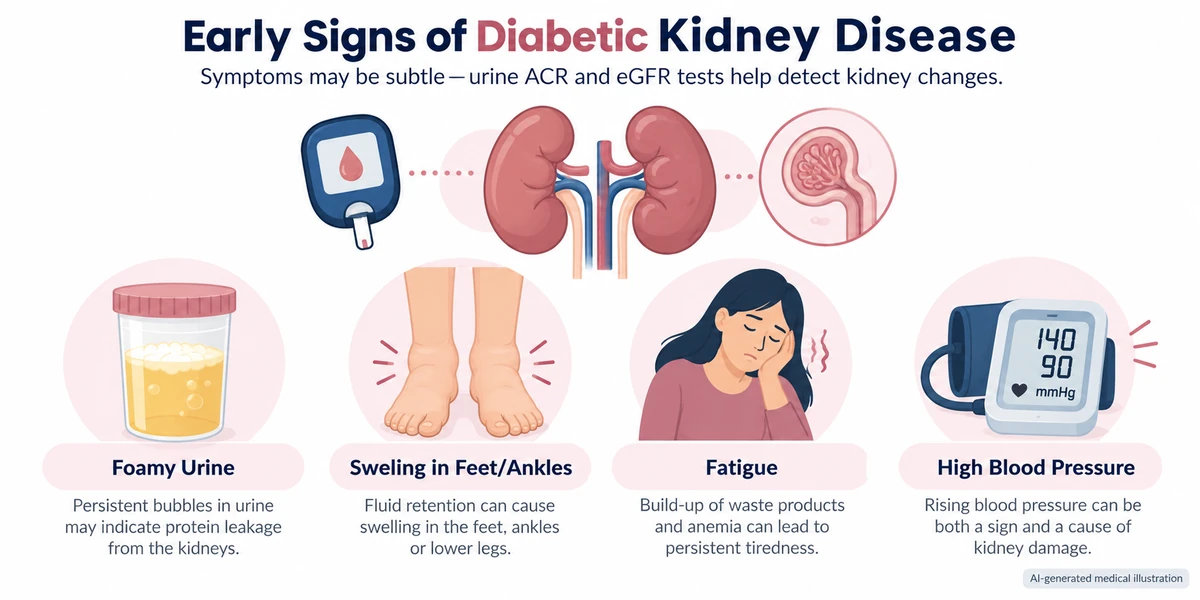
Diabetic kidney disease (DKD) is a form of kidney damage associated with diabetes. Over time, high blood glucose can affect the kidneys’ filtering structures, sometimes causing albumin to leak into urine or reducing kidney filtration. Early diabetic kidney disease often develops without noticeable symptoms. Urine albumin-to-creatinine ratio (uACR) and estimated glomerular filtration rate (eGFR) tests help identify and monitor kidney abnormalities. Not everyone with diabetes develops kidney disease. Individual risk depends on diabetes duration, blood glucose management, blood pressure and other medical factors. Quick Answer: What Are the Early Symptoms of Diabetic Kidney Disease? Early diabetic kidney disease often causes no obvious symptoms. The first signs may appear on kidney tests, such as increased albumin in urine or changes in eGFR. As kidney disease progresses, possible symptoms may include:  – Foamy or unusually bubbly urine  – Swelling in the feet, ankles or around the eyes  – Fatigue or weakness  – Changes in urination  – Nausea or reduced appetite  – Itching or muscle cramps  – Increasing or difficult-to-control blood pressure Because early diabetic kidney disease is often silent, blood and urine tests are more reliable than waiting for symptoms to appear.  What Is Diabetic Kidney Disease? Diabetic kidney disease develops when diabetes damages the small blood vessels and filtering structures inside the kidneys. The kidneys contain microscopic filtering units called glomeruli. Over time, persistently high blood glucose can damage these filters, allowing albumin to leak into the urine and gradually reducing the kidneys’ ability to remove waste from the blood. High blood pressure can further increase stress on the kidneys and accelerate kidney damage. For a broader explanation, read about diabetes and kidney diseases. Why Can Diabetic Kidney Disease Develop Without Symptoms? Kidneys have significant reserve capacity. Early kidney damage may therefore develop while a person still feels completely well. NIDDK notes that most people with diabetic kidney disease do not have symptoms in the early stages. Kidney problems are usually detected through blood and urine tests.  A patient can have: No pain + no swelling + normal-looking urine and still have albuminuria or another early kidney abnormality. Who Is at Higher Risk? Not everyone with diabetes develops diabetic kidney disease. Risk may be greater in people who have: Diabetes for many years Persistently high blood glucose High blood pressure Cardiovascular disease Smoking habits Excess body weight Family history of kidney failure Existing kidney abnormalities NIDDK identifies poor blood-glucose control and high blood pressure as especially important risk factors.  Type 1 vs Type 2 Diabetes: When Should Kidney Testing Begin? Type 1 Diabetes Current ADA 2026 recommendations advise checking urine ACR and eGFR at least annually once a person has had type 1 diabetes for five years or more.  Type 2 Diabetes People with type 2 diabetes should generally have urine ACR and eGFR checked at least once a year from diagnosis, regardless of treatment. Diabetes Journals This difference matters because type 2 diabetes may have been present for years before it is diagnosed. What Are the Earliest Signs of Kidney Damage in Diabetes? The earliest signs are often found on laboratory tests. 1. Albumin in the Urine Albumin is a protein that normally remains in the bloodstream. When the kidney filters are damaged, albumin can begin leaking into urine. This is called albuminuria. The standard test used to measure this is the urine albumin-to-creatinine ratio (UACR). For more detail, see the Urine ACR Test Guide. 2. Changes in eGFR The estimated glomerular filtration rate (eGFR) estimates how well the kidneys are filtering blood. A declining eGFR can indicate reduced kidney function. 3. Changes in Serum Creatinine Creatinine is a waste product normally filtered from the blood by the kidneys. As filtration worsens, serum creatinine may increase. However, creatinine alone is not enough to assess early diabetic kidney disease. 4. Increasing Blood Pressure High blood pressure can damage kidney blood vessels, while kidney disease can also make blood pressure more difficult to control. Patients with persistent blood-pressure problems can read more about resistant hypertension. The Two Most Important Tests for Diabetic Kidney Disease The two key kidney markers are: Urine ACR (UACR) eGFR NIDDK specifically identifies urine albumin and eGFR as the two major markers used to detect and monitor chronic kidney disease.  Urine Albumin-to-Creatinine Ratio (UACR) UACR measures albumin in urine relative to creatinine. A random spot urine sample is usually sufficient, meaning a 24-hour urine collection is generally unnecessary for routine screening.  Typical categories include: An increased urine ACR may indicate kidney damage, but one abnormal result does not automatically establish chronic kidney disease. Albumin levels can be temporarily affected by fever, infection, strenuous exercise, menstruation, markedly elevated blood glucose and other factors. Repeat testing and clinical assessment may be required to determine whether albuminuria is persistent. A UACR above 30 mg/g is considered abnormal, but the result should be interpreted with other kidney tests and, when appropriate, repeat measurements.  eGFR eGFR estimates kidney filtration. In general: 60 or above: may be within an acceptable range depending on the clinical situation Below 60: may indicate kidney disease if the reduction persists 15 or below: represents severely reduced kidney function and may indicate kidney failure The result should always be interpreted alongside urine albumin and the patient’s medical history. Can You Have Diabetic Kidney Disease with a Normal eGFR? Yes. A person may have: Normal or relatively preserved eGFR + elevated urine ACR and still have evidence of kidney damage. Albuminuria can appear before significant changes in eGFR. This is why checking only creatinine or eGFR may miss early kidney damage.  How to Understand UACR and eGFR Together How to Understand UACR and eGFR Together UACR eGFR What It May Suggest Normal Normal Current kidney markers may be reassuring. High Normal Possible early kidney damage. Normal Low Reduced kidney filtration requiring evaluation. High Low Kidney damage with reduced filtration may be present. This table is a general guide only. Diagnosis depends on repeat testing, trends over time and the patient’s overall clinical condition. Learn more about combined kidney testing
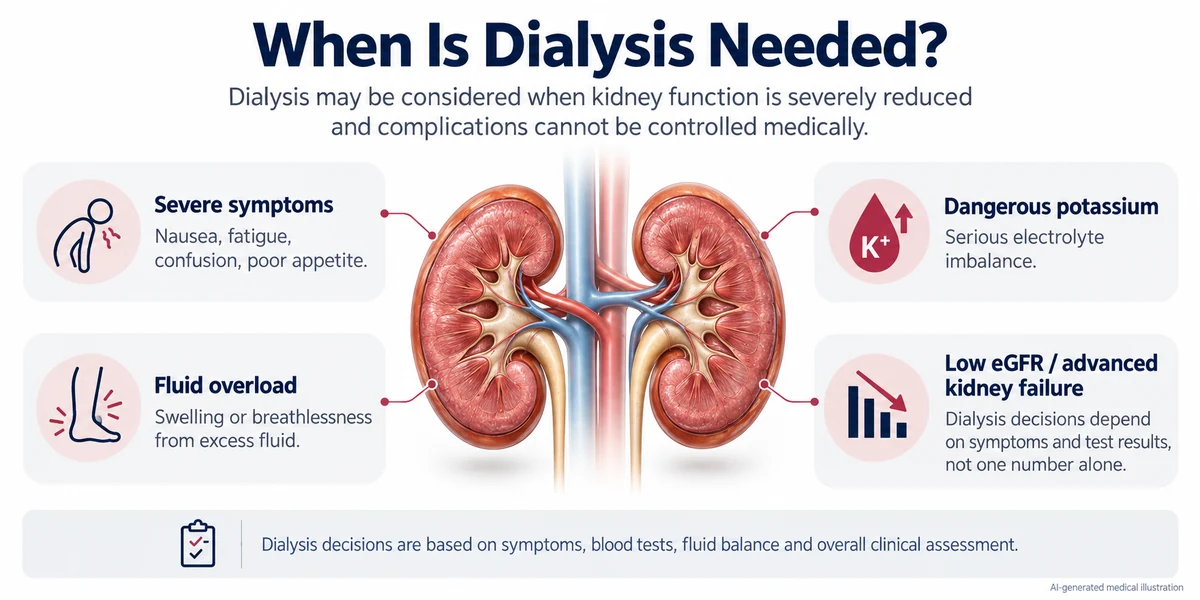
When Is Dialysis Needed? Symptoms, eGFR & Clinical Factors

Dialysis may be needed when the kidneys can no longer adequately remove waste products, control excess fluid or maintain the body’s electrolyte and acid–base balance. It is considered in advanced chronic kidney disease and, in some situations, during acute kidney injury. The decision to start dialysis is not based on a single creatinine or eGFR value. Doctors assess symptoms, laboratory results, fluid balance, nutritional status and the patient’s overall medical condition. According to KDIGO guidance, dialysis initiation often occurs when eGFR is approximately 5–10 mL/min/1.73 m² in advanced chronic kidney disease, but this is not a fixed threshold. Some patients require dialysis earlier because of serious complications, while others can continue monitoring without dialysis for a period of time. What Is Dialysis? Dialysis is a medical treatment that helps remove waste products and excess fluid from the blood when kidney function is insufficient. Healthy kidneys help: – Filter waste products from the bloodstream. – Regulate body fluid balance. – Maintain appropriate electrolyte levels. – Support the body’s acid–base balance. – Contribute to blood pressure regulation. When the kidneys become severely impaired, waste products and fluid may accumulate, leading to potentially serious complications. Dialysis replaces some of the kidneys’ filtering functions, but it does not perform every function of a healthy kidney. When Do Doctors Recommend Starting Dialysis? The decision to begin dialysis depends on the clinical condition rather than a fixed laboratory number. Dialysis may be recommended when kidney failure is associated with complications that cannot be adequately controlled through appropriate medical treatment. Important indications include: 1. Severe Symptoms of Uremia Uremia occurs when substances normally removed by the kidneys accumulate in the body. Possible symptoms include: Persistent nausea or vomiting. – Significant loss of appetite. – Unexplained weight loss. – Severe itching. – Marked fatigue or weakness. – Difficulty concentrating or confusion. These symptoms may have causes other than kidney failure. Medical evaluation is needed to determine their significance. Severe neurological complications attributable to uremia may require urgent dialysis. 2. Excess Fluid That Cannot Be Controlled When kidney function declines, excess fluid may accumulate in the body. Signs can include swelling of the legs, difficulty breathing or fluid accumulation in the lungs. Severe fluid overload, particularly when breathing is affected and medical treatment is insufficient, may require urgent dialysis. 3. Dangerous Potassium Levels Potassium is an electrolyte involved in normal muscle and heart function. When kidneys cannot remove sufficient potassium, levels may become dangerously elevated. Severe hyperkalemia can cause abnormal heart rhythms and may become life-threatening. Dialysis may be required when hyperkalemia is severe, persistent or not adequately controlled with other emergency treatments. 4. Severe Metabolic Acidosis Healthy kidneys help maintain the body’s acid–base balance. When kidney function becomes severely impaired, acid can accumulate in the bloodstream. Severe metabolic acidosis that cannot be adequately managed with other treatments may require dialysis. 5. Other Complications of Kidney Failure Additional reasons for considering dialysis include: – Uremic pericarditis, involving inflammation around the heart. – Persistent neurological symptoms attributable to kidney failure. – Progressive nutritional deterioration despite appropriate management. – Inability to control fluid status or blood pressure. Not everyone with these symptoms needs dialysis, and the urgency depends on the medical assessment. What eGFR Level Indicates That Dialysis May Be Needed? Estimated glomerular filtration rate (eGFR) is a measure used to estimate how effectively the kidneys filter blood. Lower eGFR values generally indicate reduced kidney filtration. Understanding eGFR Categories eGFR (mL/min/1.73 m²) Kidney function category 90 or above Normal or high 60–89 Mildly decreased 45–59 Mildly to moderately decreased 30–44 Moderately to severely decreased 15–29 Severely decreased Below 15 Kidney failure range An eGFR below 15 is associated with CKD category G5 when the reduction is chronic. However, an eGFR below 15 does not automatically mean dialysis must begin immediately. For many people with advanced chronic kidney disease, dialysis begins when clinically significant symptoms or complications develop, often at an eGFR around 5–10. Some people need dialysis at a higher eGFR because of serious complications. Others may remain clinically stable without immediate dialysis. The timing is individualised. Learn more about the eGFR Kidney Function Test. Does High Creatinine Mean Dialysis Is Needed? No. An elevated serum creatinine result alone does not determine the need for dialysis. Creatinine levels are influenced by kidney filtration, muscle mass and other factors. Doctors interpret creatinine alongside: – eGFR and changes over time. – Blood potassium and bicarbonate. – Fluid balance and urine output. – Clinical symptoms. – The cause of kidney dysfunction. – Response to medical treatment. A person with high creatinine may not require dialysis, while someone with a less dramatically elevated creatinine level may need urgent treatment because of severe complications. Read more about What Causes High Creatinine. Can Dialysis Be Needed in Acute Kidney Injury? Yes. Dialysis may be required temporarily during severe acute kidney injury (AKI). AKI involves a sudden reduction in kidney function, potentially caused by severe infection, reduced blood flow to the kidneys, urinary obstruction or certain medicines. Dialysis may be considered in AKI when serious complications occur, such as: – Dangerous potassium abnormalities. – Severe metabolic acidosis. – Fluid overload affecting breathing. – Certain uremic complications. In selected cases of poisoning, dialysis may also be used to remove particular toxins. The need for dialysis in AKI depends on the type and severity of complications, not simply how rapidly creatinine has increased. Is Dialysis Permanent After Acute Kidney Injury? Not always. Some patients recover sufficient kidney function after the underlying cause of AKI has been treated and may no longer need dialysis. Others develop persistent kidney impairment and require ongoing treatment. Recovery depends on the cause, severity and duration of AKI, previous kidney function and other medical conditions. What Are the Different Types of Dialysis? There are two main forms of dialysis used for kidney failure: hemodialysis and peritoneal dialysis. Hemodialysis Hemodialysis uses a machine and an external filter, called a dialyzer, to remove waste products and excess fluid from the blood. Blood passes through the filter and