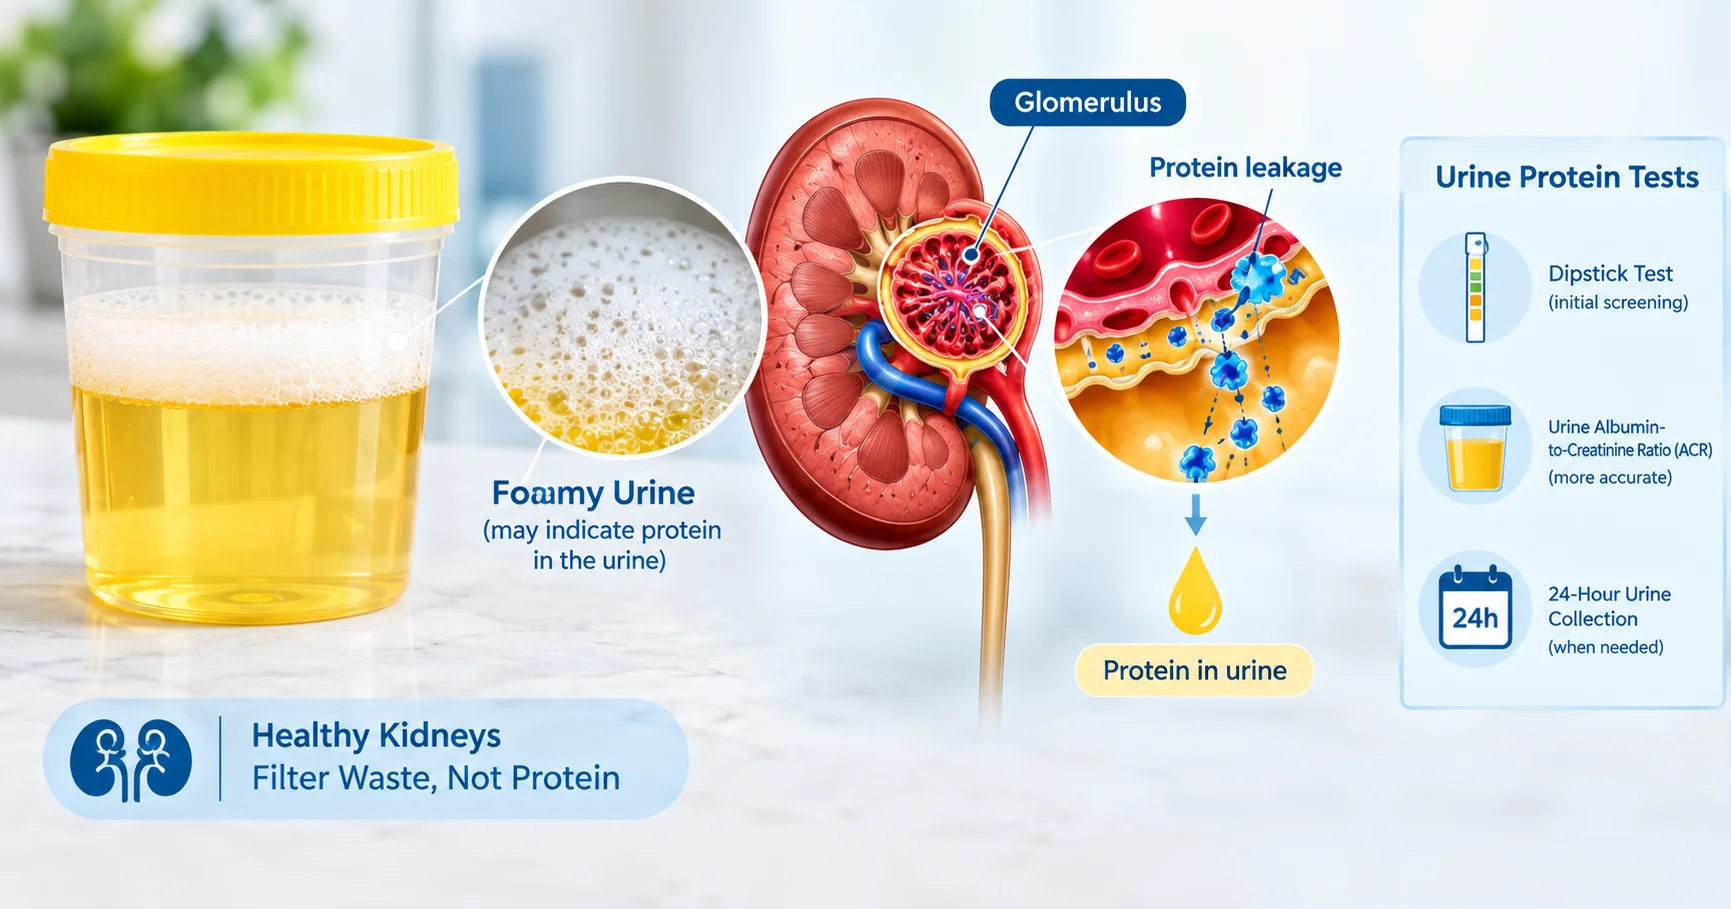
When your doctor orders a urine albumin‑creatinine ratio (ACR) test, the goal is to catch early signs of kidney stress before symptoms appear. This guide breaks down the science in plain language, explains what the numbers mean, and shows you how to prepare for accurate results. Medical Review: Dr. Jyoti Bansode, MBBS, MD Medicine, DM Nephrology – >10 years of nephrology experience. What the Urine ACR Test Measures The ACR test quantifies two substances in a single, random‑spot urine sample: albumin (a protein that belongs in the bloodstream) and creatinine (a waste product filtered by the kidneys). The laboratory divides the albumin concentration (mg) by the creatinine concentration (g) to produce a ratio expressed as mg/g. Because creatinine corrects for urine concentration, the ACR is more reliable than a simple dip‑stick protein test. For a detailed explanation, see Dr. Jyoti Bansode’s article. Albumin vs. Creatinine Albumin should stay in the blood; the kidneys act as a sieve that prevents it from leaking into urine. Creatinine, on the other hand, is a by‑product of muscle metabolism that the kidneys normally excrete. By comparing the two, the ACR tells you whether the filtration barrier is compromised. Why Albumin in Urine Matters Even tiny amounts of albumin (called microalbuminuria) signal that the glomeruli—the tiny filtering units—are under stress. Persistent albuminuria is linked to a higher risk of chronic kidney disease (CKD), cardiovascular events, and progression to end‑stage renal disease. The National Kidney Foundation notes that albuminuria is a red flag for both kidney and heart health NKF uACR overview. Understanding ACR Result Ranges Normal: < 30 mg/g – no significant albumin loss. Microalbuminuria: 30–300 mg/g – early kidney damage; warrants repeat testing and risk‑factor control. Macroalbuminuria: >300 mg/g – overt proteinuria; indicates more advanced disease. These cut‑offs are widely accepted in clinical practice and help guide treatment decisions NKF uACR overview. Common Causes of a High ACR Diabetes mellitus – high blood sugar damages glomerular capillaries. Hypertension – elevated pressure strains the filtration barrier. Glomerulonephritis or other inflammatory kidney diseases. Infections (e.g., urinary tract infection, fever). Medications such as non‑steroidal anti‑inflammatory drugs (NSAIDs) or certain antibiotics. For a deeper look at how diabetes triggers albuminuria, read our Understanding Microalbuminuria in Diabetes. Temporary Factors That Can Skew Results Not every elevated ACR means chronic disease. Transient conditions can raise albumin temporarily: Intense exercise or heavy lifting (muscle breakdown releases creatinine). Fever or acute illness. Dehydration – concentrates urine, raising the ratio. High‑protein meals within the previous 24 hours. Menstrual blood contamination. If any of these apply, your clinician may repeat the test after a few days. Interpreting ACR with eGFR and Creatinine ACR is most powerful when viewed alongside estimated glomerular filtration rate (eGFR) and serum creatinine. A normal eGFR with a high ACR suggests early glomerular injury, while a low eGFR with a modest ACR may reflect advanced CKD. Our Kidney Tests Explained: Creatinine, eGFR, Urine ACR & Electrolytes article walks through the combined interpretation. Laboratories such as Labcorp calculate the ratio automatically and flag results that exceed risk thresholds Labcorp ACR test details. Diabetes, Hypertension, and Cardiovascular Risk Albuminuria is not just a kidney issue; it predicts heart attacks, strokes, and peripheral artery disease. People with diabetes and high blood pressure are up to three times more likely to develop albuminuria, and each 30 mg/g increase in ACR raises cardiovascular risk by roughly 10 % according to the National Kidney Foundation NKF uACR risk page. How Often Should You Repeat the Test? Guidelines recommend: Annual screening for anyone with diabetes or hypertension. Every 1–2 years for individuals with other CKD risk factors (family history, age > 60). Repeat within 3–6 months if the first result is abnormal, after addressing any temporary factors. When to See a Nephrologist Schedule a specialist appointment if you meet any of the following: ACR > 300 mg/g on two separate occasions. eGFR < 60 mL/min/1.73 m² combined with any albuminuria. Rapidly rising ACR (increase > 30 % within 3 months). Persistent proteinuria despite optimal blood‑pressure and glucose control. Our guide on specialist referral can help you prepare for the visit: When Should You See a Nephrologist in Navi Mumbai?. Practical Patient Checklist Before Your ACR Test Collect a mid‑stream, clean‑catch urine sample in the morning if possible. Avoid vigorous exercise for 24 hours prior. Stay well‑hydrated, but do not over‑drink immediately before the test. Notify the lab if you have a fever, infection, or recent heavy protein intake. Bring a list of current medications (especially NSAIDs, ACE inhibitors, or ARBs). Following these steps improves accuracy and reduces the need for repeat testing. Frequently Asked Questions What does a normal urine ACR result look like? A normal ACR is less than 30 mg of albumin per gram of creatinine, indicating that the kidneys are effectively retaining protein. Can a single high ACR result be ignored? No. A single elevated ACR should be repeated after 3–6 months, especially if you had recent fever, intense exercise, or dehydration that could temporarily raise the ratio. Why is the ACR preferred over a simple urine protein dip‑stick? The ACR corrects for urine concentration by using creatinine as a reference, making it more reliable than a dip‑stick, which can be falsely low in dilute urine or high in concentrated samples. How does diabetes affect the urine ACR? High blood glucose damages the glomerular filter, allowing albumin to leak into urine. Even early diabetes can cause microalbuminuria (30–300 mg/g), which signals the need for tighter glucose and blood‑pressure control. When should I see a nephrologist after an abnormal ACR? If your ACR exceeds 300 mg/g, if eGFR falls below 60 mL/min/1.73 m², or if albuminuria rises rapidly despite treatment, a referral to a nephrologist is recommended. Conclusion Understanding your urine ACR result empowers you to act early, protect kidney function, and lower cardiovascular risk. Talk to your healthcare provider about the next steps, whether that means lifestyle changes, medication adjustments, or a referral to a nephrologist.