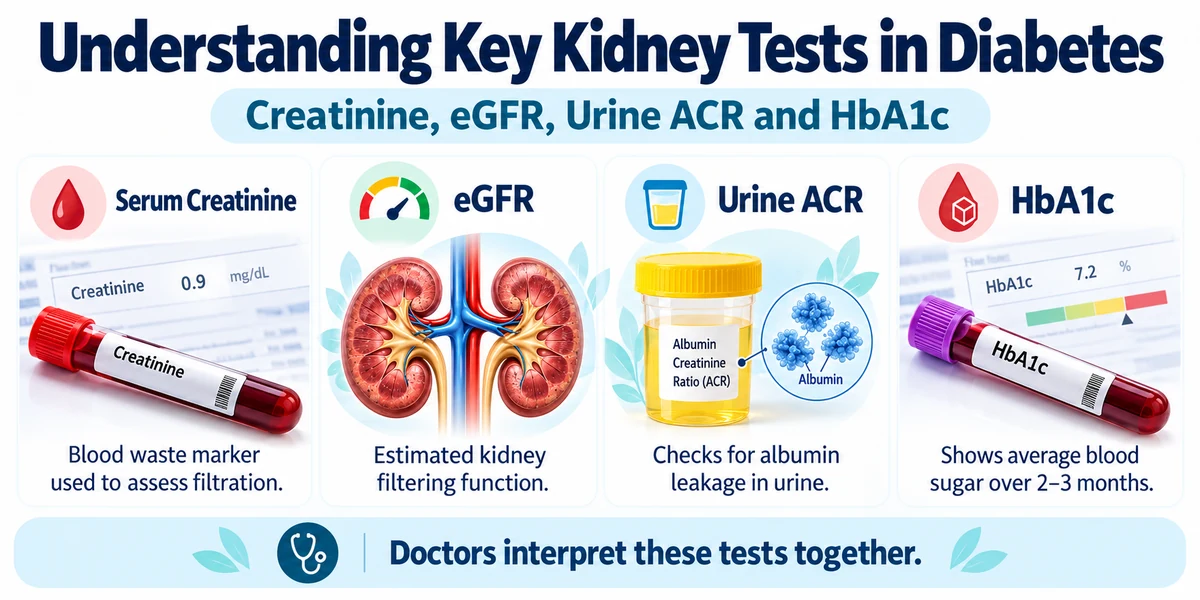
Diabetes can damage the tiny filtering units in the kidneys, reducing their ability to clear waste; regular blood and urine screening catches problems early, allowing treatment that can slow or halt progression. How does diabetes affect the kidneys and why is regular screening important? High blood glucose over many years harms the glomeruli – the tiny capillaries that filter blood – leading to leakage of protein and reduced filtration. Screening with serum creatinine, eGFR and urine ACR identifies early injury before symptoms appear, giving clinicians a chance to intervene. What is diabetic kidney disease and how does high blood sugar cause damage? Diabetic kidney disease (DKD) is the gradual loss of kidney function caused by chronic hyperglycaemia. Excess glucose triggers inflammation and thickening of the glomerular basement membrane, making it less efficient at filtering waste and allowing albumin to leak into urine. What does a serum creatinine test measure? Serum creatinine measures the concentration of creatinine – a waste product from muscle metabolism – that the kidneys normally remove. The result provides a snapshot of how well the kidneys are clearing this waste at the time of the blood draw. Why can a normal creatinine result still miss early kidney damage? Creatinine levels stay within the normal range until roughly 50 % of kidney function is lost because the body can compensate. Early structural damage may therefore be invisible on a single creatinine test, making complementary measures such as eGFR and ACR essential. What is eGFR and how do doctors interpret it? eGFR (estimated glomerular filtration rate) uses the creatinine value together with age, sex, body size and ethnicity to estimate how many millilitres of blood the kidneys filter each minute per 1.73 m² of body surface. Clinicians compare the eGFR to the patient’s age, prior results and any co‑existing conditions; a decline of more than 5 ml/min/1.73 m² per year often signals progressive disease. How is the urine albumin‑to‑creatinine ratio (ACR) test performed and why repeat testing may be needed? The urine ACR measures the amount of albumin (a protein) relative to creatinine in a single‑spot urine sample, eliminating the need for a 24‑hour collection. Small increases (micro‑albuminuria) can fluctuate with exercise, fever or hydration, so a repeat test after 2–3 months confirms whether the finding is persistent. What does swelling of the feet, ankles or face indicate? Swelling (edema) can result from fluid retention due to reduced kidney function, but it also occurs with heart failure, low albumin, certain medications or prolonged standing. Therefore, edema alone does not confirm kidney failure; a full assessment of blood tests, blood pressure and clinical history is required. How can I tell if test changes are temporary or a sign of chronic kidney disease? Transient abnormalities often resolve after treating an acute illness, adjusting medication or correcting dehydration. Persistent changes – repeated abnormal eGFR, rising ACR or steadily increasing creatinine over three or more readings spaced weeks apart – suggest chronic kidney disease (CKD) and warrant specialist review. Will everyone with diabetes eventually develop kidney failure? No. While diabetes increases the risk of kidney disease, good glucose control, blood‑pressure management and early treatment of albuminuria can keep many people from progressing to end‑stage renal failure. Individual risk depends on genetics, lifestyle and comorbidities. What everyday strategies protect my kidneys? Maintain target HbA1c (as advised by your clinician) to limit glucose‑induced damage. Control blood pressure < 130/80 mmHg, often using ACE inhibitors or ARBs. Adopt a balanced diet low in sodium and moderate in protein. Stay hydrated, avoid excessive NSAID use and quit smoking. Attend regular kidney‑function screenings – at least annually for type 2 diabetes and from five years after diagnosis for type 1 diabetes diabetes‑on‑the‑net. When should I arrange a routine check‑up and when is urgent assessment required? Schedule routine kidney panels (creatinine, eGFR, ACR) at least once a year, or more often if previous results show borderline values or you have hypertension ADA CKD Compendium. Seek urgent care if you develop sudden swelling, a rapid rise in creatinine, unexplained shortness of breath, or if urine becomes foamy or dark, as these may signal acute kidney injury. Quick reference: test comparison Test What it measures Normal range (approx.) Key clinical use Serum Creatinine Waste product from muscle metabolism 0.6–1.2 mg/dL (varies by sex & muscle mass) Initial screen for reduced filtration eGFR Estimated filtration rate per 1.73 m² >90 mL/min/1.73 m² (stage 1) Stage CKD, monitor progression Urine ACR Albumin relative to creatinine in urine <30 mg/g (normal), 30–300 mg/g (micro‑albuminuria) Detect early glomerular leak HbA1c Average blood glucose over 2–3 months 4.0–5.6 % (normal) Guide glucose‑control targets For deeper guidance on protecting kidneys with diabetes, see our practical daily tips. If you have resistant hypertension, read our resistant hypertension overview. To arrange a review, use the appointment and consultation page. Frequently Asked Questions What is the difference between eGFR and serum creatinine? Serum creatinine is a raw blood measurement, while eGFR translates that value into an estimated filtration rate that accounts for age, sex and body size. Can a single high ACR result be ignored? No. A single elevated ACR may be caused by temporary factors; repeat testing after a few weeks confirms whether albuminuria is persistent. Why does swelling sometimes appear even with normal kidney tests? Edema can arise from heart failure, low albumin, medication side‑effects or prolonged standing, so it is not a specific sign of kidney failure. How often should people with type 2 diabetes have kidney tests? Guidelines recommend at least annual eGFR and ACR checks from the time of diagnosis, with more frequent monitoring if results are abnormal. Do ACE inhibitors protect the kidneys? Yes, ACE inhibitors and ARBs reduce pressure within the glomeruli and lower albumin excretion, slowing the progression of diabetic kidney disease. When is an urgent kidney assessment needed? Urgent review is required for rapid creatinine rise, sudden swelling, foamy urine, or unexplained shortness of breath, as these may indicate acute kidney injury. Conclusion Understanding what creatinine, eGFR and ACR tell you about kidney health empowers proactive management of diabetic kidney disease. Regular testing, timely interpretation and personalised lifestyle