+91 8691888178 / 8850999397 dr.jyotibansode.01@gmail.com Monday to Saturday : 05:00PM TO 06:00PM

Diabetes Kidney Disease FAQ: Creatinine, eGFR, ACR & Swelling

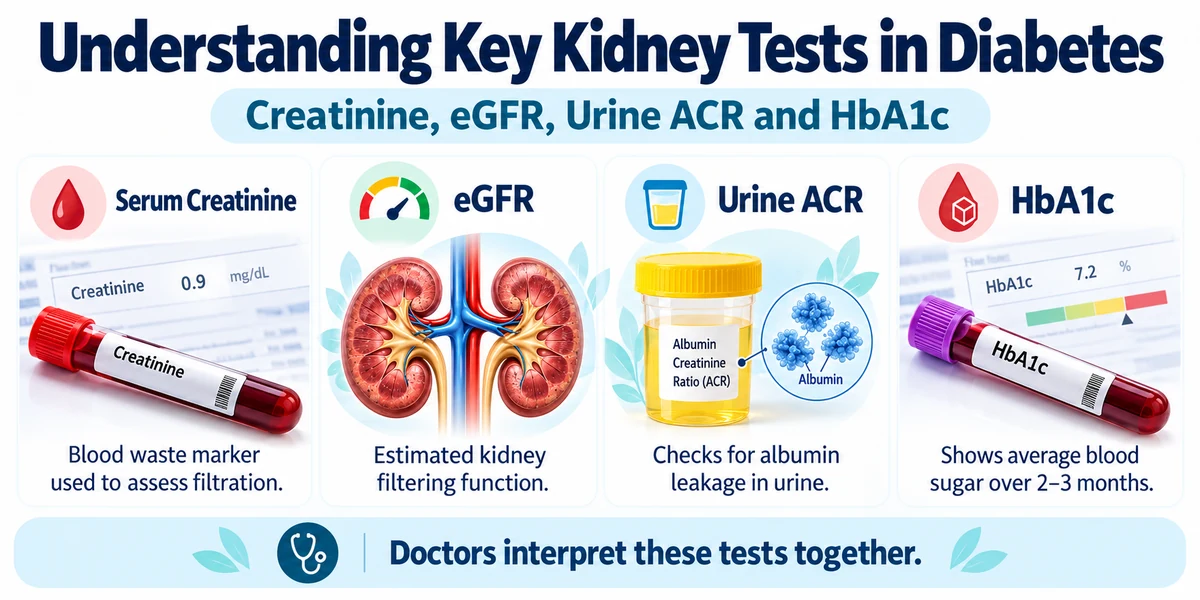
Diabetes can damage the tiny filtering units in the kidneys, reducing their ability to clear waste; regular blood and urine screening catches problems early, allowing treatment that can slow or halt progression. How does diabetes affect the kidneys and why is regular screening important? High blood glucose over many years harms the glomeruli – the tiny capillaries that filter blood – leading to leakage of protein and reduced filtration. Screening with serum creatinine, eGFR and urine ACR identifies early injury before symptoms appear, giving clinicians a chance to intervene. What is diabetic kidney disease and how does high blood sugar cause damage? Diabetic kidney disease (DKD) is the gradual loss of kidney function caused by chronic hyperglycaemia. Excess glucose triggers inflammation and thickening of the glomerular basement membrane, making it less efficient at filtering waste and allowing albumin to leak into urine. What does a serum creatinine test measure? Serum creatinine measures the concentration of creatinine – a waste product from muscle metabolism – that the kidneys normally remove. The result provides a snapshot of how well the kidneys are clearing this waste at the time of the blood draw. Why can a normal creatinine result still miss early kidney damage? Creatinine levels stay within the normal range until roughly 50 % of kidney function is lost because the body can compensate. Early structural damage may therefore be invisible on a single creatinine test, making complementary measures such as eGFR and ACR essential. What is eGFR and how do doctors interpret it? eGFR (estimated glomerular filtration rate) uses the creatinine value together with age, sex, body size and ethnicity to estimate how many millilitres of blood the kidneys filter each minute per 1.73 m² of body surface. Clinicians compare the eGFR to the patient’s age, prior results and any co‑existing conditions; a decline of more than 5 ml/min/1.73 m² per year often signals progressive disease. How is the urine albumin‑to‑creatinine ratio (ACR) test performed and why repeat testing may be needed? The urine ACR measures the amount of albumin (a protein) relative to creatinine in a single‑spot urine sample, eliminating the need for a 24‑hour collection. Small increases (micro‑albuminuria) can fluctuate with exercise, fever or hydration, so a repeat test after 2–3 months confirms whether the finding is persistent. What does swelling of the feet, ankles or face indicate? Swelling (edema) can result from fluid retention due to reduced kidney function, but it also occurs with heart failure, low albumin, certain medications or prolonged standing. Therefore, edema alone does not confirm kidney failure; a full assessment of blood tests, blood pressure and clinical history is required. How can I tell if test changes are temporary or a sign of chronic kidney disease? Transient abnormalities often resolve after treating an acute illness, adjusting medication or correcting dehydration. Persistent changes – repeated abnormal eGFR, rising ACR or steadily increasing creatinine over three or more readings spaced weeks apart – suggest chronic kidney disease (CKD) and warrant specialist review. Will everyone with diabetes eventually develop kidney failure? No. While diabetes increases the risk of kidney disease, good glucose control, blood‑pressure management and early treatment of albuminuria can keep many people from progressing to end‑stage renal failure. Individual risk depends on genetics, lifestyle and comorbidities. What everyday strategies protect my kidneys? Maintain target HbA1c (as advised by your clinician) to limit glucose‑induced damage. Control blood pressure < 130/80 mmHg, often using ACE inhibitors or ARBs. Adopt a balanced diet low in sodium and moderate in protein. Stay hydrated, avoid excessive NSAID use and quit smoking. Attend regular kidney‑function screenings – at least annually for type 2 diabetes and from five years after diagnosis for type 1 diabetes diabetes‑on‑the‑net. When should I arrange a routine check‑up and when is urgent assessment required? Schedule routine kidney panels (creatinine, eGFR, ACR) at least once a year, or more often if previous results show borderline values or you have hypertension ADA CKD Compendium. Seek urgent care if you develop sudden swelling, a rapid rise in creatinine, unexplained shortness of breath, or if urine becomes foamy or dark, as these may signal acute kidney injury. Quick reference: test comparison Test What it measures Normal range (approx.) Key clinical use Serum Creatinine Waste product from muscle metabolism 0.6–1.2 mg/dL (varies by sex & muscle mass) Initial screen for reduced filtration eGFR Estimated filtration rate per 1.73 m² >90 mL/min/1.73 m² (stage 1) Stage CKD, monitor progression Urine ACR Albumin relative to creatinine in urine <30 mg/g (normal), 30–300 mg/g (micro‑albuminuria) Detect early glomerular leak HbA1c Average blood glucose over 2–3 months 4.0–5.6 % (normal) Guide glucose‑control targets For deeper guidance on protecting kidneys with diabetes, see our practical daily tips. If you have resistant hypertension, read our resistant hypertension overview. To arrange a review, use the appointment and consultation page. Frequently Asked Questions What is the difference between eGFR and serum creatinine? Serum creatinine is a raw blood measurement, while eGFR translates that value into an estimated filtration rate that accounts for age, sex and body size. Can a single high ACR result be ignored? No. A single elevated ACR may be caused by temporary factors; repeat testing after a few weeks confirms whether albuminuria is persistent. Why does swelling sometimes appear even with normal kidney tests? Edema can arise from heart failure, low albumin, medication side‑effects or prolonged standing, so it is not a specific sign of kidney failure. How often should people with type 2 diabetes have kidney tests? Guidelines recommend at least annual eGFR and ACR checks from the time of diagnosis, with more frequent monitoring if results are abnormal. Do ACE inhibitors protect the kidneys? Yes, ACE inhibitors and ARBs reduce pressure within the glomeruli and lower albumin excretion, slowing the progression of diabetic kidney disease. When is an urgent kidney assessment needed? Urgent review is required for rapid creatinine rise, sudden swelling, foamy urine, or unexplained shortness of breath, as these may indicate acute kidney injury. Conclusion Understanding what creatinine, eGFR and ACR tell you about kidney health empowers proactive management of diabetic kidney disease. Regular testing, timely interpretation and personalised lifestyle
How to Protect Kidneys with Diabetes – Practical Daily Tips

Direct answer (40‑60 words): The most important steps to protect kidneys with diabetes are to keep blood glucose at your personalised target, control blood pressure, stay hydrated, follow a low‑sodium, balanced diet, avoid smoking and NSAIDs, take any prescribed kidney‑protective medicines, and attend regular kidney‑function tests. Why high blood sugar harms the kidneys Persistent hyperglycaemia damages the tiny filtering units (glomeruli) in the kidneys. Excess glucose triggers inflammation and thickening of the glomerular basement membrane, leading to leakage of albumin (protein) into the urine – a condition called albuminuria. Over time, filtration capacity (eGFR) declines, progressing toward diabetic nephropathy. Key risk factors Beyond uncontrolled diabetes, other factors increase the chance of diabetic kidney disease: – Hypertension (often >140/90 mmHg) – Smoking – Cardiovascular disease – Obesity – Family history of kidney disease These risks interact; managing each one lowers overall kidney‑damage risk. Ten practical kidney‑protection strategies Maintain individualised blood‑sugar targets. Work with your diabetes team to set a realistic HbA1c goal based on age, duration of diabetes, heart health and hypoglycaemia risk. Regular self‑monitoring and timely medication adjustments are essential. Monitor and manage blood pressure. Aim for the target your clinician recommends, often <130/80 mmHg for many diabetics. Lifestyle changes and, if needed, ACE inhibitors or ARBs provide added kidney protection. Take prescribed kidney‑protective medications. ACE inhibitors, ARBs, SGLT2 inhibitors or GLP‑1 receptor agonists have proven benefits for slowing eGFR decline. Never start or stop these drugs without medical advice. Reduce excess dietary sodium. Limit added salt, avoid salty snacks such as pickles, papad, namkeen and processed chips. Aim for less than 2 g of sodium per day, as recommended by the National Kidney Foundation NKF guidance. Follow a balanced, kidney‑appropriate eating plan. Emphasise high‑fiber vegetables, whole grains, lean proteins (fish, poultry, legumes) and healthy fats. Avoid excessive animal protein that can increase glomerular workload, but do not adopt an extreme low‑protein diet without specialist input. Maintain suitable hydration. Drink enough fluid to keep urine pale‑yellow, but adjust if you have heart failure or reduced kidney function; a fixed litre‑per‑day rule is not appropriate. Exercise regularly. Aim for about 150 minutes of moderate activity (brisk walking, cycling, swimming) each week, unless contraindicated by your doctor. Physical activity improves insulin sensitivity and blood pressure. Avoid smoking and limit alcohol. Smoking accelerates vascular damage, while excess alcohol can raise blood pressure and interfere with medications. Avoid unnecessary NSAIDs and unregulated supplements. Over‑the‑counter pain relievers (ibuprofen, naproxen) can reduce renal blood flow. Discuss any herbal or “kidney‑cleansing” products with your clinician. Attend regular kidney‑screening appointments. Annual urine albumin‑to‑creatinine ratio (ACR), eGFR, serum creatinine, and blood pressure checks detect early changes before symptoms appear. Indian dietary considerations Traditional Indian cuisine often includes high‑salt items such as pickles, papad, namkeen and packaged snacks. Replace these with fresh salads, low‑salt roasted vegetables, and homemade spice blends without added salt. Use herbs like coriander, mint and lemon juice for flavour. While a universal renal diet is not advised, a typical balanced plate could be: half non‑starchy vegetables, a quarter whole‑grain roti or brown rice, and a quarter lean protein (dal, fish, chicken). Adjust portions based on personal calorie needs and kidney function. Hydration – a nuanced approach Fluid needs vary with body size, climate, activity level, and co‑existing heart or kidney disease. Generally, aim for urine that is light straw‑coloured. If you have fluid restrictions prescribed by a nephrologist, follow those limits precisely. Physical activity guidelines For most adults with diabetes, 150 minutes of moderate‑intensity aerobic exercise per week is safe and beneficial. Include resistance training twice weekly to preserve muscle mass, which supports glucose metabolism. Essential preventive tests Key investigations performed at least annually:  – Urine albumin‑to‑creatinine ratio (ACR) – detects early albuminuria.  – Estimated glomerular filtration rate (eGFR) – assesses overall kidney function.  – Serum creatinine – part of eGFR calculation.  – HbA1c – monitors long‑term glucose control.  – Blood pressure measurement. Early diabetic kidney disease may be silent; a normal creatinine alone does not rule out damage, especially when eGFR is still >60 mL/min/1.73 m². Do / Limit / Discuss With Your Doctor Do Limit Discuss With Your Doctor Check blood glucose and pressure daily; keep a log. Consume >2 g sodium per day; binge‑drink alcohol. Any change in urine colour, swelling, or persistent fatigue. Take ACE inhibitor/ARB or SGLT2 inhibitor if prescribed. Frequent use of over‑the‑counter NSAIDs. Starting or stopping any medication, including herbal supplements. Aim for 150 min/week moderate exercise. Very high‑protein diets (>1.5 g/kg body weight) without supervision. Declining eGFR, rising ACR, or unexplained swelling. Common mistakes to avoid Many patients rely on “kidney‑cleansing” herbs, stop medicines when they feel better, or think a single normal test means the kidneys are fine. Protein intake should be balanced, not excessively low or high, and test results must be interpreted over time, not in isolation. When specialised nephrology advice is needed Seek a kidney specialist if you have persistent albuminuria (ACR ≥ 30 mg/g), a steady decline in eGFR, rising serum creatinine, uncontrolled hypertension despite therapy, or unexplained peripheral swelling. Early referral allows personalised treatment plans. Medical review by Dr. Jyoti BansodeMBBS, MD Medicine, DM NephrologyOver 10 years of nephrology experienceArticle reviewed and approved on 2026‑10‑09. For deeper insight into how diabetes affects kidney health, see our Can Diabetes Damage Your Kidneys? page. Learn more about early signs and testing in Diabetic Kidney Disease Symptoms: Early Signs & Tests. If you’re concerned about blood‑pressure‑related kidney stress, read Can High Blood Pressure Damage Your Kidneys?. Further reading from trusted organisations includes the National Kidney Foundation’s recommendations here and the National Institute of Diabetes and Digestive and Kidney Diseases guidance on HbA1c targets NIDDK. Frequently Asked Questions Can I prevent diabetic kidney disease completely? While no one can guarantee complete prevention, tight glucose and blood‑pressure control, a balanced diet and regular kidney checks dramatically lower the risk of progression. What does a high urine albumin test mean? Elevated albumin in urine (albuminuria) signals early damage to the glomeruli. It often appears before any change in creatinine or eGFR, so prompt medical review is important. Is it safe

Microalbuminuria Follow‑Up: What Happens After an Abnormal Result?

After an abnormal urine albumin‑to‑creatinine ratio (ACR) result, you can expect your doctor to repeat the test, review other kidney function markers, and look for temporary causes before deciding if further specialist referral is needed. What Is Microalbuminuria? Microalbuminuria, now termed moderately increased albuminuria, means a small but abnormal amount of albumin is leaking into the urine. It often signals early kidney stress before overt disease develops, especially in people with diabetes or hypertension. Urine ACR Categories The urine albumin‑to‑creatinine ratio (ACR) is expressed in milligrams of albumin per gram of creatinine (mg/g). The common categories are: Below 30 mg/g – normal to mildly increased. 30–299 mg/g – moderately increased (microalbuminuria). ≥300 mg/g – severely increased (macro‑albuminuria). Why a Single Abnormal Result Isn’t a Diagnosis Several temporary factors can raise urine albumin levels, so one high reading does not confirm permanent kidney damage. Common triggers include:  – Fever or acute infection.  – Urinary tract infection.  – Strenuous exercise or heavy lifting.  – Marked hyperglycaemia (high blood sugar).  – Uncontrolled blood pressure spikes.  – Dehydration or recent NSAID use. These factors are often reversible, and the albumin leak may disappear once the underlying cause is addressed. When and Why Doctors Repeat the Test Guidelines from the American Diabetes Association and KDIGO recommend confirming persistent albuminuria before labeling chronic kidney disease. Typically, at least two of three ACR samples collected over a 3–6 month period must be elevated for a diagnosis in diabetes.Ubie Doctor’s Note explains that a single high reading is insufficient for a CKD label. Repeating the test also helps differentiate a true trend from a transient spike caused by the factors listed above. Key Follow‑Up Investigations In addition to repeat ACR, clinicians usually order a panel of kidney‑related tests to build a complete picture. Test Purpose What an Abnormal Result May Indicate Repeat urine ACR Confirm persistence of albuminuria Early kidney stress, need for monitoring Serum creatinine & eGFR Estimate filtration capacity Reduced kidney function (CKD stage) HbA1c Assess long‑term blood‑sugar control Poor control raises risk of diabetic nephropathy Blood pressure measurement Identify hypertension as a kidney stressor Uncontrolled BP accelerates albumin leakage Urinalysis (dipstick, microscopy) Detect infection, haematuria, or other protein sources UTI, glomerulonephritis, stones, etc. Lipid profile (optional) Cardiovascular risk assessment High LDL may worsen kidney outcomes These investigations are guided by clinical context and may be expanded if the patient has other comorbidities. How a Nephrologist Evaluates Persistent Microalbuminuria If repeat testing confirms persistent moderately increased albuminuria, a referral to a nephrologist is often advised. The specialist reviews:  – Diabetes history (duration, control, complications).  – Blood‑pressure trends and current antihypertensive regimen.  – All medications, especially ACE inhibitors, ARBs, NSAIDs, and herbal supplements.  – Previous kidney‑function tests (eGFR trajectory, creatinine trends).  – Any signs of other renal diseases (haematuria, systemic lupus, etc.). These details help the nephrologist decide whether to intensify kidney‑protective therapy, order imaging, or perform a kidney biopsy in rare cases. Before / During / After Your Follow‑Up Appointment Stage What to Do What to Expect Before Bring previous lab reports, medication list, and note any recent infections, exercise, or fever. Doctor will schedule repeat ACR and possibly a fasting blood draw. During Discuss lifestyle factors, blood‑pressure readings, and blood‑sugar logs. Provider may perform a physical exam and order the test panel above. Results are usually reviewed within 1–2 weeks; the clinician explains whether the finding is persistent. After Follow any medication adjustments, adopt recommended diet/exercise changes, and schedule the next ACR in 3–6 months. Continued monitoring helps determine if the albumin level improves, stays stable, or worsens. Management Strategies to Protect Your Kidneys Even without permanent damage, early intervention can slow progression:  – Blood‑sugar control: Aim for HbA1c targets set by your diabetes team (often <7%).  – Blood‑pressure control: Keep systolic <130 mmHg, using ACE inhibitors or ARBs when appropriate – these drugs also reduce albuminuria.  – Kidney‑protective medicines: ACE‑I/ARB, SGLT2 inhibitors, or GLP‑1 receptor agonists have proven benefit in diabetic kidney disease The Kingsley  Clinic.  – Dietary habits: Moderate protein, limit sodium, stay hydrated, and consider a DASH‑style eating plan.  – Regular monitoring: Repeat ACR and eGFR at least annually, or more often if values are rising. Can the Result Improve? With optimal control of blood sugar, blood pressure, and the use of kidney‑protective drugs, many patients see their ACR move from the moderately increased range back toward normal. Improvement is common, but it does not guarantee that underlying kidney injury has been fully reversed. Warning Signs that Need Immediate Attention If you notice any of the following, contact your healthcare provider promptly:  – Sudden reduction in urine output.  – Rapidly worsening swelling (edema) in legs or face.  – Shortness of breath or difficulty breathing.  – Visible blood in the urine or a dramatic change in colour.  – Severe flank pain. These symptoms may indicate an acute kidney issue that requires urgent evaluation. For deeper insight into how protein in urine relates to kidney disease, see our Protein in Urine Causes article. To learn more about diabetic kidney disease and its early markers, read Diabetic Nephropathy vs CKD. If you are wondering when to see a specialist, our When Should a Person With Diabetes See a Kidney Specialist guide offers practical thresholds. Frequently Asked Questions What does a single high urine ACR result mean? A single elevated ACR indicates possible kidney stress but does not confirm chronic kidney disease; repeat testing is needed to see if the finding persists. How many ACR tests are required to confirm persistent microalbuminuria? Guidelines suggest that at least two out of three ACR measurements taken over 3–6 months must be in the 30–299 mg/g range to confirm persistence. Can lifestyle changes lower my ACR level? Yes. Better blood‑sugar control, blood‑pressure management, reduced sodium intake, and regular moderate exercise have all been shown to lower albumin excretion. When should I see a nephrologist after an abnormal result? If repeat ACR tests remain elevated, or if you have rapidly declining eGFR, uncontrolled hypertension, or other concerning symptoms, a nephrology referral is advised. Do ACE inhibitors

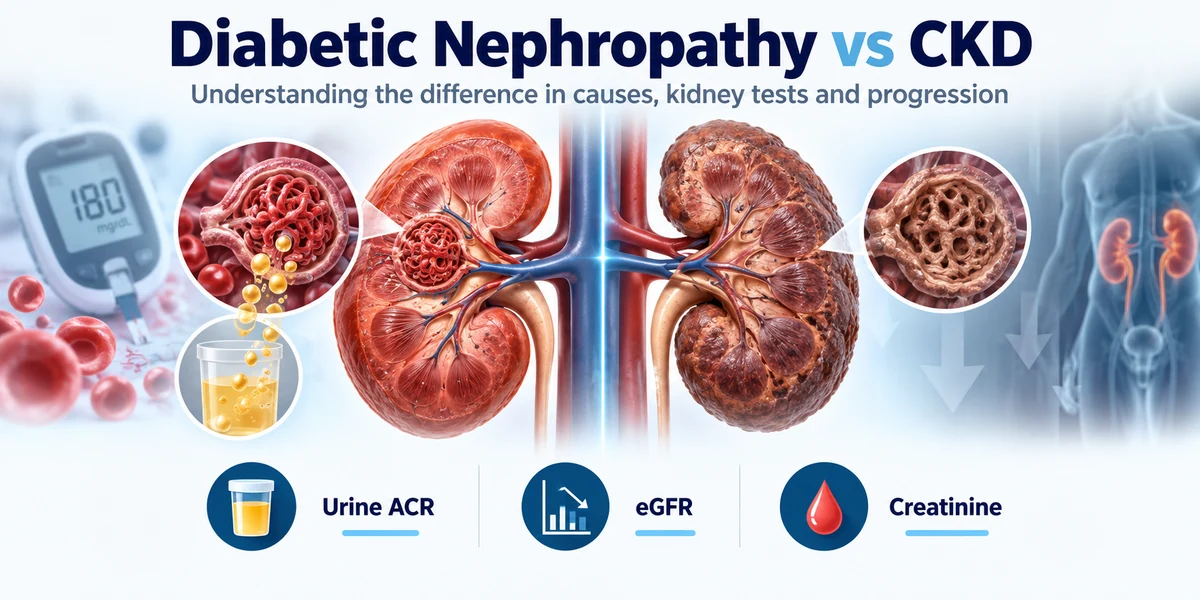
Diabetic Nephropathy vs CKD: Key Differences Explained

Diabetic nephropathy is kidney damage that results directly from long‑term high blood sugar, whereas chronic kidney disease (CKD) is a broader clinical term for any persistent kidney impairment lasting at least three months, regardless of the underlying cause. What Is Diabetic Nephropathy? Diabetic nephropathy, also called diabetic kidney disease, occurs when chronic hyperglycaemia damages the tiny filtering units (glomeruli) in the kidneys. Over time, high glucose leads to thickening of the glomerular basement membrane, mesangial expansion and loss of filtration surface area, causing protein to leak into the urine. What Is Chronic Kidney Disease (CKD)? CKD is defined by the presence of kidney abnormalities—such as reduced glomerular filtration rate (eGFR) or albuminuria—that persist for three months or more. It can arise from diabetes, hypertension, glomerulonephritis, polycystic kidney disease and many other conditions. Comparison at a Glance   Aspect Diabetic Nephropathy Chronic Kidney Disease (CKD) Primary cause Long‑term diabetes mellitus (type 1 or type 2) Any sustained kidney injury – diabetes, hypertension, glomerulonephritis, genetic disorders, etc.   Key risk factors Poor glycaemic control, duration of diabetes >10 years, hypertension, smoking Age, family history, cardiovascular disease, obesity, exposure to nephrotoxins Typical symptoms Foamy urine, swelling (edema), fatigue, high blood pressure, nocturia Often silent early; later may include the same symptoms as above Diagnostic hallmark Elevated urine albumin‑to‑creatinine ratio (ACR) ≥ 30 mg/g in a diabetic patient eGFR < 60 ml/min/1.73 m² or ACR ≥ 30 mg/g persisting ≥3 months, regardless of cause Progression pattern Albuminuria → declining eGFR → end‑stage renal disease (ESRD) Variable; may stay stable for years or progress rapidly depending on etiology Management focus Strict glucose and blood‑pressure control, renin‑angiotensin system blockers, lifestyle Address underlying cause, control BP, protect remaining kidney function, diet How Diabetic Nephropathy Leads to CKD When diabetic kidney damage progresses, the persistent albuminuria and loss of nephrons meet the CKD definition. However, not every person with diabetes who develops CKD has classic diabetic nephropathy; other kidney diseases (e.g., IgA nephropathy) can coexist, and some diabetic patients develop CKD from hypertension rather than direct glucose toxicity. Shared Symptoms to Watch For Foamy or bubbly urine (protein in urine) Swelling of ankles, feet or hands Unexplained fatigue Elevated blood pressure Changes in urination frequency or volume Early kidney disease often has no noticeable symptoms, which is why regular screening is crucial for people with diabetes or other risk factors. Key Laboratory Tests Doctors rely on a combination of blood and urine tests: Serum creatinine – used to calculate eGFR. eGFR – estimates kidney filtering capacity; values <60 ml/min/1.73 m² suggest CKD. Urine albumin‑to‑creatinine ratio (ACR) – quantifies protein loss. HbA1c – reflects average blood‑sugar control over 2‑3 months. Routine urinalysis – looks for blood, casts, infection. Kidney ultrasound – ordered when structural abnormalities are suspected. Understanding Urine ACR Categories According to clinical guidelines, ACR results are interpreted as: Normal: < 30 mg/g – no significant albumin loss. Microalbuminuria: 30–299 mg/g – early sign of kidney damage. Macroalbuminuria: ≥ 300 mg/g – indicates more advanced disease. Putting Test Results Into Context Doctors combine medical history, blood‑pressure readings, urine ACR trends and eGFR trajectories to infer the likely cause of kidney disease. For example, a diabetic patient with steadily rising ACR and a falling eGFR is classic for diabetic nephropathy, whereas a non‑diabetic patient with isolated low eGFR may have a different CKD aetiology. Management Strategies Effective kidney protection hinges on several pillars: Blood‑glucose control: Target HbA1c <7 % (individualised). Blood‑pressure control: Aim for <130/80 mmHg, often using ACE inhibitors or ARBs. Kidney‑protective medications: SGLT2 inhibitors and GLP‑1 receptor agonists have shown renal benefits in diabetes. Dietary guidance: Moderate protein (0.8 g/kg), sodium <2 g/day, adequate hydration. Regular monitoring: Check eGFR and ACR every 3–6 months. For deeper insight into early signs, see our early signs and tests page, and for advice on managing rising creatinine, read Rising Creatinine in Diabetes. To learn how lifestyle can slow progression, visit How to Slow Diabetic Kidney Disease Progression. When to See a Nephrologist Referral is recommended if any of the following occur: Persistent albuminuria (ACR ≥ 30 mg/g) despite optimal diabetes care. eGFR declines by >5 ml/min/1.73 m² per year. Serum creatinine rises steadily or spikes unexpectedly. Unexplained hematuria or blood in urine. Hypertension that is difficult to control with three or more agents. Early specialist involvement can slow progression and prepare for potential renal replacement therapy if needed. About Dr. Jyoti Bansode Dr. Jyoti Bansode, MBBS, MD Medicine and DM Nephrology, brings over 10 years of experience in managing diabetic kidney disease and CKD. Her evidence‑based approach integrates the latest ADA Standards of Care and National Kidney Foundation recommendations. Frequently Asked Questions Can I have CKD without having diabetes? Yes. CKD can result from hypertension, glomerulonephritis, polycystic kidney disease and many other causes unrelated to diabetes. Is protein in urine always a sign of diabetic nephropathy? Proteinuria indicates kidney damage but is not exclusive to diabetes; it can arise from other kidney diseases or temporary conditions like infection. How often should I have my urine ACR checked? For people with diabetes, an ACR test is recommended at least once a year; more frequent testing is advised if earlier results were abnormal. Do ACE inhibitors cure diabetic nephropathy? ACE inhibitors do not cure the condition, but they lower blood pressure and reduce protein loss, slowing the progression of kidney damage. What lifestyle changes help protect my kidneys? Maintaining good blood‑sugar control, limiting sodium, staying physically active, quitting smoking and following a kidney‑friendly diet all support kidney health. When is dialysis needed for CKD? Dialysis is considered when eGFR falls below 15 ml/min/1.73 m² or when symptoms of kidney failure (e.g., severe fluid overload) become unmanageable. Conclusion Understanding that diabetic nephropathy is a specific form of kidney damage caused by diabetes, while CKD is a broader diagnosis, empowers you to take targeted action. If you notice any warning signs or have concerns about your kidney health, schedule an appointment with Dr. Bansode today.

Diabetic Kidney Care Vashi: Essential Reports for Your Nephrology Visit

Direct answer (40–60 words): Bring your latest serum creatinine, estimated glomerular filtration rate (eGFR), urine albumin‑creatinine ratio (ACR), HbA1c result, and any previous kidney‑related test reports (ultrasound, prior creatinine/eGFR trends). These five reports give the nephrologist a clear picture of kidney function and diabetes control. When Should a Diabetic Patient Seek a Kidney Specialist in Vashi? According to the American Diabetes Association 2026 Standards of Care, you should schedule a nephrology appointment if you notice any of the following: Persistent albuminuria (urine ACR ≥30 mg/g) on two separate tests. Rising serum creatinine or a steady decline in eGFR over three months. Uncontrolled blood pressure (≥140/90 mmHg) despite medication. New‑onset foamy urine, swelling of ankles, or unexplained fatigue. These signs suggest diabetic kidney disease may be progressing and merit specialist evaluation Kidney Specialist in Vashi: What to Bring. Practical Report Checklist for Your First Visit Essential Blood Tests Serum creatinine eGFR (calculated from creatinine, age, sex, race) HbA1c (glycated haemoglobin) Lipid profile (LDL, HDL, triglycerides) Electrolytes (sodium, potassium, bicarbonate) Urine Tests Urine albumin‑creatinine ratio (ACR) – spot test 24‑hour urine protein (if previously ordered) Urine microscopy for casts or infection Diabetes Records Recent HbA1c trends (last 12 months) Medication list (insulin, oral agents, SGLT2 inhibitors, GLP‑1 agonists) Self‑monitoring blood glucose logs Blood Pressure Readings Home BP log (at least three readings per day for a week) Clinic BP measurements, if available Medications & Supplements All prescribed drugs (including ACE inhibitors/ARBs) Over‑the‑counter meds and herbal supplements Previous Kidney Imaging Renal ultrasound reports CT/MRI reports if done for stones or structural issues What Each Report Measures and Why It Matters Report What It Measures Why It Matters for Diabetic Kidney Care Serum Creatinine Level of creatinine in blood, a waste product filtered by kidneys. Elevated values signal reduced filtration; trend helps track disease progression. eGFR Estimated glomerular filtration rate (mL/min/1.73 m²). Provides a stage‑wise assessment of chronic kidney disease; essential for medication dosing. Urine ACR Albumin (protein) relative to creatinine in a spot urine sample. Detects micro‑ and macro‑albuminuria, the earliest sign of diabetic nephropathy. HbA1c Average blood glucose over 2‑3 months. Poor glycaemic control accelerates kidney damage; targets guide therapy. Lipid Profile Cholesterol and triglyceride levels. High LDL contributes to atherosclerotic renal artery disease. Why Previous Results Are Valuable Nephrologists compare current labs with past values to distinguish a new acute insult from a chronic trend. A steady eGFR decline over years suggests progressive diabetic nephropathy, whereas a sudden creatinine spike may indicate dehydration, medication side‑effects, or an acute kidney injury. Having a timeline of reports enables precise risk stratification and avoids unnecessary repeat testing. How Dr. Jyoti Bansode Evaluates Diabetic Kidney Disease During the consultation, Dr. Bansode follows a systematic approach: Medical History: Diabetes duration, glycaemic control, hypertension, cardiovascular disease, and family kidney history. Symptom Review: Foamy urine, swelling, nocturia, itching, fatigue. Physical Examination: Blood pressure, peripheral oedema, abdominal exam for enlarged kidneys. Report Review: All blood, urine, imaging, and medication records are analysed for trends. Additional Tests (if needed): Repeat ACR, renal Doppler ultrasound, or referral for kidney biopsy in atypical cases. This comprehensive assessment aligns with recommendations from the National Kidney Foundation and NIDDK Laboratory Assessment of Diabetic Kidney Disease. Do You Need Every Test Before the First Appointment? No. Bring whatever recent reports you have. If a key test (e.g., urine ACR) is missing, Dr. Bansode will order it during the visit. The goal is to avoid delays while ensuring the specialist has enough data to make an initial plan. Five Questions to Ask Your Nephrologist What is my current stage of diabetic kidney disease based on eGFR and ACR? How should my diabetes medications be adjusted to protect my kidneys? What dietary changes (protein, sodium, potassium) are recommended for my kidney health? How often should I repeat kidney function tests and HbA1c? What are the signs that require me to call you or seek urgent care? Warning Signs Requiring Immediate Attention If you experience any of the following, seek emergency care: Sudden drop in urine output (<400 ml/24 h).  – Severe shortness of breath or chest pain. Confusion, drowsiness, or seizures. – Rapidly worsening swelling of legs, hands, or face. – High fever with flank pain (possible kidney infection). Kidney Consultation with Dr. Jyoti Bansode Dr. Jyoti Bansode, a board‑certified nephrologist with over 10 years of experience, sees patients at NewEra Hospitals, Sector 7, Vashi, Navi Mumbai. The clinic offers state‑of‑the‑art renal imaging, diabetes‑focused kidney care, and personalised medication plans. To book an appointment, visit the appointment and consultation page. Medical Review: This article was reviewed by Dr. Jyoti Bansode, MBBS, MD Medicine, DM Nephrology, with more than a decade of nephrology practice. The information reflects current clinical guidelines and her professional expertise. Related Resources For deeper insight into protein leakage in urine, read our protein and blood in urine guide. To understand how acute and chronic kidney conditions differ, see acute and chronic kidney diseases. Frequently Asked Questions What is the normal range for urine ACR in a diabetic patient? A urine ACR below 30 mg/g is considered normal. Values between 30‑300 mg/g indicate micro‑albuminuria, and above 300 mg/g suggest macro‑albuminuria, signalling progressive kidney damage.   Can a single creatinine test diagnose diabetic kidney disease? No. Creatinine alone provides a snapshot; eGFR and trend over time, combined with urine ACR, are needed to diagnose and stage diabetic nephropathy.   Do SGLT2 inhibitors protect the kidneys? Yes. Current ADA 2026 guidelines recommend SGLT2 inhibitors for most adults with type 2 diabetes and eGFR ≥30 mL/min/1.73 m², as they reduce albuminuria and slow CKD progression. How often should I have my kidney function tested? If you have diabetes without kidney disease, test eGFR and ACR at least annually. With micro‑albuminuria or reduced eGFR, testing every 3‑6 months is advised. Is a low‑protein diet necessary for diabetic kidney disease? A moderate protein intake (0.8 g/kg body weight) is generally recommended to reduce renal workload, but extreme restriction is not required unless advised by your nephrologist.   What lifestyle changes help protect my kidneys? Maintain tight blood‑sugar control, keep blood pressure <130/80 mmHg, stay active, limit sodium,

When Should a Person With Diabetes See a Kidney Specialist in Navi Mumbai?

Direct answer (45 words): A person with diabetes should consider seeing a kidney specialist in Navi Mumbai when routine tests show persistent albuminuria, rising creatinine, falling eGFR, uncontrolled blood pressure, unexplained swelling, or any concerning symptom that cannot be explained by diabetes alone. Not every diabetic needs an immediate referral. Why Diabetes Affects the Kidneys Long‑term high blood glucose damages the tiny blood vessels in the kidneys, reducing their ability to filter waste. This progressive condition is called diabetic kidney disease or diabetic nephropathy. Over years, the damage can lead to chronic kidney disease (CKD) and, if untreated, to kidney failure. When to Ask for a Nephrology Referral Guidelines and real‑world practice highlight several red‑flag indicators: – Persistent albuminuria (urine albumin‑to‑creatinine ratio ≥ 30 mg/g) on two separate tests. – Serum creatinine that is steadily rising or above the normal range for age and sex. – Estimated glomerular filtration rate (eGFR) dropping below 60 mL/min/1.73 m², especially if the trend is downward. – Blood pressure that remains above 130/80 mmHg despite optimal antihypertensive therapy. – Unexplained peripheral or facial swelling, foamy urine, or sudden weight gain. – Uncertainty about abnormal lab results or conflicting advice from other physicians. Key Kidney Tests for Diabetics Understanding the routine tests helps you know when a result warrants a specialist review. Test Typical Normal Range Findings That Prompt a Nephrology Review Serum Creatinine 0.6‑1.2 mg/dL (varies by muscle mass) Consistently >1.3 mg/dL or a rise >0.3 mg/dL over 3 months eGFR >90 mL/min/1.73 m² Below 60 mL/min/1.73 m² or a decline >5 mL/min/yr Urine Albumin‑Creatinine Ratio (ACR) <30 mg/g 30‑300 mg/g (micro‑albuminuria) or >300 mg/g (macro‑albuminuria) HbA1c 4.0‑5.6 % ≥7.5 % despite therapy – indicates higher risk for kidney damage Serum Electrolytes (Na, K, Cl, Bicarbonate) Within laboratory reference Abnormalities such as hyperkalaemia or metabolic acidosis These thresholds are guides; a single abnormal value does not mean kidney failure, but it does merit discussion with a kidney specialist. What to Bring to Your First Nephrology Appointment Being prepared makes the consultation efficient and thorough. Use the checklist below:– Latest blood test report (creatinine, eGFR, electrolytes, HbA1c).– Urine ACR or 24‑hour urine protein results.– List of current medications, including doses and frequency.– Blood pressure log (at least 3 readings per day for the past week).– Daily blood glucose records or glucometer print‑out.– Any previous kidney imaging (ultrasound, CT) or biopsy reports.– Referral letter from your diabetologist or primary physician, if available.–  How a Nephrologist Evaluates Diabetic Kidney Disease Dr. Jyoti Bansode, MBBS, MD Medicine, DM Nephrology, with over ten years of experience, follows a systematic approach: Review of history, symptoms and the documents listed above. Physical examination focusing on blood pressure, edema and signs of fluid overload. Interpretation of laboratory trends (creatinine, eGFR, ACR) and calculation of CKD stage. Decision on further investigations – e.g., renal ultrasound, renal biopsy (rare), or specialised blood tests for autoimmune causes. Tailored treatment plan: optimisation of blood pressure (often ACE‑inhibitor or ARB), glycaemic control, dietary advice, and medication adjustments. Establishment of a monitoring schedule – typically every 3‑6 months for stable early CKD, more frequently if rapid progression is seen. Five Questions to Ask Your Nephrologist What stage of kidney disease am I in, and how fast is it progressing? Which medications should I start, stop, or adjust to protect my kidneys? How often do I need repeat blood and urine tests? What lifestyle changes (diet, fluid intake, exercise) will have the biggest impact? When would I need to consider referral for dialysis or transplant evaluation? Emergency Warning Signs If any of the following develop suddenly, seek urgent medical care: – Markedly reduced urine output (<200 mL/24 h). – Severe shortness of breath or rapid weight gain due to fluid overload. – Confusion, lethargy, or sudden change in mental status. – Swelling that spreads rapidly to the face or abdomen. Local SEO: Kidney Consultation with Dr. Jyoti Bansode in Navi Mumbai Patients in Navi Mumbai can book a specialised diabetes‑kidney consultation at Dr. Jyoti Bansode’s clinic located in Sector 20, Kopar Khairane. The centre offers state‑of‑the‑art renal imaging, laboratory support and a multidisciplinary team that works closely with diabetologists. For accurate appointment details, refer to the official website Dr. Jyoti Bansode – Nephrologist. Further Reading For a deeper dive into test interpretation, see our Kidney Tests Explained: Creatinine, eGFR, Urine ACR & Electrolytes. If you are looking for guidance on what to bring to a kidney appointment, our Kidney Specialist in Vashi: What to Bring to Your Consultation page is useful. To understand when a nephrologist is recommended in Navi Mumbai, read When Should You See a Nephrologist in Navi Mumbai?. Medical review: Dr. Jyoti Bansode has reviewed and approved this article. Frequently Asked Questions Do I need a referral to see a kidney specialist for diabetes in Navi Mumbai? While a referral is not mandatory, having one from your primary doctor or diabetologist can streamline the appointment and ensure your medical records are shared. How often should I have kidney function tests if I have diabetes? For most diabetics, checking serum creatinine, eGFR and urine ACR at least once a year is recommended; more frequent testing is advised if any abnormality is detected. Can I bring my own urine test kit to the nephrologist? Home kits are useful for monitoring, but the specialist will rely on laboratory‑validated results for diagnosis and treatment decisions. What if my eGFR is slightly below 60 mL/min – is dialysis needed? An eGFR below 60 indicates stage 3 CKD, but dialysis is only considered when eGFR falls below 15 mL/min or symptoms of kidney failure appear. Is it possible to get a second opinion on my kidney report? Yes, you may request a second opinion from another qualified nephrologist; bring all original reports and imaging for review. What are the signs that my kidney problem is an emergency? Sudden loss of urine, severe swelling, breathlessness, or confusion require immediate medical attention. Conclusion Early detection and timely specialist care are vital for preserving kidney function in diabetes. If any of the indicators above apply to you, schedule a consultation with Dr. Jyoti Bansode in Navi Mumbai today.

Rising Creatinine in Diabetes: What It Means and What to Do

Answer: A rising creatinine level in a person with diabetes usually indicates that the kidneys are filtering blood less efficiently, often due to diabetic kidney disease, dehydration, medication effects, or acute injury. Prompt medical review is needed to identify the cause and protect kidney function. How Creatinine Reflects Kidney Filtration Creatinine is a waste product formed from muscle metabolism. The kidneys filter it out of the bloodstream and excrete it in urine. Because the body produces creatinine at a relatively constant rate, the blood concentration is a reliable gauge of glomerular filtration rate (GFR). When GFR falls, serum creatinine rises. Common Causes of Rising Creatinine in Diabetes – Long‑term high blood sugar damaging the tiny filtering units (glomeruli) – known as diabetic nephropathy. – High blood pressure (hypertension) that strains kidney blood vessels. – Dehydration or reduced fluid intake, which concentrates blood creatinine. – Medications such as ACE inhibitors, NSAIDs, or certain antibiotics that affect kidney perfusion. – Acute kidney injury from infections, contrast dye, or severe illness. – Obstruction or urinary tract blockage. For a deeper look at how diabetes harms kidneys, see our diabetes and kidney diseases article. Diabetic Kidney Disease (Diabetic Nephropathy) Studies show that patients with uncontrolled diabetes for many years develop structural damage to the glomerular basement membrane, leading to protein leakage and a gradual rise in creatinine PMC study. This process is often silent until routine labs pick up the change. Early Symptoms and Warning Signs Most people do not feel symptoms until kidney function is markedly reduced, but watch for: Swelling in ankles or feet. Unexplained fatigue or weakness. Changes in urine volume or colour. Persistent nausea or loss of appetite. Muscle cramps, especially at night. If you notice sudden swelling, severe nausea, or a creatinine jump above 2 mg/dL, seek urgent care. Temporary Elevation vs. Chronic Kidney Disease Creatinine can spike temporarily after dehydration, intense exercise, or a short‑term medication change. In chronic kidney disease (CKD), the rise is progressive and persists across multiple tests. Distinguishing the two requires repeat measurements and additional tests. Key Kidney Tests for People with Diabetes   Test What It Shows Serum Creatinine Current waste level; higher = lower filtration. eGFR Estimated GFR based on creatinine, age, sex, and race. Urine Albumin‑to‑Creatinine Ratio (ACR) Detects protein leakage; early sign of nephropathy. HbA1c Average blood sugar over 3 months; high values accelerate kidney damage. Electrolytes (Na, K, Bicarbonate) Assess kidney’s ability to balance fluids and acids. eGFR Categories Stage eGFR (mL/min/1.73 m²) Interpretation 1 >90 Normal or high; kidney damage may still be present. 2 60‑89 Mild decrease; monitor closely. 3a 45‑59 Moderate decrease; consider specialist referral. 3b 30‑44 Moderately severe; nephrology input advised. 4 15‑29 Severe reduction; preparation for possible dialysis. 5 <15 Kidney failure (end‑stage). Urine ACR Categories Result Albumin (mg/g) Risk Level Normal <30 Low risk. Microalbuminuria 30‑300 Early kidney damage. Macroalbuminuria >300 Advanced nephropathy. Our detailed guide to urine tests can be found in Kidney Tests Explained: Creatinine, eGFR, Urine ACR & Electrolytes. Why a Normal Creatinine Doesn’t Always Mean Healthy Kidneys Creatinine is influenced by muscle mass, diet, and hydration. Early diabetic kidney disease often shows normal serum creatinine while urine ACR is already elevated. Therefore, regular screening with eGFR and ACR is essential even if creatinine looks fine. Kidney‑Protection Strategies for People with Diabetes – Maintain tight blood‑sugar control (HbA1c <7%). – Keep blood pressure below 130/80 mmHg, preferably with ACE inhibitors or ARBs. – Stay well‑hydrated; aim for 1.5–2 L of fluid daily unless contraindicated. – Review medications with your doctor; avoid unnecessary NSAIDs. Adopt a kidney‑friendly diet low in sodium and processed protein. – Exercise regularly but avoid extreme muscle‑building workouts that can raise creatinine. For more on protein and blood in urine, read protein and blood in urine. When to Consult a Nephrologist Schedule a specialist appointment if any of the following occur: – eGFR falls below 60 mL/min/1.73 m² (Stage 3) on two separate tests. – Urine ACR shows micro‑ or macro‑albuminuria. – Serum creatinine rises rapidly (>0.3 mg/dL within weeks) without an obvious cause. – Persistent swelling, high blood pressure, or electrolyte abnormalities. Our clinic makes it easy to book a visit – see appointment and consultation for details. Expert Insight Dr. Jyoti Bansode, MBBS, MD Medicine, DM Nephrology, brings over 15 years of experience managing diabetic kidney disease. Her evidence‑based approach combines lifestyle counselling with personalised medication plans to slow progression and improve quality of life. For further reading on the link between diabetes and creatinine, consult the Healthgrades guide and the UCLA Health article. Frequently Asked Questions Can a single high creatinine test mean I have kidney failure? Not necessarily. A one‑time rise can be due to dehydration, recent exercise, or medication. Your doctor will repeat the test and look at eGFR and urine ACR to determine if the change is temporary or indicative of chronic disease. Why is urine albumin important if my creatinine is normal? Albumin leaks into urine long before serum creatinine rises. Detecting micro‑albuminuria allows treatment to start early, potentially halting further kidney damage. Do ACE inhibitors raise creatinine levels? ACE inhibitors may cause a modest, temporary increase in creatinine as they reduce intraglomerular pressure, but they protect the kidneys long‑term by lowering blood pressure and protein loss. How often should a person with diabetes check kidney function? Guidelines recommend checking serum creatinine, eGFR, and urine ACR at least once a year, or more frequently if any abnormality or rapid change is detected. Can lifestyle changes lower a high creatinine level? Yes. Proper hydration, blood‑sugar control, blood‑pressure management, and avoiding nephrotoxic drugs can improve kidney filtration and bring creatinine back toward normal. When is dialysis needed for diabetic kidney disease? Dialysis is considered when eGFR falls below 15 mL/min/1.73 m², symptoms of kidney failure appear, or complications like severe electrolyte imbalance develop. Conclusion If your creatinine is rising, don’t wait – discuss the result with your doctor, repeat the test, and explore the full panel of kidney assessments. Early action can preserve kidney function and keep diabetes under control.

Does Long‑Term High Blood Sugar Cause Protein in Urine?

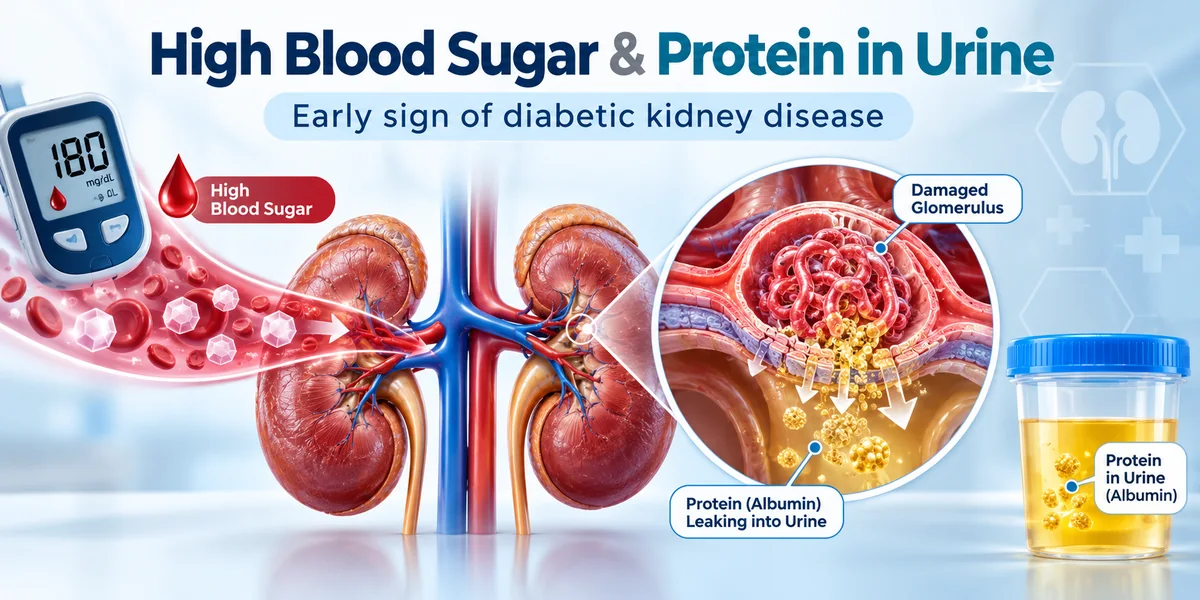
Yes. Persistent high blood sugar harms the tiny filtering units in the kidneys, causing the glomerular walls to thicken and leak protein into the urine—a condition called proteinuria, often the first sign of diabetic kidney disease. If left unchecked, it can progress to chronic kidney disease. Living with diabetes means keeping an eye on more than just blood glucose. One of the earliest warnings that the kidneys are under stress is the appearance of protein in the urine. Understanding why this happens, how to detect it, and when to act can protect your renal health for years to come. How High Blood Sugar Damages Kidney Filters Kidneys contain millions of microscopic filtering units called glomeruli. When blood sugar stays elevated over months or years, several harmful processes unfold:  – Glomerular hyperfiltration – excess glucose draws more fluid into the capillaries, overworking the filter.  – Advanced glycation end‑products (AGEs) thicken the basement membrane, making it leaky.  – Inflammatory pathways trigger scar tissue (fibrosis) that further reduces filtering efficiency. These changes are described in detail by ABDIWALUYO’s overview of kidney damage from high sugar and confirmed by Mayo Clinic News Network, which notes that chemical changes from glucose directly activate factors that cause scarring and protein loss. Glomerular Hyperfiltration and Thickening The afferent arteriole dilates in response to high glucose, increasing blood flow into the glomerulus. Over time, the wall becomes thickened and loses its selective barrier, allowing albumin and other proteins to slip into the urine. Common Causes of Protein in Urine While diabetes is the leading cause, other conditions can also produce proteinuria: Uncontrolled hypertension – high pressure damages glomerular capillaries. Glomerulonephritis – inflammation of the filtering units. Infections or fever – temporary stress on the kidneys. Medications such as NSAIDs or certain antibiotics. For a deeper dive into what’s normal versus worrisome, see our Protein in Urine Causes article. Early Symptoms and Warning Signs Protein loss often occurs without obvious symptoms, but subtle clues may appear:  – Foamy or bubbly urine.   – Swelling in ankles, feet, or around the eyes (edema).  – Unexplained fatigue or loss of appetite.  – Frequent nighttime urination. If you notice any of these, especially alongside high blood sugar readings, it’s time to test your urine. Key Kidney Tests: ACR, eGFR, and Creatinine The three most informative lab values for kidney health are: – Urine Albumin‑to‑Creatinine Ratio (ACR) – measures how much albumin is present relative to creatinine, providing a spot‑test for proteinuria. A result above 30 mg/g signals abnormal leakage.  – Estimated Glomerular Filtration Rate (eGFR) – calculates kidney filtering capacity from serum creatinine, age, sex, and race. Values below 60 mL/min/1.73 m² indicate reduced function.  – Serum Creatinine – a waste product cleared by the kidneys; rising levels suggest declining filtration. Our detailed guide on the urine ACR test can be found at Urine ACR Test. For a broader overview of all kidney labs, check the kidney test guide. When to See a Nephrologist Early referral can slow or even reverse damage. Schedule a nephrology appointment if you:  – Have an ACR >30 mg/g on two separate tests.  – Experience persistent edema or unexplained weight gain.  – Show a steady decline in eGFR over three months.  – Are unable to achieve target blood‑sugar levels despite lifestyle and medication. Timely specialist care, combined with tighter glucose control, can improve outcomes, as highlighted in NephDocs’ proteinuria guide and Kidney Clinic of North Florida’s review of diabetic kidney disease. Medical Review: Dr. Jyoti Bansode, MD, Nephrology Conclusion Long‑term high blood sugar is a direct culprit behind protein leakage in the urine. By monitoring ACR, eGFR, and creatinine, and seeking nephrology care early, you can protect your kidneys and maintain overall health. Frequently Asked Questions Can occasional spikes in blood sugar cause protein in urine? Transient spikes are less likely to produce measurable proteinuria. Persistent hyperglycemia over weeks to months is needed to damage the glomeruli enough for protein to appear in the urine. What amount of protein in urine indicates kidney damage? An ACR above 30 mg/g (microalbuminuria) is considered abnormal and signals early kidney damage. Values above 300 mg/g indicate overt proteinuria and more advanced disease. Is proteinuria reversible if blood sugar is well controlled? Yes, many patients see a reduction in urine protein when blood glucose is brought into target ranges, especially if intervention occurs before significant scarring develops. How often should diabetics get a urine ACR test? Guidelines recommend at least once a year for stable diabetes, and every 3–6 months if you have existing kidney involvement or fluctuating blood‑sugar levels. Does dehydration affect protein urine results? Dehydration can concentrate urine, temporarily raising the ACR value. It’s best to test when you are well‑hydrated to avoid false‑positive readings.

Diabetic Kidney Disease with Normal Creatinine – What You Need to Know

Yes, diabetic kidney disease can be present even when serum creatinine is within the normal laboratory range. Creatinine alone may miss early kidney damage because albumin leakage in urine often appears before a significant fall in the kidneys’ filtering ability. Why Creatinine Can Remain Normal in Early Diabetic Kidney Disease Serum creatinine reflects the overall filtration capacity of the kidneys, but it does not detect subtle damage to the glomerular filter. In the early stages of diabetic nephropathy, the glomerular basement membrane becomes leaky, allowing albumin to pass into the urine while the total filtration rate (and thus creatinine) stays within normal limits. Therefore, a patient can have: Normal creatinine Relatively preserved eGFR Elevated urine albumin (high urine ACR) and still have evidence of kidney damage. How Diabetes Damages the Glomeruli Prolonged high blood glucose damages the tiny blood vessels that line the glomeruli – the kidney’s filtering units. The excess glucose triggers inflammation and thickening of the basement membrane, making it porous. The first sign is usually a small amount of albumin spilling into the urine (microalbuminuria). Over time, continued injury can reduce the number of functional nephrons, leading to a drop in eGFR and, eventually, chronic kidney disease. Creatinine vs eGFR vs Urine ACR Each test answers a different question about kidney health. Understanding their roles helps catch disease early. Test What It Measures Typical Use Creatinine Blood waste product from muscle metabolism Basic screen; high levels suggest reduced filtration eGFR Estimated glomerular filtration rate (calculates filtration based on creatinine, age, sex, race) Quantifies overall kidney function Urine ACR Albumin‑to‑creatinine ratio in a spot urine sample Detects early leak of protein (albumin) from glomeruli Because they assess different aspects, clinicians interpret them together rather than in isolation. Can eGFR Be Normal in Early Diabetic Kidney Disease? Yes. In the initial phases of diabetic nephropathy, the eGFR often remains >90 mL/min/1.73 m² while urine ACR is already elevated. A normal eGFR does not guarantee that the kidneys are healthy; persistent albuminuria signals early injury even when filtration appears preserved. Current Screening Guidance for Diabetes Guidelines from the American Diabetes Association and KDIGO recommend: People with type 2 diabetes: urine ACR and eGFR testing at least once a year from the time of diagnosis. People with type 1 diabetes: begin annual kidney screening after about five years of diabetes duration, unless other risk factors call for earlier testing. Regular monitoring helps detect changes before symptoms appear. Early Warning Signs (Often Absent) Early diabetic kidney disease usually has no noticeable symptoms. When it progresses, patients may notice: Foamy or frothy urine (protein) Swelling of the feet or ankles Increasing blood pressure Fatigue or reduced energy Changes in urination frequency Nausea or loss of appetite Can a High Urine ACR Be Temporary? Transient factors can raise urine albumin, including intense exercise, fever, urinary‑tract infection, marked hyperglycaemia, menstruation, heart failure, or a sudden spike in blood pressure. One abnormal ACR result does not automatically confirm chronic kidney disease; repeat testing after a few weeks is recommended to verify persistence. What Test Results May Suggest Early Kidney Damage? Look for patterns such as: Normal serum creatinine + elevated urine ACR. Preserved eGFR + elevated urine ACR. Gradual decline in eGFR over months or years. Increasing albumin levels on consecutive ACR tests. These findings indicate that the kidneys are under stress even if the filtration rate seems normal. What Should You Do If Creatinine Is Normal but You Have Diabetes? Discuss the following with your clinician: Request a urine ACR test. Ask for an eGFR calculation based on your latest labs. Review previous creatinine results to spot trends. Review prior urine ACR results, if available. Check your blood pressure readings. Know your most recent HbA1c level. Ask whether repeat urine testing is needed to confirm any abnormality. Inquire if your kidney‑function numbers are changing over time. When Should You See a Nephrologist? Referral is appropriate when any of the following occur: Persistently elevated urine ACR (especially >300 mg/g). Rapid increase in albuminuria over a short period. Steady decline in eGFR (e.g., drop >5 mL/min/1.73 m² per year). Persistent protein or blood in urine protein and blood in urine. Difficult‑to‑control hypertension despite medication. Unexplained swelling (edema). Sudden or unexplained changes in kidney‑function test results. Uncertainty about the cause of abnormal kidney tests acute and chronic kidney diseases. Referral does not mean you have end‑stage disease; it ensures specialized care to slow progression. Why Early Detection Matters Interventions such as tighter glucose control, blood‑pressure management (often with ACE inhibitors or ARBs), lifestyle changes, and regular monitoring can significantly slow the progression of diabetic kidney disease. Medical Review: Dr. Jyoti BansodeMBBS, MD Medicine, DM NephrologyMore than 10 years of nephrology experience For a deeper look at how diabetes affects kidney health, see our diabetes and kidney diseases page. If you notice persistent protein or blood in your urine, read our protein and blood in urine guide. For broader information on chronic kidney conditions, explore acute and chronic kidney diseases. Key sources:  American Heart Association overview of kidney disease in diabetes, bidirectional link study between diabetes and kidney disease, KDIGO‑style review of diabetic kidney disease. Frequently Asked Questions Can diabetic kidney disease happen with normal creatinine? Yes. Early kidney damage can cause albumin to leak into urine while serum creatinine remains within the normal range. Can kidney damage occur with a normal eGFR? Yes. Albuminuria can be present even when eGFR is >90 mL/min/1.73 m², indicating early glomerular injury. Which test detects diabetic kidney disease earliest? Urine ACR (albumin‑to‑creatinine ratio) is the most sensitive early marker, detecting microalbuminuria before creatinine or eGFR change. Is urine ACR more useful than creatinine for early kidney damage? For early detection, yes. Urine ACR identifies tiny amounts of albumin that appear before serum creatinine rises. Can albumin in urine be temporary? Transient factors like exercise, infection, fever, or high blood pressure can raise urine albumin; repeat testing confirms persistence. When should a person with diabetes see a nephrologist? See a nephrologist if urine ACR stays high, eGFR declines, protein/blood persists in urine, hypertension is uncontrolled,

Diabetic Kidney Disease Symptoms: Early Signs & Tests

Diabetic kidney disease (DKD), also called diabetic nephropathy, is a common complication of diabetes. Current American Diabetes Association guidance estimates that chronic kidney disease affects about 20–40% of people with diabetes. The condition may develop without noticeable symptoms, so regular urine and blood testing is important for detecting kidney damage early.  Medical Review: Dr. Jyoti Bansode, MBBS, MD Medicine, DM Nephrology — more than 10 years of nephrology experience. Quick Answer: What Are the Early Symptoms of Diabetic Kidney Disease? Early diabetic kidney disease often causes no obvious symptoms. The first signs may appear on kidney tests, such as increased albumin in urine or changes in eGFR. As kidney disease progresses, possible symptoms may include:  – Foamy or unusually bubbly urine  – Swelling in the feet, ankles or around the eyes  – Fatigue or weakness  – Changes in urination  – Nausea or reduced appetite  – Itching or muscle cramps  – Increasing or difficult-to-control blood pressure Because early diabetic kidney disease is often silent, blood and urine tests are more reliable than waiting for symptoms to appear.  What Is Diabetic Kidney Disease? Diabetic kidney disease develops when diabetes damages the small blood vessels and filtering structures inside the kidneys. The kidneys contain microscopic filtering units called glomeruli. Over time, persistently high blood glucose can damage these filters, allowing albumin to leak into the urine and gradually reducing the kidneys’ ability to remove waste from the blood. High blood pressure can further increase stress on the kidneys and accelerate kidney damage. For a broader explanation, read about diabetes and kidney diseases. Why Can Diabetic Kidney Disease Develop Without Symptoms? Kidneys have significant reserve capacity. Early kidney damage may therefore develop while a person still feels completely well. NIDDK notes that most people with diabetic kidney disease do not have symptoms in the early stages. Kidney problems are usually detected through blood and urine tests.  A patient can have: No pain + no swelling + normal-looking urine and still have albuminuria or another early kidney abnormality. Who Is at Higher Risk? Not everyone with diabetes develops diabetic kidney disease. Risk may be greater in people who have: Diabetes for many years Persistently high blood glucose High blood pressure Cardiovascular disease Smoking habits Excess body weight Family history of kidney failure Existing kidney abnormalities NIDDK identifies poor blood-glucose control and high blood pressure as especially important risk factors.  Type 1 vs Type 2 Diabetes: When Should Kidney Testing Begin? Type 1 Diabetes Current ADA 2026 recommendations advise checking urine ACR and eGFR at least annually once a person has had type 1 diabetes for five years or more.  Type 2 Diabetes People with type 2 diabetes should generally have urine ACR and eGFR checked at least once a year from diagnosis, regardless of treatment. Diabetes Journals This difference matters because type 2 diabetes may have been present for years before it is diagnosed. What Are the Earliest Signs of Kidney Damage in Diabetes? The earliest signs are often found on laboratory tests. 1. Albumin in the Urine Albumin is a protein that normally remains in the bloodstream. When the kidney filters are damaged, albumin can begin leaking into urine. This is called albuminuria. The standard test used to measure this is the urine albumin-to-creatinine ratio (UACR). For more detail, see the Urine ACR Test Guide. 2. Changes in eGFR The estimated glomerular filtration rate (eGFR) estimates how well the kidneys are filtering blood. A declining eGFR can indicate reduced kidney function. 3. Changes in Serum Creatinine Creatinine is a waste product normally filtered from the blood by the kidneys. As filtration worsens, serum creatinine may increase. However, creatinine alone is not enough to assess early diabetic kidney disease. 4. Increasing Blood Pressure High blood pressure can damage kidney blood vessels, while kidney disease can also make blood pressure more difficult to control. Patients with persistent blood-pressure problems can read more about resistant hypertension. The Two Most Important Tests for Diabetic Kidney Disease The two key kidney markers are: Urine ACR (UACR) eGFR NIDDK specifically identifies urine albumin and eGFR as the two major markers used to detect and monitor chronic kidney disease.  Urine Albumin-to-Creatinine Ratio (UACR) UACR measures albumin in urine relative to creatinine. A random spot urine sample is usually sufficient, meaning a 24-hour urine collection is generally unnecessary for routine screening.  Typical categories include: UACR Result Interpretation UACR Result Interpretation Below 30 mg/g Normal to mildly increased 30–300 mg/g Moderately increased albuminuria Above 300 mg/g Severely increased albuminuria A UACR above 30 mg/g is considered abnormal, but the result should be interpreted with other kidney tests and, when appropriate, repeat measurements.  eGFR eGFR estimates kidney filtration. In general: 60 or above: may be within an acceptable range depending on the clinical situation Below 60: may indicate kidney disease if the reduction persists 15 or below: represents severely reduced kidney function and may indicate kidney failure The result should always be interpreted alongside urine albumin and the patient’s medical history. Can You Have Diabetic Kidney Disease with a Normal eGFR? Yes. A person may have: Normal or relatively preserved eGFR + elevated urine ACR and still have evidence of kidney damage. Albuminuria can appear before significant changes in eGFR. This is why checking only creatinine or eGFR may miss early kidney damage.  How to Understand UACR and eGFR Together How to Understand UACR and eGFR Together UACR eGFR What It May Suggest Normal Normal Current kidney markers may be reassuring. High Normal Possible early kidney damage. Normal Low Reduced kidney filtration requiring evaluation. High Low Kidney damage with reduced filtration may be present. This table is a general guide only. Diagnosis depends on repeat testing, trends over time and the patient’s overall clinical condition. Learn more about combined kidney testing in Kidney Tests Explained. Can a High Urine ACR Be Temporary? Yes. A single elevated urine ACR does not always mean permanent kidney damage. Factors that can temporarily raise UACR include: – Vigorous exercise within the previous 24 hours  – Infection  –