+91 8691888178 / 8850999397 dr.jyotibansode.01@gmail.com Monday to Saturday : 05:00PM TO 06:00PM

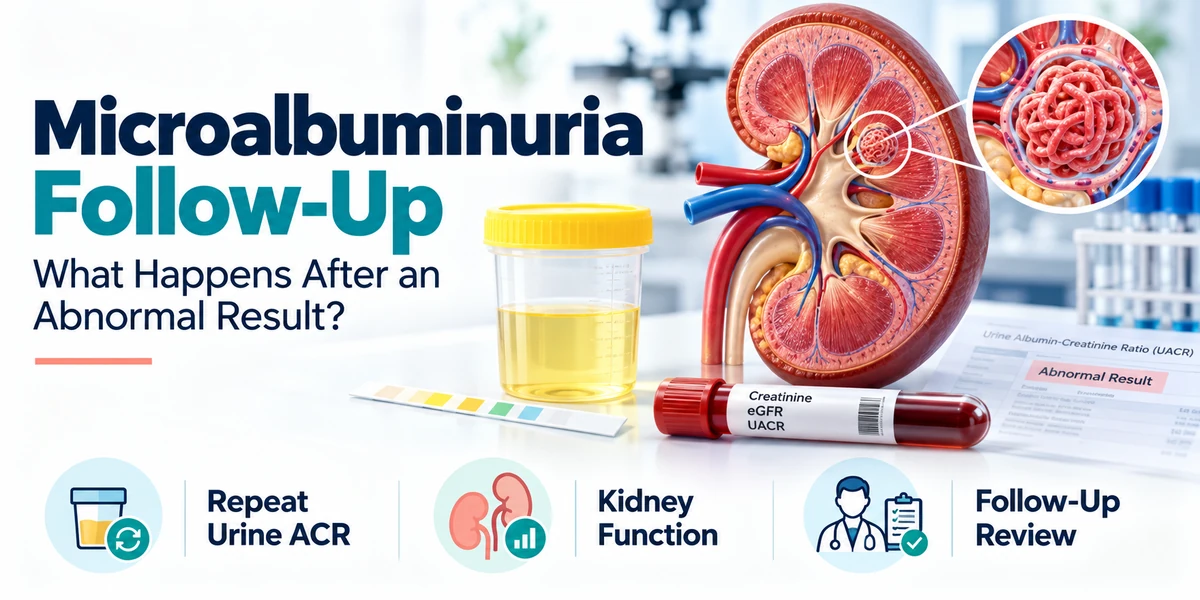
Microalbuminuria Follow‑Up: What Happens After an Abnormal Result?

After an abnormal urine albumin‑to‑creatinine ratio (ACR) result, you can expect your doctor to repeat the test, review other kidney function markers, and look for temporary causes before deciding if further specialist referral is needed. What Is Microalbuminuria? Microalbuminuria, now termed moderately increased albuminuria, means a small but abnormal amount of albumin is leaking into the urine. It often signals early kidney stress before overt disease develops, especially in people with diabetes or hypertension. Urine ACR Categories The urine albumin‑to‑creatinine ratio (ACR) is expressed in milligrams of albumin per gram of creatinine (mg/g). The common categories are: Below 30 mg/g – normal to mildly increased. 30–299 mg/g – moderately increased (microalbuminuria). ≥300 mg/g – severely increased (macro‑albuminuria). Why a Single Abnormal Result Isn’t a Diagnosis Several temporary factors can raise urine albumin levels, so one high reading does not confirm permanent kidney damage. Common triggers include:  – Fever or acute infection.  – Urinary tract infection.  – Strenuous exercise or heavy lifting.  – Marked hyperglycaemia (high blood sugar).  – Uncontrolled blood pressure spikes.  – Dehydration or recent NSAID use. These factors are often reversible, and the albumin leak may disappear once the underlying cause is addressed. When and Why Doctors Repeat the Test Guidelines from the American Diabetes Association and KDIGO recommend confirming persistent albuminuria before labeling chronic kidney disease. Typically, at least two of three ACR samples collected over a 3–6 month period must be elevated for a diagnosis in diabetes.Ubie Doctor’s Note explains that a single high reading is insufficient for a CKD label. Repeating the test also helps differentiate a true trend from a transient spike caused by the factors listed above. Key Follow‑Up Investigations In addition to repeat ACR, clinicians usually order a panel of kidney‑related tests to build a complete picture. Test Purpose What an Abnormal Result May Indicate Repeat urine ACR Confirm persistence of albuminuria Early kidney stress, need for monitoring Serum creatinine & eGFR Estimate filtration capacity Reduced kidney function (CKD stage) HbA1c Assess long‑term blood‑sugar control Poor control raises risk of diabetic nephropathy Blood pressure measurement Identify hypertension as a kidney stressor Uncontrolled BP accelerates albumin leakage Urinalysis (dipstick, microscopy) Detect infection, haematuria, or other protein sources UTI, glomerulonephritis, stones, etc. Lipid profile (optional) Cardiovascular risk assessment High LDL may worsen kidney outcomes These investigations are guided by clinical context and may be expanded if the patient has other comorbidities. How a Nephrologist Evaluates Persistent Microalbuminuria If repeat testing confirms persistent moderately increased albuminuria, a referral to a nephrologist is often advised. The specialist reviews:  – Diabetes history (duration, control, complications).  – Blood‑pressure trends and current antihypertensive regimen.  – All medications, especially ACE inhibitors, ARBs, NSAIDs, and herbal supplements.  – Previous kidney‑function tests (eGFR trajectory, creatinine trends).  – Any signs of other renal diseases (haematuria, systemic lupus, etc.). These details help the nephrologist decide whether to intensify kidney‑protective therapy, order imaging, or perform a kidney biopsy in rare cases. Before / During / After Your Follow‑Up Appointment Stage What to Do What to Expect Before Bring previous lab reports, medication list, and note any recent infections, exercise, or fever. Doctor will schedule repeat ACR and possibly a fasting blood draw. During Discuss lifestyle factors, blood‑pressure readings, and blood‑sugar logs. Provider may perform a physical exam and order the test panel above. Results are usually reviewed within 1–2 weeks; the clinician explains whether the finding is persistent. After Follow any medication adjustments, adopt recommended diet/exercise changes, and schedule the next ACR in 3–6 months. Continued monitoring helps determine if the albumin level improves, stays stable, or worsens. Management Strategies to Protect Your Kidneys Even without permanent damage, early intervention can slow progression:  – Blood‑sugar control: Aim for HbA1c targets set by your diabetes team (often <7%).  – Blood‑pressure control: Keep systolic <130 mmHg, using ACE inhibitors or ARBs when appropriate – these drugs also reduce albuminuria.  – Kidney‑protective medicines: ACE‑I/ARB, SGLT2 inhibitors, or GLP‑1 receptor agonists have proven benefit in diabetic kidney disease The Kingsley  Clinic.  – Dietary habits: Moderate protein, limit sodium, stay hydrated, and consider a DASH‑style eating plan.  – Regular monitoring: Repeat ACR and eGFR at least annually, or more often if values are rising. Can the Result Improve? With optimal control of blood sugar, blood pressure, and the use of kidney‑protective drugs, many patients see their ACR move from the moderately increased range back toward normal. Improvement is common, but it does not guarantee that underlying kidney injury has been fully reversed. Warning Signs that Need Immediate Attention If you notice any of the following, contact your healthcare provider promptly:  – Sudden reduction in urine output.  – Rapidly worsening swelling (edema) in legs or face.  – Shortness of breath or difficulty breathing.  – Visible blood in the urine or a dramatic change in colour.  – Severe flank pain. These symptoms may indicate an acute kidney issue that requires urgent evaluation. For deeper insight into how protein in urine relates to kidney disease, see our Protein in Urine Causes article. To learn more about diabetic kidney disease and its early markers, read Diabetic Nephropathy vs CKD. If you are wondering when to see a specialist, our When Should a Person With Diabetes See a Kidney Specialist guide offers practical thresholds. Frequently Asked Questions What does a single high urine ACR result mean? A single elevated ACR indicates possible kidney stress but does not confirm chronic kidney disease; repeat testing is needed to see if the finding persists. How many ACR tests are required to confirm persistent microalbuminuria? Guidelines suggest that at least two out of three ACR measurements taken over 3–6 months must be in the 30–299 mg/g range to confirm persistence. Can lifestyle changes lower my ACR level? Yes. Better blood‑sugar control, blood‑pressure management, reduced sodium intake, and regular moderate exercise have all been shown to lower albumin excretion. When should I see a nephrologist after an abnormal result? If repeat ACR tests remain elevated, or if you have rapidly declining eGFR, uncontrolled hypertension, or other concerning symptoms, a nephrology referral is advised. Do ACE inhibitors
Understanding Microalbuminuria in Diabetes: What an Abnormal Urine Test Means

When you receive a lab report that says your urine albumin is elevated, it can be unsettling. For people with diabetes, an abnormal urine test often points to microalbuminuria – a subtle but important sign of early kidney stress. This article explains what microalbuminuria in diabetes means, how the test is performed, how to interpret the numbers, and what steps you can take to protect your kidneys. What Is Microalbuminuria in Diabetes? Microalbuminuria refers to a moderate increase in the amount of albumin – a small protein – that leaks into the urine. In healthy kidneys, less than 30 mg of albumin is excreted per gram of creatinine. When the level rises to 30–300 mg/g, the condition is called microalbuminuria; values above 300 mg/g are termed macroalbuminuria or overt proteinuria. According to early diabetes research, this rise is often invisible on a standard dipstick and requires a specific urine microalbumin test. Why It Matters for People With Diabetes Elevated urine albumin is the first measurable sign that the tiny filtering units (glomeruli) in the kidneys are being damaged by high blood sugar. It also signals a higher risk of cardiovascular events. Detecting microalbuminuria early gives you a window to intervene before diabetic nephropathy becomes irreversible. How the Urine Microalbumin Test Works The most common screening method is a spot urine sample that measures both albumin and creatinine, then calculates the urine albumin‑to‑creatinine ratio (UACR). This ratio corrects for variations in urine concentration, making it reliable even when you haven’t timed the collection. Sample Collection Options Random spot sample: The easiest method; you provide a single urine specimen at any time of day. First‑morning sample: Slightly more concentrated, reducing variability. 24‑hour collection: Considered the gold standard but is cumbersome for most patients. Most guidelines recommend an annual spot‑sample screening for adults with diabetes aged 12–70 years clinical recommendation. Understanding the UACR The UACR is reported in milligrams of albumin per gram of creatinine (mg/g). The interpretation is straightforward: Normal: < 30 mg/g Microalbuminuria: 30–300 mg/g (equivalent to 30–300 mg albumin in a 24‑hour collection) Macroalbuminuria: > 300 mg/g These cut‑offs match the definitions used in the Ubie Doctor’s note and are echoed in the MLabs reference. Interpreting Test Results: More Than Just Numbers Understanding UACR result with urine sample, laboratory analysis, and albuminuria interpretation ranges When you see a result labeled “high urine albumin,” consider the following factors before concluding permanent kidney damage: Temporary physiological changes: Fever, vigorous exercise, or a high‑protein meal can transiently raise albumin excretion. Medications: Certain drugs (e.g., NSAIDs) may affect kidney filtration. Laboratory variability: Different labs use slightly different units; always confirm the reference range. If an abnormal value appears, clinicians typically repeat the test. Two out of three positive UACR results over a 3–6‑month period confirm true microalbuminuria clinical protocol. Common Causes of a One‑Time Elevated Albumin Level Before jumping to a diagnosis of diabetic nephropathy, rule out these reversible contributors: Acute urinary tract infection Uncontrolled hypertension Recent intense physical activity (e.g., marathon running) Dehydration or concentrated urine High‑protein diet within the past 24 hours Addressing these factors often normalizes the UACR on repeat testing. Confirming an Abnormal Result – The Screening Protocol Guidelines recommend the following workflow after a first abnormal microalbuminuria reading: Repeat the spot‑sample UACR in 1–3 months. If the second test is still elevated, obtain a third sample within the next 3 months. Two of the three results above 30 mg/g confirm persistent microalbuminuria. Once confirmed, a quantitative assessment of kidney function – including eGFR and serum creatinine – should be ordered. Our Kidney Tests Explained page walks through how eGFR and creatinine complement the urine albumin test. What Microalbuminuria Means for Your Kidneys Persistent microalbuminuria signals early diabetic kidney disease, often called diabetic nephropathy. Studies show that structural changes in the glomeruli can begin a decade before overt symptoms appear research on subclinical kidney changes. If left unchecked, microalbuminuria can progress to macroalbuminuria, a rapid decline in eGFR, and eventually end‑stage renal disease. Because albuminuria reflects systemic endothelial dysfunction, it also flags an increased risk for heart disease and stroke – a dual warning that warrants aggressive risk‑factor management. Protect your kidneys infographic showing blood sugar, blood pressure, diet, monitoring, and medical follow-up in diabetes Managing and Reducing Albuminuria Intervention at the microalbuminuria stage can halt or even reverse kidney damage. Key strategies include: Blood pressure control: Aim for <130/80 mm Hg using ACE inhibitors or ARBs, which specifically reduce intraglomerular pressure. Optimized glycemic control: Target an HbA1c below 7 % (or individualized per provider). Lifestyle modifications: Low‑sodium diet, regular moderate exercise, weight management, and smoking cessation. Lipid management: Statins lower cardiovascular risk, indirectly protecting kidney health. Regular monitoring—every 3–6 months for the first year after detection—helps gauge treatment effectiveness. If albuminuria persists despite optimal therapy, referral to a nephrologist is advised. When to See a Kidney Specialist Consider a referral if any of the following occur: Macroalbuminuria (> 300 mg/g) on two consecutive tests eGFR falls below 60 mL/min/1.73 m² Rapid rise in UACR despite ACE/ARB therapy Uncontrolled hypertension or diabetes despite standard measures Early involvement of a nephrologist can tailor medication regimens, discuss potential renal protective agents, and plan for future renal replacement therapy if needed. For more guidance on when specialist care is appropriate, see our dialysis criteria article. Integrating the Urine Test Into Your Diabetes Care Plan Think of the urine albumin test as a vital sign for your kidneys, just like blood pressure or blood sugar. Incorporate it into your routine diabetes check‑ups, discuss results openly with your endocrinologist, and track trends over time. By staying proactive, you can keep microalbuminuria from becoming a roadblock on your health journey. Frequently Asked Questions What is the normal range for urine albumin‑to‑creatinine ratio (UACR)? A normal UACR is less than 30 mg of albumin per gram of creatinine. Values between 30 and 300 mg/g indicate microalbuminuria, and above 300 mg/g suggest macroalbuminuria. How often should people with diabetes get a urine microalbumin test? Guidelines recommend an annual spot‑sample UACR for adults with diabetes aged 12–70. If microalbuminuria is detected, repeat testing every 3–6 months until the trend is clear. Can a