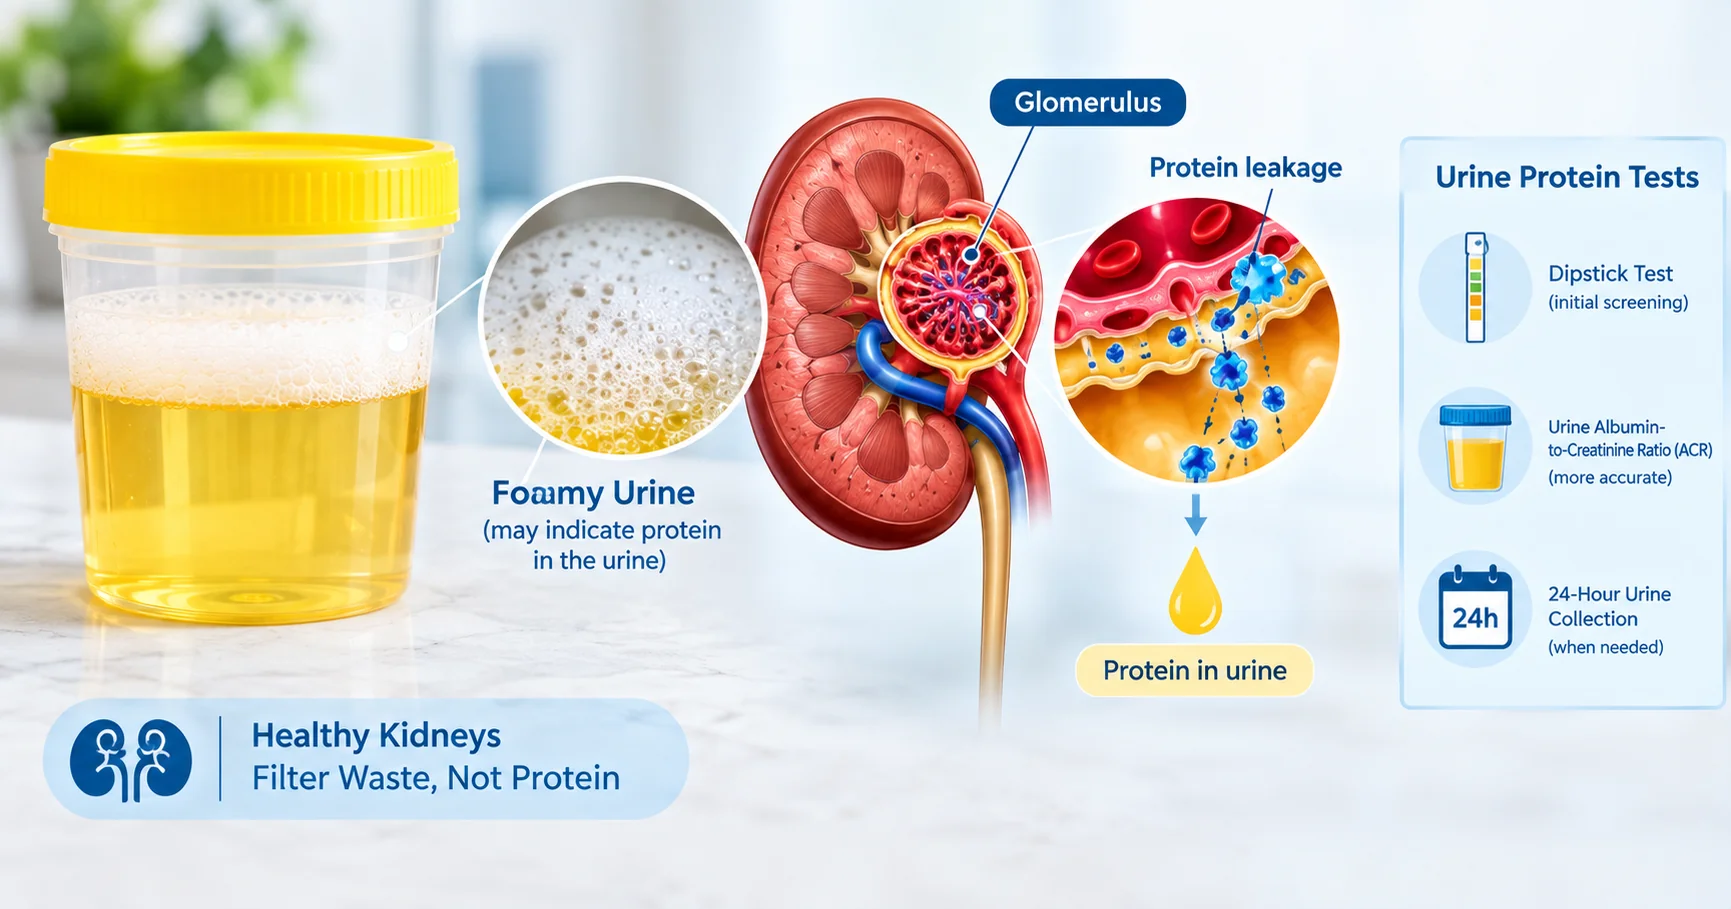
Finding protein or blood in a child’s urine can be unsettling for parents. While occasional traces may be harmless, they can also signal an underlying kidney issue that needs timely attention. This guide explains what these findings mean, common causes, essential tests, and clear signs that warrant a specialist’s evaluation. Quick answer (40‑60 words): Protein or blood in a child’s urine may be temporary (e.g., after fever or exercise) or indicate kidney disease such as glomerulonephritis, nephrotic syndrome, or a urinary tract infection. Seek pediatric nephrology care if the abnormality persists, is accompanied by swelling, high blood pressure, or pain. – Persistent proteinuria or hematuria – Swelling (edema) around eyes, ankles, or abdomen – Unexplained high blood pressure – Painful urination, fever, or flank pain – Family history of kidney disease What Does Protein or Blood in Urine Indicate? Both protein and red blood cells are normally filtered by healthy kidneys. When the filtration barrier is damaged, protein leaks (proteinuria) or blood appears (hematuria) in the urine. According to Orlando Health’s early‑kidney‑signs guide, pediatricians use a routine urine dipstick to detect these abnormalities during well‑child visits. Common Causes of Proteinuria in Children Proteinuria can be classified as orthostatic (appears only when standing) or persistent. The most frequent reasons include: Orthostatic proteinuria – benign and often resolves with age. Fever, illness, or intense exercise – temporary spikes, as noted by the National Kidney Foundation. Urinary tract infection (UTI) – inflammation can leak protein. Nephrotic syndrome – heavy protein loss, swelling, and risk of infections. Chronic kidney disease – progressive loss of filtering ability. In most cases, a single mild proteinuria episode is not serious, but repeated findings require further evaluation Children’s Health on pediatric proteinuria. Common Causes of Hematuria in Children Blood in the urine may be visible (gross hematuria) or only detectable under a microscope (microscopic hematuria). Typical causes are: UTI – the most common infectious cause. Kidney stones – can cause painful bleeding. Trauma – after a fall or sports injury. Glomerulonephritis – inflammation of the kidney’s filtering units. Structural abnormalities – such as reflux or polycystic kidneys. If hematuria persists, especially with protein, high blood pressure, or reduced urine output, a nephrologist should be consulted Nemours KidsHealth on hematuria. When to Seek Kidney Care Most pediatricians will monitor mild, isolated findings. However, you should arrange a specialist appointment when any of the following are present: Proteinuria or hematuria that lasts more than 2 weeks. Swelling (edema) in the face, hands, or feet. Consistently high blood pressure for age. Painful urination, fever, or flank pain. Family history of kidney disease or genetic conditions. Early referral improves outcomes, especially for conditions like nephrotic syndrome or glomerulonephritis. Key Tests Pediatricians Use Tests for protein or blood in a child’s urine including urinalysis, blood tests and kidney ultrasound To pinpoint the cause, doctors may order: Urine analysis (UA) and urine culture – checks for protein, blood, infection, and crystals. Blood tests – serum creatinine, BUN, electrolytes, and complement levels. Kidney ultrasound – non‑invasive imaging to view size, structure, and stones. 24‑hour urine protein collection – quantifies protein loss. Kidney biopsy – reserved for unclear cases or suspected glomerular disease Children’s Health on pediatric hematuria. These investigations help differentiate temporary changes from chronic kidney disease. Red‑Flag Symptoms That Need Immediate Attention While many urinary abnormalities are benign, watch for these urgent signs: – Sudden onset of severe flank or abdominal pain. – Persistent fever (>38°C) with urinary changes. – Rapid swelling of the face or legs. – Decreased urine output or dark‑colored urine. – Signs of anemia (pallor, fatigue) combined with hematuria. If any of these appear, seek emergency care and inform the physician about the urine findings. What to Expect During a Pediatric Nephrology Visit A pediatric nephrologist will review the child’s medical history, repeat urine tests, and may order imaging or a biopsy based on initial results. The goal is to identify the underlying cause, assess kidney function, and develop a treatment plan that may include medication, dietary changes, or monitoring. Medical Review: Dr. Jyoti Bansode, MBBS, MD Medicine, DM Nephrology, with more than 10 years of pediatric nephrology experience. For a deeper dive into kidney‑specific services, explore our kidney specialist in Vashi page or learn when to schedule a consultation via when should you see a nephrologist in Navi Mumbai?. Additional guidance on kidney biopsies is available in Kidney Biopsy Preparation & Recovery. Frequently Asked Questions Is occasional protein in a child’s urine always a cause for concern? Occasional protein, especially after fever, exercise, or dehydration, is often temporary and harmless. However, if it persists for more than a few weeks, repeat testing is recommended. What distinguishes orthostatic proteinuria from disease‑related proteinuria? Orthostatic proteinuria appears only when the child is upright and disappears when lying down, and it usually requires no treatment. Disease‑related proteinuria is present regardless of position and often signals kidney pathology. Can a urinary tract infection cause both protein and blood in urine? Yes, a UTI can irritate the urinary tract lining, leading to protein leakage and microscopic or gross hematuria, along with symptoms like burning urination and fever. When should I schedule a kidney ultrasound for my child? A kidney ultrasound is advised when urine tests show persistent abnormalities, there is flank pain, a history of stones, or structural concerns identified by the pediatrician. Are there lifestyle changes that can reduce proteinuria in children? Ensuring adequate hydration, managing blood pressure, and avoiding excessive salt intake can help. For children with specific kidney conditions, a low‑protein diet may be recommended by a specialist. What is the role of a kidney biopsy in pediatric patients? A biopsy provides a definitive diagnosis when non‑invasive tests are inconclusive, especially for suspected glomerulonephritis or unexplained persistent proteinuria. Conclusion If protein or blood appears in your child’s urine, monitor the situation closely and act promptly when warning signs emerge. Early evaluation by a pediatric nephrologist can prevent complications and ensure the best possible outcome for your child’s kidney health.