+91 8691888178 / 8850999397 dr.jyotibansode.01@gmail.com Monday to Saturday : 05:00PM TO 06:00PM

Microalbuminuria Follow‑Up: What Happens After an Abnormal Result?

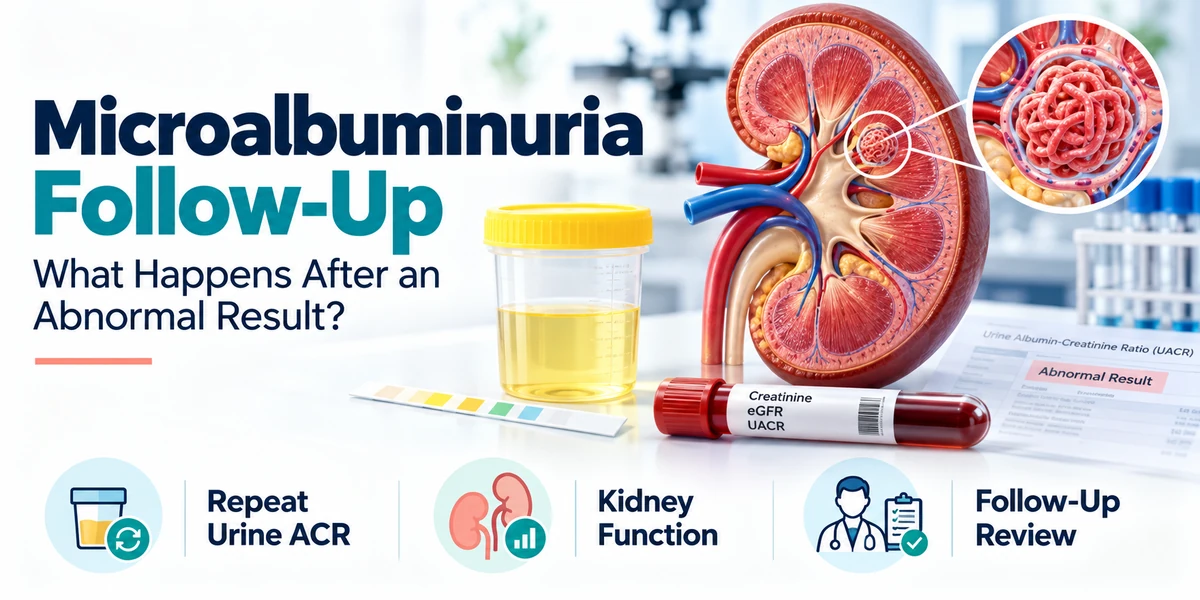
After an abnormal urine albumin‑to‑creatinine ratio (ACR) result, you can expect your doctor to repeat the test, review other kidney function markers, and look for temporary causes before deciding if further specialist referral is needed. What Is Microalbuminuria? Microalbuminuria, now termed moderately increased albuminuria, means a small but abnormal amount of albumin is leaking into the urine. It often signals early kidney stress before overt disease develops, especially in people with diabetes or hypertension. Urine ACR Categories The urine albumin‑to‑creatinine ratio (ACR) is expressed in milligrams of albumin per gram of creatinine (mg/g). The common categories are: Below 30 mg/g – normal to mildly increased. 30–299 mg/g – moderately increased (microalbuminuria). ≥300 mg/g – severely increased (macro‑albuminuria). Why a Single Abnormal Result Isn’t a Diagnosis Several temporary factors can raise urine albumin levels, so one high reading does not confirm permanent kidney damage. Common triggers include:  – Fever or acute infection.  – Urinary tract infection.  – Strenuous exercise or heavy lifting.  – Marked hyperglycaemia (high blood sugar).  – Uncontrolled blood pressure spikes.  – Dehydration or recent NSAID use. These factors are often reversible, and the albumin leak may disappear once the underlying cause is addressed. When and Why Doctors Repeat the Test Guidelines from the American Diabetes Association and KDIGO recommend confirming persistent albuminuria before labeling chronic kidney disease. Typically, at least two of three ACR samples collected over a 3–6 month period must be elevated for a diagnosis in diabetes.Ubie Doctor’s Note explains that a single high reading is insufficient for a CKD label. Repeating the test also helps differentiate a true trend from a transient spike caused by the factors listed above. Key Follow‑Up Investigations In addition to repeat ACR, clinicians usually order a panel of kidney‑related tests to build a complete picture. Test Purpose What an Abnormal Result May Indicate Repeat urine ACR Confirm persistence of albuminuria Early kidney stress, need for monitoring Serum creatinine & eGFR Estimate filtration capacity Reduced kidney function (CKD stage) HbA1c Assess long‑term blood‑sugar control Poor control raises risk of diabetic nephropathy Blood pressure measurement Identify hypertension as a kidney stressor Uncontrolled BP accelerates albumin leakage Urinalysis (dipstick, microscopy) Detect infection, haematuria, or other protein sources UTI, glomerulonephritis, stones, etc. Lipid profile (optional) Cardiovascular risk assessment High LDL may worsen kidney outcomes These investigations are guided by clinical context and may be expanded if the patient has other comorbidities. How a Nephrologist Evaluates Persistent Microalbuminuria If repeat testing confirms persistent moderately increased albuminuria, a referral to a nephrologist is often advised. The specialist reviews:  – Diabetes history (duration, control, complications).  – Blood‑pressure trends and current antihypertensive regimen.  – All medications, especially ACE inhibitors, ARBs, NSAIDs, and herbal supplements.  – Previous kidney‑function tests (eGFR trajectory, creatinine trends).  – Any signs of other renal diseases (haematuria, systemic lupus, etc.). These details help the nephrologist decide whether to intensify kidney‑protective therapy, order imaging, or perform a kidney biopsy in rare cases. Before / During / After Your Follow‑Up Appointment Stage What to Do What to Expect Before Bring previous lab reports, medication list, and note any recent infections, exercise, or fever. Doctor will schedule repeat ACR and possibly a fasting blood draw. During Discuss lifestyle factors, blood‑pressure readings, and blood‑sugar logs. Provider may perform a physical exam and order the test panel above. Results are usually reviewed within 1–2 weeks; the clinician explains whether the finding is persistent. After Follow any medication adjustments, adopt recommended diet/exercise changes, and schedule the next ACR in 3–6 months. Continued monitoring helps determine if the albumin level improves, stays stable, or worsens. Management Strategies to Protect Your Kidneys Even without permanent damage, early intervention can slow progression:  – Blood‑sugar control: Aim for HbA1c targets set by your diabetes team (often <7%).  – Blood‑pressure control: Keep systolic <130 mmHg, using ACE inhibitors or ARBs when appropriate – these drugs also reduce albuminuria.  – Kidney‑protective medicines: ACE‑I/ARB, SGLT2 inhibitors, or GLP‑1 receptor agonists have proven benefit in diabetic kidney disease The Kingsley  Clinic.  – Dietary habits: Moderate protein, limit sodium, stay hydrated, and consider a DASH‑style eating plan.  – Regular monitoring: Repeat ACR and eGFR at least annually, or more often if values are rising. Can the Result Improve? With optimal control of blood sugar, blood pressure, and the use of kidney‑protective drugs, many patients see their ACR move from the moderately increased range back toward normal. Improvement is common, but it does not guarantee that underlying kidney injury has been fully reversed. Warning Signs that Need Immediate Attention If you notice any of the following, contact your healthcare provider promptly:  – Sudden reduction in urine output.  – Rapidly worsening swelling (edema) in legs or face.  – Shortness of breath or difficulty breathing.  – Visible blood in the urine or a dramatic change in colour.  – Severe flank pain. These symptoms may indicate an acute kidney issue that requires urgent evaluation. For deeper insight into how protein in urine relates to kidney disease, see our Protein in Urine Causes article. To learn more about diabetic kidney disease and its early markers, read Diabetic Nephropathy vs CKD. If you are wondering when to see a specialist, our When Should a Person With Diabetes See a Kidney Specialist guide offers practical thresholds. Frequently Asked Questions What does a single high urine ACR result mean? A single elevated ACR indicates possible kidney stress but does not confirm chronic kidney disease; repeat testing is needed to see if the finding persists. How many ACR tests are required to confirm persistent microalbuminuria? Guidelines suggest that at least two out of three ACR measurements taken over 3–6 months must be in the 30–299 mg/g range to confirm persistence. Can lifestyle changes lower my ACR level? Yes. Better blood‑sugar control, blood‑pressure management, reduced sodium intake, and regular moderate exercise have all been shown to lower albumin excretion. When should I see a nephrologist after an abnormal result? If repeat ACR tests remain elevated, or if you have rapidly declining eGFR, uncontrolled hypertension, or other concerning symptoms, a nephrology referral is advised. Do ACE inhibitors
Persistent Proteinuria Evaluation: Tests a Nephrologist May Recommend

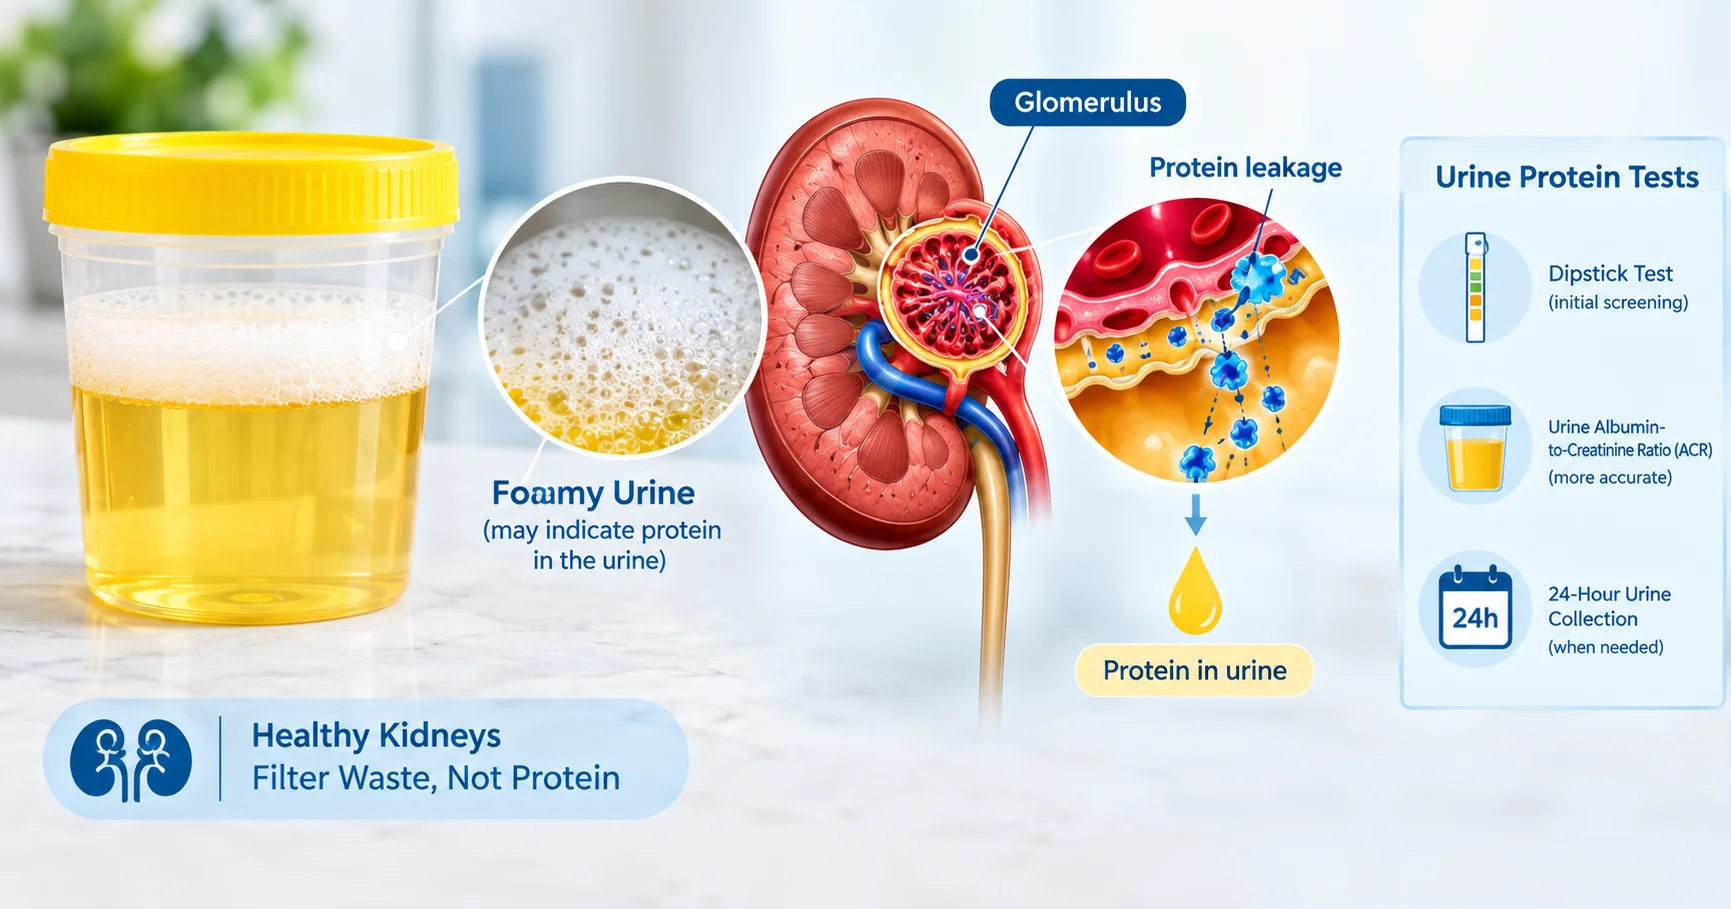
Persistent proteinuria is the continued presence of excess protein in the urine, usually defined as an albumin‑to‑creatinine ratio ≥30 mg/g on two separate samples taken weeks apart. A nephrologist typically orders a urine ACR or PCR, blood tests for kidney function, a renal ultrasound, and may consider a kidney biopsy if the cause remains unclear. Temporary vs. Persistent Proteinuria Protein may appear in urine after strenuous exercise, fever, or a urinary tract infection. This temporary proteinuria resolves once the trigger is removed. Persistent proteinuria is detected on repeat testing and suggests ongoing leakage from the kidney’s filtering units. It can be an early sign of kidney damage, but it does not automatically mean the kidneys have failed. Common Causes of Persistent Proteinuria Diabetes mellitus – high blood sugar damages the glomeruli. Hypertension – elevated pressure injures tiny blood vessels in the kidneys. Glomerular diseases – such as IgA nephropathy, membranous nephropathy, or lupus nephritis. Other kidney conditions – polycystic kidney disease, obstructive uropathy, or chronic kidney disease of other aetiologies. For a deeper look at protein and blood in urine, see our protein and blood in urine page. Symptoms to Watch For Many people with proteinuria feel fine, but some notice: Foamy or frothy urine. Swelling of the ankles, feet, or face (edema). Unexplained fatigue. Occasional blood in the urine (haematuria). Key Laboratory Tests The nephrologist will usually start with the following investigations: Urine Protein‑to‑Creatinine Ratio (PCR/UPCR)Measures total protein; useful when non‑albumin protein is suspected. Test Purpose When Recommended Urine Albumin‑to‑Creatinine Ratio (ACR) Quantifies albumin leakage; first‑line screening. Any persistent proteinuria; ACR ≥30 mg/g.     When ACR is borderline or to assess nephrotic‑range proteinuria. Routine Urinalysis & Microscopy Detects haematuria, casts, crystals, infection. All patients with proteinuria. Serum Creatinine & eGFR Estimates kidney filtration capacity. Baseline assessment and ongoing monitoring. Serum Electrolytes & Albumin Evaluates overall kidney health and nutritional status. When eGFR is reduced or edema is present. Renal Ultrasound Assesses kidney size, echogenicity, and rules out obstruction. If structural abnormality is suspected or eGFR declines. Kidney Biopsy Provides definitive histological diagnosis. Unexplained persistent proteinuria >1 g/day, rapid decline in eGFR, or suspicion of glomerular disease. When Additional Tests Are Needed Beyond the basic panel, the specialist may order: Autoimmune serology (ANA, anti‑DNA, ANCA) if lupus or vasculitis is suspected. Serum complement levels (C3, C4) for immune‑complex diseases. Genetic panels for hereditary kidney disorders. Details on kidney biopsy are available on our kidney biopsy page. Preparing for Your Tests To ensure accurate results, bring the following to your appointment: List of current medications, including over‑the‑counter supplements. Recent lab reports or imaging studies. Details of any recent infections, intense exercise, or fever. Fasting is not required for urine tests, but a morning mid‑stream sample is preferred. Before / During / After Evaluation Stage What Happens Patient Actions Before Review medical history, medication list, and prior test results. Gather documents, note any new symptoms, avoid heavy exercise 24 h before urine collection. During Provide urine sample, blood draw, and possibly an ultrasound. Answer questions, inform staff of allergies, stay hydrated. After Doctor interprets results, discusses need for further testing or treatment. Schedule follow‑up, adhere to any medication adjustments, keep a symptom diary. Interpreting Results and Follow‑Up An ACR of 30–300 mg/g indicates micro‑albuminuria; >300 mg/g suggests overt proteinuria. Persistent elevations usually trigger repeat testing in 3–6 months to confirm trend. If the protein load rises or eGFR falls, the nephrologist may increase monitoring frequency or add imaging/biopsy. Guidelines from the National Kidney Foundation recommend referral when proteinuria is persistent, substantial, or accompanied by declining kidney function nephrology referral guidelines. Detailed work‑up recommendations are outlined in the KDIGO consensus on proteinuria assessment proteinuria workup guidance. Warning Signs Requiring Urgent Assessment Sudden drop in urine output. Severe shortness of breath or rapid weight gain from fluid overload. Marked swelling of the face, hands, or abdomen. New onset of visible blood in the urine. If any of these appear, seek immediate medical attention. Medical Review: This article was reviewed and approved by Dr. Jyoti Bansode, MBBS, MD Medicine and DM Nephrology, with over 10 years of specialised experience in glomerular diseases. All information reflects current clinical guidelines. Ready to discuss your test results? Book an appointment with Dr. Bansode through our appointment and consultation page. Frequently Asked Questions What does a urine ACR test measure? The urine albumin‑to‑creatinine ratio (ACR) estimates how much albumin is excreted relative to creatinine in a single spot urine sample, allowing detection of micro‑ and macro‑albuminuria without a 24‑hour collection. When is a kidney biopsy necessary for proteinuria? A biopsy is usually considered when proteinuria exceeds 1 g/day, when kidney function is rapidly declining, or when the underlying disease cannot be identified through non‑invasive tests. Can proteinuria be reversed? If the cause is treatable—such as uncontrolled diabetes, hypertension, or a reversible medication—proteinuria can improve or even resolve with appropriate therapy and lifestyle changes. Do I need medication for protein in urine? Medication is prescribed only after the underlying cause is identified; for example, ACE inhibitors or ARBs are often used to reduce protein loss in diabetic or hypertensive kidney disease. How often should I have repeat urine tests? For persistent proteinuria, clinicians typically repeat the urine ACR or PCR every 3–6 months to track trends and adjust management as needed. What are the signs that I need urgent nephrology care? Sudden reduction in urine output, severe swelling, shortness of breath, or visible blood in the urine are red‑flag symptoms that require immediate evaluation. Conclusion Persistent proteinuria warrants a systematic evaluation to uncover its cause and protect kidney health. By understanding the key tests and when specialist input is needed, you can partner with your nephrologist for timely, targeted care.

Rising Creatinine in Diabetes: What It Means and What to Do

Answer: A rising creatinine level in a person with diabetes usually indicates that the kidneys are filtering blood less efficiently, often due to diabetic kidney disease, dehydration, medication effects, or acute injury. Prompt medical review is needed to identify the cause and protect kidney function. How Creatinine Reflects Kidney Filtration Creatinine is a waste product formed from muscle metabolism. The kidneys filter it out of the bloodstream and excrete it in urine. Because the body produces creatinine at a relatively constant rate, the blood concentration is a reliable gauge of glomerular filtration rate (GFR). When GFR falls, serum creatinine rises. Common Causes of Rising Creatinine in Diabetes – Long‑term high blood sugar damaging the tiny filtering units (glomeruli) – known as diabetic nephropathy. – High blood pressure (hypertension) that strains kidney blood vessels. – Dehydration or reduced fluid intake, which concentrates blood creatinine. – Medications such as ACE inhibitors, NSAIDs, or certain antibiotics that affect kidney perfusion. – Acute kidney injury from infections, contrast dye, or severe illness. – Obstruction or urinary tract blockage. For a deeper look at how diabetes harms kidneys, see our diabetes and kidney diseases article. Diabetic Kidney Disease (Diabetic Nephropathy) Studies show that patients with uncontrolled diabetes for many years develop structural damage to the glomerular basement membrane, leading to protein leakage and a gradual rise in creatinine PMC study. This process is often silent until routine labs pick up the change. Early Symptoms and Warning Signs Most people do not feel symptoms until kidney function is markedly reduced, but watch for: Swelling in ankles or feet. Unexplained fatigue or weakness. Changes in urine volume or colour. Persistent nausea or loss of appetite. Muscle cramps, especially at night. If you notice sudden swelling, severe nausea, or a creatinine jump above 2 mg/dL, seek urgent care. Temporary Elevation vs. Chronic Kidney Disease Creatinine can spike temporarily after dehydration, intense exercise, or a short‑term medication change. In chronic kidney disease (CKD), the rise is progressive and persists across multiple tests. Distinguishing the two requires repeat measurements and additional tests. Key Kidney Tests for People with Diabetes   Test What It Shows Serum Creatinine Current waste level; higher = lower filtration. eGFR Estimated GFR based on creatinine, age, sex, and race. Urine Albumin‑to‑Creatinine Ratio (ACR) Detects protein leakage; early sign of nephropathy. HbA1c Average blood sugar over 3 months; high values accelerate kidney damage. Electrolytes (Na, K, Bicarbonate) Assess kidney’s ability to balance fluids and acids. eGFR Categories Stage eGFR (mL/min/1.73 m²) Interpretation 1 >90 Normal or high; kidney damage may still be present. 2 60‑89 Mild decrease; monitor closely. 3a 45‑59 Moderate decrease; consider specialist referral. 3b 30‑44 Moderately severe; nephrology input advised. 4 15‑29 Severe reduction; preparation for possible dialysis. 5 <15 Kidney failure (end‑stage). Urine ACR Categories Result Albumin (mg/g) Risk Level Normal <30 Low risk. Microalbuminuria 30‑300 Early kidney damage. Macroalbuminuria >300 Advanced nephropathy. Our detailed guide to urine tests can be found in Kidney Tests Explained: Creatinine, eGFR, Urine ACR & Electrolytes. Why a Normal Creatinine Doesn’t Always Mean Healthy Kidneys Creatinine is influenced by muscle mass, diet, and hydration. Early diabetic kidney disease often shows normal serum creatinine while urine ACR is already elevated. Therefore, regular screening with eGFR and ACR is essential even if creatinine looks fine. Kidney‑Protection Strategies for People with Diabetes – Maintain tight blood‑sugar control (HbA1c <7%). – Keep blood pressure below 130/80 mmHg, preferably with ACE inhibitors or ARBs. – Stay well‑hydrated; aim for 1.5–2 L of fluid daily unless contraindicated. – Review medications with your doctor; avoid unnecessary NSAIDs. Adopt a kidney‑friendly diet low in sodium and processed protein. – Exercise regularly but avoid extreme muscle‑building workouts that can raise creatinine. For more on protein and blood in urine, read protein and blood in urine. When to Consult a Nephrologist Schedule a specialist appointment if any of the following occur: – eGFR falls below 60 mL/min/1.73 m² (Stage 3) on two separate tests. – Urine ACR shows micro‑ or macro‑albuminuria. – Serum creatinine rises rapidly (>0.3 mg/dL within weeks) without an obvious cause. – Persistent swelling, high blood pressure, or electrolyte abnormalities. Our clinic makes it easy to book a visit – see appointment and consultation for details. Expert Insight Dr. Jyoti Bansode, MBBS, MD Medicine, DM Nephrology, brings over 15 years of experience managing diabetic kidney disease. Her evidence‑based approach combines lifestyle counselling with personalised medication plans to slow progression and improve quality of life. For further reading on the link between diabetes and creatinine, consult the Healthgrades guide and the UCLA Health article. Frequently Asked Questions Can a single high creatinine test mean I have kidney failure? Not necessarily. A one‑time rise can be due to dehydration, recent exercise, or medication. Your doctor will repeat the test and look at eGFR and urine ACR to determine if the change is temporary or indicative of chronic disease. Why is urine albumin important if my creatinine is normal? Albumin leaks into urine long before serum creatinine rises. Detecting micro‑albuminuria allows treatment to start early, potentially halting further kidney damage. Do ACE inhibitors raise creatinine levels? ACE inhibitors may cause a modest, temporary increase in creatinine as they reduce intraglomerular pressure, but they protect the kidneys long‑term by lowering blood pressure and protein loss. How often should a person with diabetes check kidney function? Guidelines recommend checking serum creatinine, eGFR, and urine ACR at least once a year, or more frequently if any abnormality or rapid change is detected. Can lifestyle changes lower a high creatinine level? Yes. Proper hydration, blood‑sugar control, blood‑pressure management, and avoiding nephrotoxic drugs can improve kidney filtration and bring creatinine back toward normal. When is dialysis needed for diabetic kidney disease? Dialysis is considered when eGFR falls below 15 mL/min/1.73 m², symptoms of kidney failure appear, or complications like severe electrolyte imbalance develop. Conclusion If your creatinine is rising, don’t wait – discuss the result with your doctor, repeat the test, and explore the full panel of kidney assessments. Early action can preserve kidney function and keep diabetes under control.

Diabetic Kidney Disease with Normal Creatinine – What You Need to Know

Yes, diabetic kidney disease can be present even when serum creatinine is within the normal laboratory range. Creatinine alone may miss early kidney damage because albumin leakage in urine often appears before a significant fall in the kidneys’ filtering ability. Why Creatinine Can Remain Normal in Early Diabetic Kidney Disease Serum creatinine reflects the overall filtration capacity of the kidneys, but it does not detect subtle damage to the glomerular filter. In the early stages of diabetic nephropathy, the glomerular basement membrane becomes leaky, allowing albumin to pass into the urine while the total filtration rate (and thus creatinine) stays within normal limits. Therefore, a patient can have: Normal creatinine Relatively preserved eGFR Elevated urine albumin (high urine ACR) and still have evidence of kidney damage. How Diabetes Damages the Glomeruli Prolonged high blood glucose damages the tiny blood vessels that line the glomeruli – the kidney’s filtering units. The excess glucose triggers inflammation and thickening of the basement membrane, making it porous. The first sign is usually a small amount of albumin spilling into the urine (microalbuminuria). Over time, continued injury can reduce the number of functional nephrons, leading to a drop in eGFR and, eventually, chronic kidney disease. Creatinine vs eGFR vs Urine ACR Each test answers a different question about kidney health. Understanding their roles helps catch disease early. Test What It Measures Typical Use Creatinine Blood waste product from muscle metabolism Basic screen; high levels suggest reduced filtration eGFR Estimated glomerular filtration rate (calculates filtration based on creatinine, age, sex, race) Quantifies overall kidney function Urine ACR Albumin‑to‑creatinine ratio in a spot urine sample Detects early leak of protein (albumin) from glomeruli Because they assess different aspects, clinicians interpret them together rather than in isolation. Can eGFR Be Normal in Early Diabetic Kidney Disease? Yes. In the initial phases of diabetic nephropathy, the eGFR often remains >90 mL/min/1.73 m² while urine ACR is already elevated. A normal eGFR does not guarantee that the kidneys are healthy; persistent albuminuria signals early injury even when filtration appears preserved. Current Screening Guidance for Diabetes Guidelines from the American Diabetes Association and KDIGO recommend: People with type 2 diabetes: urine ACR and eGFR testing at least once a year from the time of diagnosis. People with type 1 diabetes: begin annual kidney screening after about five years of diabetes duration, unless other risk factors call for earlier testing. Regular monitoring helps detect changes before symptoms appear. Early Warning Signs (Often Absent) Early diabetic kidney disease usually has no noticeable symptoms. When it progresses, patients may notice: Foamy or frothy urine (protein) Swelling of the feet or ankles Increasing blood pressure Fatigue or reduced energy Changes in urination frequency Nausea or loss of appetite Can a High Urine ACR Be Temporary? Transient factors can raise urine albumin, including intense exercise, fever, urinary‑tract infection, marked hyperglycaemia, menstruation, heart failure, or a sudden spike in blood pressure. One abnormal ACR result does not automatically confirm chronic kidney disease; repeat testing after a few weeks is recommended to verify persistence. What Test Results May Suggest Early Kidney Damage? Look for patterns such as: Normal serum creatinine + elevated urine ACR. Preserved eGFR + elevated urine ACR. Gradual decline in eGFR over months or years. Increasing albumin levels on consecutive ACR tests. These findings indicate that the kidneys are under stress even if the filtration rate seems normal. What Should You Do If Creatinine Is Normal but You Have Diabetes? Discuss the following with your clinician: Request a urine ACR test. Ask for an eGFR calculation based on your latest labs. Review previous creatinine results to spot trends. Review prior urine ACR results, if available. Check your blood pressure readings. Know your most recent HbA1c level. Ask whether repeat urine testing is needed to confirm any abnormality. Inquire if your kidney‑function numbers are changing over time. When Should You See a Nephrologist? Referral is appropriate when any of the following occur: Persistently elevated urine ACR (especially >300 mg/g). Rapid increase in albuminuria over a short period. Steady decline in eGFR (e.g., drop >5 mL/min/1.73 m² per year). Persistent protein or blood in urine protein and blood in urine. Difficult‑to‑control hypertension despite medication. Unexplained swelling (edema). Sudden or unexplained changes in kidney‑function test results. Uncertainty about the cause of abnormal kidney tests acute and chronic kidney diseases. Referral does not mean you have end‑stage disease; it ensures specialized care to slow progression. Why Early Detection Matters Interventions such as tighter glucose control, blood‑pressure management (often with ACE inhibitors or ARBs), lifestyle changes, and regular monitoring can significantly slow the progression of diabetic kidney disease. Medical Review: Dr. Jyoti BansodeMBBS, MD Medicine, DM NephrologyMore than 10 years of nephrology experience For a deeper look at how diabetes affects kidney health, see our diabetes and kidney diseases page. If you notice persistent protein or blood in your urine, read our protein and blood in urine guide. For broader information on chronic kidney conditions, explore acute and chronic kidney diseases. Key sources:  American Heart Association overview of kidney disease in diabetes, bidirectional link study between diabetes and kidney disease, KDIGO‑style review of diabetic kidney disease. Frequently Asked Questions Can diabetic kidney disease happen with normal creatinine? Yes. Early kidney damage can cause albumin to leak into urine while serum creatinine remains within the normal range. Can kidney damage occur with a normal eGFR? Yes. Albuminuria can be present even when eGFR is >90 mL/min/1.73 m², indicating early glomerular injury. Which test detects diabetic kidney disease earliest? Urine ACR (albumin‑to‑creatinine ratio) is the most sensitive early marker, detecting microalbuminuria before creatinine or eGFR change. Is urine ACR more useful than creatinine for early kidney damage? For early detection, yes. Urine ACR identifies tiny amounts of albumin that appear before serum creatinine rises. Can albumin in urine be temporary? Transient factors like exercise, infection, fever, or high blood pressure can raise urine albumin; repeat testing confirms persistence. When should a person with diabetes see a nephrologist? See a nephrologist if urine ACR stays high, eGFR declines, protein/blood persists in urine, hypertension is uncontrolled,

Urine ACR Test Explained: Why Albumin in Urine Matters

When your doctor orders a urine albumin‑creatinine ratio (ACR) test, the goal is to catch early signs of kidney stress before symptoms appear. This guide breaks down the science in plain language, explains what the numbers mean, and shows you how to prepare for accurate results. Medical Review: Dr. Jyoti Bansode, MBBS, MD Medicine, DM Nephrology – >10 years of nephrology experience. What the Urine ACR Test Measures The ACR test quantifies two substances in a single, random‑spot urine sample: albumin (a protein that belongs in the bloodstream) and creatinine (a waste product filtered by the kidneys). The laboratory divides the albumin concentration (mg) by the creatinine concentration (g) to produce a ratio expressed as mg/g. Because creatinine corrects for urine concentration, the ACR is more reliable than a simple dip‑stick protein test. For a detailed explanation, see Dr. Jyoti Bansode’s article. Albumin vs. Creatinine Albumin should stay in the blood; the kidneys act as a sieve that prevents it from leaking into urine. Creatinine, on the other hand, is a by‑product of muscle metabolism that the kidneys normally excrete. By comparing the two, the ACR tells you whether the filtration barrier is compromised. Why Albumin in Urine Matters Even tiny amounts of albumin (called microalbuminuria) signal that the glomeruli—the tiny filtering units—are under stress. Persistent albuminuria is linked to a higher risk of chronic kidney disease (CKD), cardiovascular events, and progression to end‑stage renal disease. The National Kidney Foundation notes that albuminuria is a red flag for both kidney and heart health NKF uACR overview. Understanding ACR Result Ranges Normal: < 30 mg/g – no significant albumin loss. Microalbuminuria: 30–300 mg/g – early kidney damage; warrants repeat testing and risk‑factor control. Macroalbuminuria: >300 mg/g – overt proteinuria; indicates more advanced disease. These cut‑offs are widely accepted in clinical practice and help guide treatment decisions NKF uACR overview. Common Causes of a High ACR Diabetes mellitus – high blood sugar damages glomerular capillaries. Hypertension – elevated pressure strains the filtration barrier. Glomerulonephritis or other inflammatory kidney diseases. Infections (e.g., urinary tract infection, fever). Medications such as non‑steroidal anti‑inflammatory drugs (NSAIDs) or certain antibiotics. For a deeper look at how diabetes triggers albuminuria, read our Understanding Microalbuminuria in Diabetes. Temporary Factors That Can Skew Results Not every elevated ACR means chronic disease. Transient conditions can raise albumin temporarily: Intense exercise or heavy lifting (muscle breakdown releases creatinine). Fever or acute illness. Dehydration – concentrates urine, raising the ratio. High‑protein meals within the previous 24 hours. Menstrual blood contamination. If any of these apply, your clinician may repeat the test after a few days. Interpreting ACR with eGFR and Creatinine ACR is most powerful when viewed alongside estimated glomerular filtration rate (eGFR) and serum creatinine. A normal eGFR with a high ACR suggests early glomerular injury, while a low eGFR with a modest ACR may reflect advanced CKD. Our Kidney Tests Explained: Creatinine, eGFR, Urine ACR & Electrolytes article walks through the combined interpretation. Laboratories such as Labcorp calculate the ratio automatically and flag results that exceed risk thresholds Labcorp ACR test details. Diabetes, Hypertension, and Cardiovascular Risk Albuminuria is not just a kidney issue; it predicts heart attacks, strokes, and peripheral artery disease. People with diabetes and high blood pressure are up to three times more likely to develop albuminuria, and each 30 mg/g increase in ACR raises cardiovascular risk by roughly 10 % according to the National Kidney Foundation NKF uACR risk page. How Often Should You Repeat the Test? Guidelines recommend: Annual screening for anyone with diabetes or hypertension. Every 1–2 years for individuals with other CKD risk factors (family history, age > 60). Repeat within 3–6 months if the first result is abnormal, after addressing any temporary factors. When to See a Nephrologist Schedule a specialist appointment if you meet any of the following: ACR > 300 mg/g on two separate occasions. eGFR < 60 mL/min/1.73 m² combined with any albuminuria. Rapidly rising ACR (increase > 30 % within 3 months). Persistent proteinuria despite optimal blood‑pressure and glucose control. Our guide on specialist referral can help you prepare for the visit: When Should You See a Nephrologist in Navi Mumbai?. Practical Patient Checklist Before Your ACR Test Collect a mid‑stream, clean‑catch urine sample in the morning if possible. Avoid vigorous exercise for 24 hours prior. Stay well‑hydrated, but do not over‑drink immediately before the test. Notify the lab if you have a fever, infection, or recent heavy protein intake. Bring a list of current medications (especially NSAIDs, ACE inhibitors, or ARBs). Following these steps improves accuracy and reduces the need for repeat testing. Frequently Asked Questions What does a normal urine ACR result look like? A normal ACR is less than 30 mg of albumin per gram of creatinine, indicating that the kidneys are effectively retaining protein. Can a single high ACR result be ignored? No. A single elevated ACR should be repeated after 3–6 months, especially if you had recent fever, intense exercise, or dehydration that could temporarily raise the ratio. Why is the ACR preferred over a simple urine protein dip‑stick? The ACR corrects for urine concentration by using creatinine as a reference, making it more reliable than a dip‑stick, which can be falsely low in dilute urine or high in concentrated samples. How does diabetes affect the urine ACR? High blood glucose damages the glomerular filter, allowing albumin to leak into urine. Even early diabetes can cause microalbuminuria (30–300 mg/g), which signals the need for tighter glucose and blood‑pressure control. When should I see a nephrologist after an abnormal ACR? If your ACR exceeds 300 mg/g, if eGFR falls below 60 mL/min/1.73 m², or if albuminuria rises rapidly despite treatment, a referral to a nephrologist is recommended. Conclusion Understanding your urine ACR result empowers you to act early, protect kidney function, and lower cardiovascular risk. Talk to your healthcare provider about the next steps, whether that means lifestyle changes, medication adjustments, or a referral to a nephrologist.

Urine ACR Test Explained: Why Albumin in Urine Matters

The urine albumin‑creatinine ratio (urine ACR test) is a quick, inexpensive way to spot early kidney damage before symptoms appear. By comparing the amount of albumin (a protein) to creatinine (a waste product) in a single urine sample, doctors can detect albuminuria, monitor disease progression, and guide treatment for conditions like diabetes and hypertension. What Is a Urine ACR Test? A urine ACR test measures the concentration of albumin and creatinine in a spot urine sample and then calculates the ratio, usually expressed in milligrams of albumin per gram of creatinine (mg/g). This ratio corrects for variations in urine concentration, making it more reliable than a simple urine protein test. According to the National Kidney Foundation, the uACR is the preferred screening tool for detecting albuminuria in people at risk for chronic kidney disease (CKD). Why Is the Urine ACR Test Done? Kidneys filter waste while keeping essential proteins like albumin in the bloodstream. When the glomeruli become damaged, albumin leaks into the urine, a condition called albuminuria or proteinuria. Detecting this leak early can: Identify early-stage CKD before eGFR declines. Stratify cardiovascular risk, since albuminuria is an independent predictor of heart disease. Guide medication choices for diabetes, hypertension, and other kidney‑affecting conditions. For people with diabetes, the Kidney Fund notes that routine uACR screening is essential because diabetic kidney disease often begins with microalbuminuria. How Is a Urine ACR Test Done? The test requires a clean‑catch midstream urine sample, which can be collected at home or in a clinic. No fasting is needed, but the sample should be taken when the bladder is neither empty nor overly full. The laboratory measures albumin (mg) and creatinine (g) and reports the ratio. Some labs also provide a separate urine albumin test and a urine creatinine test, but the combined ratio is what clinicians use for interpretation. Understanding Urine ACR Results Results are categorized by the National Kidney Foundation as follows: Understanding urine ACR result with kidney illustration and normal, moderately increased, and severely increased UACR ranges UACR (mg/g) Albuminuria Category What It Means < 30 mg/g Normal to Mildly Increased Usually considered within the normal range. 30–299 mg/g Moderately Increased May indicate early kidney damage or albuminuria. ≥ 300 mg/g Severely Increased May indicate more significant kidney damage and needs medical evaluation. A result under 30 mg/g is considered normal, while values between 30 and 299 mg/g indicate microalbuminuria—a warning sign that kidney damage may be beginning. Values of 300 mg/g or higher reflect macroalbuminuria, which usually means more advanced kidney disease. It’s important to remember that a single abnormal result does not automatically diagnose CKD. The NIDDK recommends repeating the urine ACR test one to two more times over a 3‑month period to confirm persistent albuminuria before labeling someone with chronic kidney disease. UACR vs. Other Urine Protein Tests Traditional urine protein tests measure total protein, which can be influenced by hydration status and muscle mass. The urine ACR test, by normalizing albumin to creatinine, provides a more stable estimate of kidney filtration function. This is why clinicians often prefer the uACR over a generic urine protein test when monitoring diabetic patients or those with hypertension. Key Situations When a Urine ACR Test Is Recommended How is a urine ACR test done showing urine collection, albumin measurement, creatinine measurement, and UACR calculation Annual screening for adults with diabetes or hypertension. Evaluation of unexplained swelling, foamy urine, or decreased urine output. Baseline assessment before starting potentially nephrotoxic medications (e.g., NSAIDs, certain antibiotics). Follow‑up after a previous abnormal ACR to assess treatment response. For a deeper dive into related kidney tests, see our Kidney Tests Explained: Creatinine, eGFR, Urine ACR & Electrolytes. Interpreting High Urine ACR Results When the urine ACR is above 30 mg/g, clinicians consider several possible causes: Early diabetic nephropathy or other forms of CKD. Acute conditions such as urinary tract infection, fever, or intense exercise. Medications that affect kidney function. Addressing reversible factors—like treating an infection or adjusting medication—can sometimes bring the ACR back into the normal range. Lifestyle changes (tight blood‑pressure control, low‑protein diet, smoking cessation) also help lower albuminuria over time. Link Between UACR and eGFR eGFR estimates how well the kidneys filter blood, while uACR detects leakage of protein. Both are complementary: a normal eGFR with a high uACR signals early kidney damage, whereas a low eGFR with a normal uACR may indicate non‑proteinuric CKD. Combining these metrics improves risk stratification, as highlighted by the Labcorp ACR test description. Practical Tips for Accurate Testing To ensure reliable results, follow these guidelines: Collect the sample first thing in the morning, if possible. Avoid heavy exercise, high‑protein meals, and NSAIDs for 24 hours before the test. Store the sample in a cool place and deliver it to the lab within 24 hours. Inform your provider about any recent infections or medications. For more on how to prepare for lab tests, read our Protein in Urine Child: When to Seek Kidney Care. When to Repeat the Test If your first urine ACR result is abnormal, most clinicians will repeat the test after 2–4 weeks to confirm persistence. For patients with known CKD, the test may be ordered every 3–6 months, depending on disease stability and treatment changes. Diabetic patients are often advised to have a urine ACR at least once a year, as recommended by the American Diabetes Association. Can High Urine ACR Be Reversed? Yes, in many cases. Tight glycemic control, blood‑pressure management (especially with ACE inhibitors or ARBs), and lifestyle modifications have been shown to reduce albuminuria. Studies cited by the Siemens Healthineers indicate that up to 30 % of patients can achieve a return to the normal range with appropriate therapy. Ultimately, early detection through regular urine ACR screening empowers patients and providers to intervene before irreversible kidney damage occurs. Frequently Asked Questions What is a urine ACR test? A urine ACR test measures the albumin‑to‑creatinine ratio in a spot urine sample, providing a snapshot of how much albumin is leaking into the urine relative to creatinine. What does a high

Kidney Tests Explained: Creatinine, eGFR, Urine ACR & Electrolytes

Kidney Tests Explained: Creatinine, eGFR, Urine ACR & ElectrolytesUnderstanding kidney function starts with the right lab tests. Creatinine, eGFR, urine albumin‑to‑creatinine ratio (uACR) and electrolyte panels are the four pillars doctors use to spot early disease, track progression, and guide treatment. This guide breaks down each test, normal values, and what the numbers mean for you. Medical Review – Dr. Jyoti BansodeMBBS, MD Medicine, DM NephrologyOver 10 years of experience in diagnosing and managing kidney disease. For personalized care, visit Dr. Bansode’s nephrology services. Why Kidney Function Testing Matters Kidneys filter waste, balance fluids, and regulate electrolytes. When they falter, waste builds up, blood pressure spikes, and vital minerals become imbalanced. Early detection through lab testing can prevent irreversible damage and reduce the need for dialysis or transplant. Common Symptoms That Prompt Testing Persistent fatigue or weakness Swelling in ankles, feet, or face Changes in urine color or frequency Unexplained high blood pressure Muscle cramps or tingling sensations If you notice any of these, ask your primary‑care physician for a kidney panel. Key Kidney Tests Overview Key Kidney Tests Overview Serum Creatinine – What It Shows Creatinine is a waste product from muscle metabolism. The kidneys clear it from the blood, so higher levels indicate reduced filtration. Normal ranges vary by sex and muscle mass, but typical limits are 0.6–1.2 mg/dL for women and 0.7–1.3 mg/dL for men Nephrology Specialists. Values above these thresholds often signal early kidney stress. Estimated Glomerular Filtration Rate (eGFR) eGFR translates the creatinine value into an estimate of how many milliliters of blood the kidneys filter each minute per 1.73 m² of body surface. An eGFR > 60 mL/min/1.73 m² is generally considered normal, 30–59 suggests moderate decline, and <30 indicates severe kidney disease MyNephrologist. The calculation also incorporates age, sex, and sometimes race, making it a more comprehensive indicator than creatinine alone. Urine Albumin‑to‑Creatinine Ratio (uACR) Albumin is a protein that should stay in the bloodstream. When the glomeruli are damaged, albumin leaks into urine. uACR compares the amount of albumin to creatinine in a single urine sample, eliminating the need for a 24‑hour collection. Normal uACR is 300 mg/g reflects macro‑albuminuria (significant damage) MyNephrologist. This test can detect kidney injury years before eGFR drops. Electrolytes and Blood Urea Nitrogen (BUN) Electrolyte panels measure sodium, potassium, chloride, bicarbonate, and calcium—minerals the kidneys tightly regulate. Abnormalities often accompany chronic kidney disease (CKD). BUN, another waste product, rises as kidney function declines but is less specific than creatinine because it is influenced by diet and hydration Nephrology Specialists. Interpreting Results Together Creatinine & eGFR Relationship Because eGFR is derived from creatinine, the two numbers should be read as a pair. A mildly elevated creatinine with a normal eGFR may be due to high muscle mass, while a normal creatinine with a low eGFR often points to early CKD, especially in older adults. When uACR Raises a Red Flag Even with a healthy eGFR, a uACR > 30 mg/g signals that the kidney’s filtering units are leaking protein. This early sign is common in diabetes and hypertension and warrants tighter blood‑sugar or blood‑pressure control, plus possible referral to a nephrologist. Electrolyte Imbalance Clues High potassium (hyperkalaemia) can indicate reduced excretion, while low sodium often reflects fluid overload. Metabolic acidosis (low bicarbonate) is another hallmark of advanced CKD. Spotting these changes early allows dietary or medication adjustments before complications arise. When to Seek Specialist Care If any of the following appear, schedule a consultation with a kidney specialist: eGFR consistently below 60 mL/min/1.73 m² uACR ≥ 30 mg/g on two separate tests Persistent electrolyte abnormalities despite treatment Rapid rise in serum creatinine (e.g., >0.3 mg/dL in 48 hours) Our clinic’s nephrology team can provide a detailed assessment and personalized plan. Learn more about when to see a specialist in When Should You See a Nephrologist in Navi Mumbai?. Common Myths About Kidney Tests Myth: “If my creatinine is normal, my kidneys are fine.” – Fact: Creatinine alone can miss early damage; uACR often reveals problems first. Myth: “Only diabetics need kidney testing.” – Fact: Hypertension, family history, and age over 50 are also risk factors. Myth: “Low potassium always means a kidney problem.” – Fact: Diet, medications, and gastrointestinal loss can also lower potassium. Putting It All Together: A Practical Checklist Use this quick reference during your next lab visit: Kidney Test Typical / Reference Range When to Seek Medical Attention Serum Creatinine Reference ranges vary by laboratory, age, sex, and muscle mass. A persistently elevated or rising creatinine level may require further evaluation. eGFR Generally ≥60 mL/min/1.73 m² An eGFR below 60 that persists for 3 months or longer may indicate chronic kidney disease. Urine ACR (uACR) <30 mg/g 30–300 mg/g indicates moderately increased albuminuria; >300 mg/g indicates severely increased albuminuria. Electrolytes(Na, K, Cl, HCO₃) Within your laboratory’s reference range Persistent or significant abnormalities, particularly potassium or bicarbonate changes, require medical assessment. BUN Typically about 7–20 mg/dL, depending on the laboratory An elevated BUN should be interpreted together with creatinine, eGFR, hydration status, and other clinical findings. Regular monitoring—typically every 6–12 months for at‑risk patients—helps catch changes early. For detailed guidance on test frequency, see our When Is Dialysis Needed? Symptoms, eGFR & Clinical Factors page. By understanding what each number represents, you can partner with your healthcare team to protect kidney health before problems become serious. Frequently Asked Questions What should patients know first about kidney disease tests? Kidney tests measure waste removal (creatinine, eGFR), protein leakage (uACR), and mineral balance (electrolytes). Together they reveal how well the kidneys filter blood and whether early damage is present.   Which kidney tests are most relevant for early detection? The urine albumin‑to‑creatinine ratio (uACR) is the most sensitive early marker, often detecting damage before eGFR declines. Serum creatinine and eGFR confirm overall filtration capacity.   What symptoms should prompt evaluation? Persistent fatigue, swelling, changes in urine, high blood pressure, and unexplained muscle cramps should trigger a kidney panel, including creatinine, eGFR, uACR, and electrolytes.   How are creatinine and eGFR interpreted together? Creatinine provides the raw waste level, while eGFR translates it into an estimated filtration