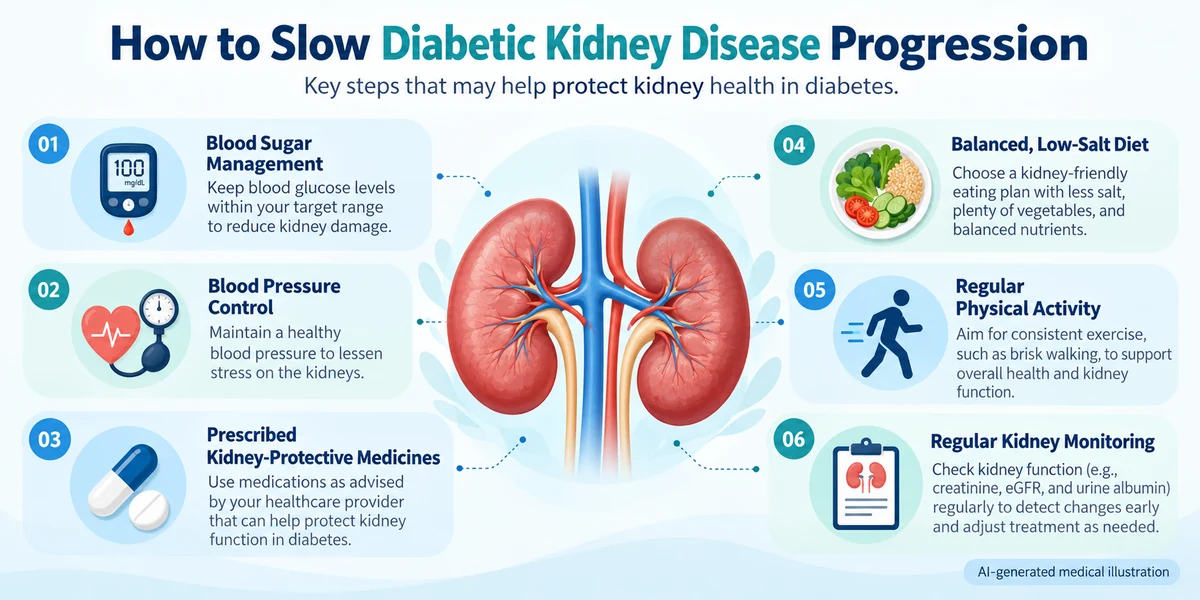
Diabetic kidney disease progression can often be slowed through appropriate blood glucose management, blood pressure control, kidney-protective medicines, dietary measures, physical activity and regular kidney monitoring. However, treatment outcomes vary, and no approach guarantees that kidney damage will stop or reverse completely. Diabetic kidney disease (DKD) can develop gradually, sometimes without noticeable symptoms. Early abnormalities may appear as increased albumin in urine, reduced estimated glomerular filtration rate (eGFR), or both. Monitoring urine albumin-to-creatinine ratio (uACR) and eGFR helps identify kidney abnormalities and track changes over time. This article explains ten evidence-based approaches to managing diabetic kidney disease, including treatment considerations, diet, kidney testing and warning signs. What Is Diabetic Kidney Disease? Diabetic kidney disease refers to kidney damage associated with diabetes. The kidneys contain microscopic filtering structures called glomeruli. These structures help remove waste products and excess fluid from the bloodstream while retaining most essential proteins. Long-term elevated blood glucose can affect the kidneys’ blood vessels and filtering structures. Possible changes include: Increased albumin leakage into urine. Injury to the glomerular filtration barrier. Gradual reduction in kidney filtration. Changes in fluid and electrolyte balance as dysfunction advances. Increased risk of cardiovascular complications. High blood pressure may contribute to further kidney injury. However, not everyone with diabetes develops kidney disease, and not every abnormal kidney result in someone with diabetes is caused by diabetes. For related information, read Diabetic Kidney Disease Symptoms. Can Diabetic Kidney Disease Progression Be Slowed? Yes. Appropriate medical management can reduce the risk of kidney disease progression in eligible patients. Treatment may help reduce albuminuria, slow the decline in eGFR and lower the risk of certain cardiovascular complications. However, the response depends on several factors: Existing kidney function. Urine albumin levels. Duration and type of diabetes. Blood pressure. Cardiovascular health. Other kidney disorders. Current medicines and treatment tolerance. Some people experience stable kidney function or improved urine albumin measurements. Others may continue to experience declining kidney function despite appropriate treatment. Slowing progression is not the same as curing established chronic kidney disease. What Increases the Risk of Diabetic Kidney Disease Progression? Several factors may contribute to kidney-related risk. Persistently Elevated Blood Glucose Long-term hyperglycaemia may contribute to blood vessel injury and changes in kidney filtration. High Blood Pressure Hypertension can worsen kidney damage and increase cardiovascular risk. Increased Urine Albumin Persistent albuminuria is associated with kidney damage and may indicate an increased risk of progression. Declining eGFR A sustained decline in eGFR may suggest worsening kidney filtration. Cardiovascular Disease Heart and blood vessel conditions frequently coexist with chronic kidney disease. Tobacco Use Smoking increases vascular and cardiovascular risks. Other medical conditions, certain medicines, acute kidney injury and urinary obstruction may also affect kidney function. The overall risk should be assessed using clinical findings and changes in laboratory results over time. 10 Evidence-Based Ways to Slow Diabetic Kidney Disease Progression 1. Manage Blood Glucose According to Individual Targets Appropriate blood glucose management is important for reducing diabetes-related complications. HbA1c reflects average blood glucose over approximately the previous two to three months. A target near 7% may be suitable for many non-pregnant adults with diabetes, but it is not appropriate for everyone. Individual HbA1c targets depend on: Age and general health. Risk of hypoglycaemia. Kidney function. Diabetes duration. Cardiovascular disease. Other medical conditions. Current treatment. In people with advanced kidney disease, HbA1c interpretation may sometimes be affected by anaemia and changes in red blood cell turnover. Home glucose monitoring or continuous glucose monitoring may provide additional information when appropriate. Patients should not adjust prescribed diabetes medicines independently to reach a particular HbA1c target. 2. Control Blood Pressure High blood pressure is an important contributor to kidney and cardiovascular complications. Blood pressure management may help reduce the risk of diabetic kidney disease progression. For many adults with diabetes, a blood pressure target below 130/80 mmHg may be considered when safely achievable. However, targets should be individualised according to clinical circumstances and treatment tolerance. Excessively aggressive treatment can cause problems such as dizziness, low blood pressure or reduced circulation in susceptible individuals. Management may include: Appropriate prescribed medicines. Reducing excessive dietary sodium. Physical activity. Weight management when indicated. Home blood pressure monitoring where appropriate. Not everyone needs the same monitoring frequency or medicine combination. 3. Use Kidney-Protective Medicines When Appropriate Certain medicines have demonstrated kidney or cardiovascular benefits in eligible patients. Their suitability depends on diabetes type, eGFR, urine albumin, blood pressure, associated conditions and potential adverse effects. ACE Inhibitors and ARBs Angiotensin-converting enzyme inhibitors (ACE inhibitors) and angiotensin receptor blockers (ARBs) may reduce albuminuria and kidney-related risk in selected people, particularly when hypertension and albuminuria are present. They can affect serum creatinine, potassium and blood pressure. Monitoring may be needed after starting treatment or adjusting the dose. ACE inhibitors and ARBs should not routinely be combined. SGLT2 Inhibitors Certain sodium-glucose cotransporter-2 (SGLT2) inhibitors have demonstrated benefits in reducing kidney disease progression and cardiovascular events. They are recommended for many eligible people with type 2 diabetes and CKD. Potential adverse effects include genital infections, volume depletion and, rarely, ketoacidosis. Medication management during acute illness or around certain procedures may require specific medical guidance. GLP-1 Receptor Agonists Selected glucagon-like peptide-1 receptor agonists may offer kidney and cardiovascular benefits in people with type 2 diabetes and CKD. Potential adverse effects and contraindications must be considered. Nonsteroidal Mineralocorticoid Receptor Antagonists Finerenone may benefit selected people with type 2 diabetes, CKD and persistent albuminuria. It can increase potassium and requires appropriate clinical and laboratory monitoring. Important: Not everyone requires every kidney-protective medicine. Prescribing decisions should be made by a qualified healthcare professional. 4. Reduce Excessive Salt Intake Excess dietary sodium can contribute to high blood pressure and fluid retention. Reducing excessive salt intake may support blood pressure and kidney management. KDIGO guidance suggests sodium intake below approximately 2 grams per day, equivalent to about 5 grams of salt, for many adults with CKD. However, dietary advice should be individualised. Certain medical conditions may require a different approach. Practical measures include: Reducing added salt during