+91 8691888178 / 8850999397 dr.jyotibansode.01@gmail.com Monday to Saturday : 05:00PM TO 06:00PM

Urine ACR Test Explained: Why Albumin in Urine Matters

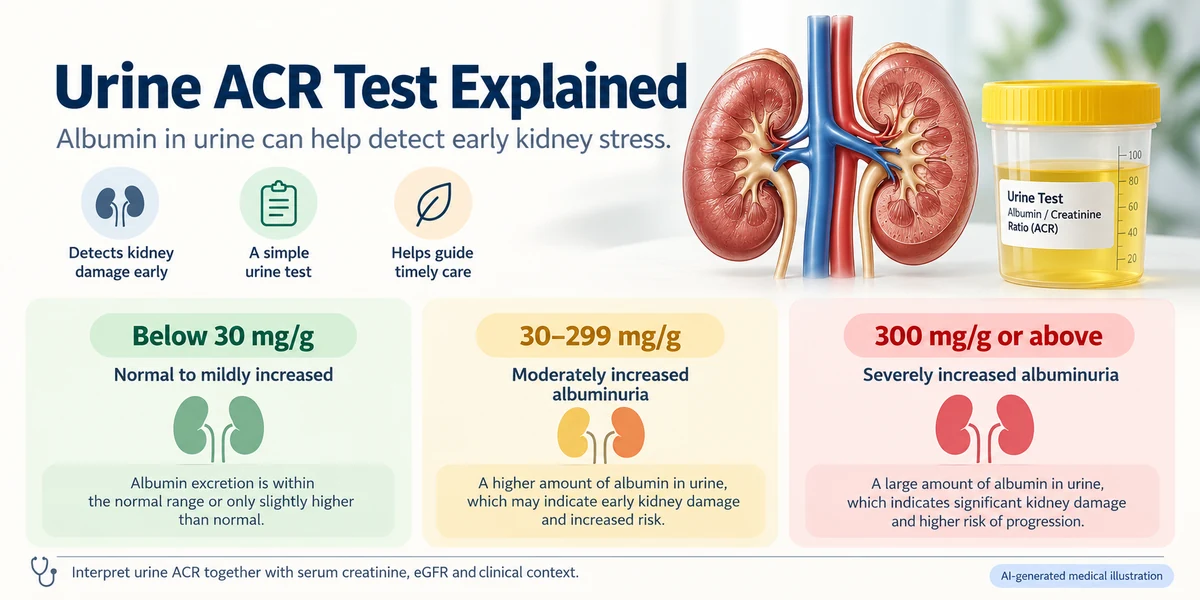
The urine albumin-to-creatinine ratio (urine ACR or uACR) test measures albumin relative to creatinine in a urine sample. It helps detect increased albumin leakage, which may be a marker of kidney damage even when serum creatinine and estimated glomerular filtration rate (eGFR) are relatively normal. A urine ACR below 30 mg/g is classified as normal to mildly increased, 30–299 mg/g as moderately increased, and 300 mg/g or above as severely increased albuminuria. However, a single high urine ACR result does not automatically confirm chronic kidney disease. Infection, fever, strenuous exercise and other medical conditions may temporarily affect urinary albumin levels. This guide explains why urine ACR testing is performed, how samples are collected, what the results mean and when further evaluation may be necessary. What Is a Urine ACR Test? A urine ACR test measures two substances in urine: Albumin: A protein normally found in the bloodstream that helps maintain fluid balance and performs other important functions. Creatinine: A waste product formed through muscle metabolism and excreted through the kidneys. The laboratory compares the amount of albumin with the amount of creatinine and reports the ratio. The test is commonly expressed in milligrams of albumin per gram of creatinine (mg/g). Because urine concentration changes throughout the day, using a ratio helps reduce the effect of urine dilution on the result. Urine ACR provides information about albumin leakage, but it does not directly measure the kidneys’ overall filtering rate. How Do Healthy Kidneys Prevent Albumin Loss? The kidneys contain microscopic filtering units called nephrons. Within each nephron, a structure called the glomerulus filters blood, allowing waste products and excess fluid to pass into the forming urine while retaining most larger proteins. The kidney tubules also help reabsorb certain filtered substances. Healthy kidneys normally allow only small amounts of albumin to appear in urine. When certain diseases affect kidney filtering structures, urinary albumin excretion may increase. This condition is called albuminuria. However, albuminuria can also occur temporarily during illness or other physiological changes. Why Is the Urine ACR Test Important? Urine ACR helps identify abnormalities that may not be detected through serum creatinine alone. Its clinical uses include: Detecting increased albumin leakage. Evaluating possible kidney damage. Assessing kidney-related risk in people with diabetes. Supporting the evaluation of hypertension-related kidney abnormalities. Helping classify chronic kidney disease. Monitoring changes in albuminuria over time. Supporting assessment of kidney and cardiovascular risk. Urine ACR is particularly useful when interpreted alongside eGFR. An elevated urine ACR is a clinical finding, not a diagnosis of a particular kidney disease. What Is the Normal Urine ACR Range? Urine ACR results are classified into three albuminuria categories. Urine ACR (mg/g) Category General interpretation Below 30 A1 Normal to mildly increased 30–299 A2 Moderately increased albuminuria 300 or above A3 Severely increased albuminuria A1: Below 30 mg/g This category is described as normal to mildly increased albuminuria. A result in this range is generally reassuring regarding albumin leakage, but it does not exclude all types of kidney disease. Other abnormalities, including reduced eGFR, may still require evaluation. A2: 30–299 mg/g This category indicates moderately increased albuminuria. The older term microalbuminuria is sometimes used to describe this range. Persistent albuminuria in this category may indicate kidney damage, particularly in people with diabetes or hypertension. However, the underlying cause must be determined clinically. A3: 300 mg/g or Above This category indicates severely increased albuminuria. It may be associated with a higher risk of kidney disease progression and cardiovascular complications. Significant or persistent abnormalities may require additional investigations. Does a High ACR Mean Kidney Failure? No. A high urine ACR means that increased albumin has been detected in urine. It does not independently determine the severity of kidney filtration impairment or establish that kidney failure is present. eGFR, previous results, symptoms and other medical findings are needed for a broader assessment. What Is the Difference Between Albuminuria and Proteinuria? Albuminuria and proteinuria are related but different terms. Albuminuria: Increased urinary excretion of albumin. Proteinuria: Increased urinary excretion of protein, which may include albumin and other proteins. Urine ACR measures albumin relative to creatinine. Urine protein-to-creatinine ratio (PCR or UPCR) measures total protein relative to creatinine. The choice of test depends on the suspected medical condition. Some kidney disorders involve proteins other than albumin, so urine ACR alone may not identify every type of proteinuria. How Is the Urine ACR Test Performed? Urine ACR usually requires a single urine specimen. Step 1: Urine Sample Collection A urine sample is collected in a container provided by the laboratory. Patients should follow the laboratory’s hygiene and collection instructions. A clean-catch midstream sample may be requested when appropriate. Step 2: Laboratory Measurement The laboratory measures urine albumin and urine creatinine. Step 3: Ratio Calculation The albumin-to-creatinine ratio is calculated. A simplified formula is: Urine ACR (mg/g) = Urine albumin (mg/dL) ÷ Urine creatinine (g/dL) Both measurements must be expressed in compatible units. Step 4: Clinical Interpretation The result is interpreted alongside previous measurements, serum creatinine, eGFR, medical history and other clinical findings. A single test does not always establish a chronic condition. Is a First-Morning Urine Sample Better? A first-morning urine sample is often preferred, particularly when confirming an abnormal result. It may reduce variation associated with daytime activity and changes in urine concentration. However, a random spot urine sample is also commonly accepted for initial screening. When urine ACR is elevated on a random sample, a first-morning specimen may be recommended for confirmation. Is a 24-Hour Urine Collection Necessary? Usually not. Spot urine ACR testing is commonly used for routine albuminuria assessment. A 24-hour urine collection may be considered in selected circumstances when more detailed measurement is clinically necessary. Do You Need to Fast Before a Urine ACR Test? Fasting is not routinely required for urine ACR testing alone. However, other blood or urine tests performed at the same time may have different preparation requirements. Patients should follow the instructions provided by the laboratory or healthcare professional. How Should You Prepare for the Test? General considerations
Understanding Microalbuminuria in Diabetes: What an Abnormal Urine Test Means

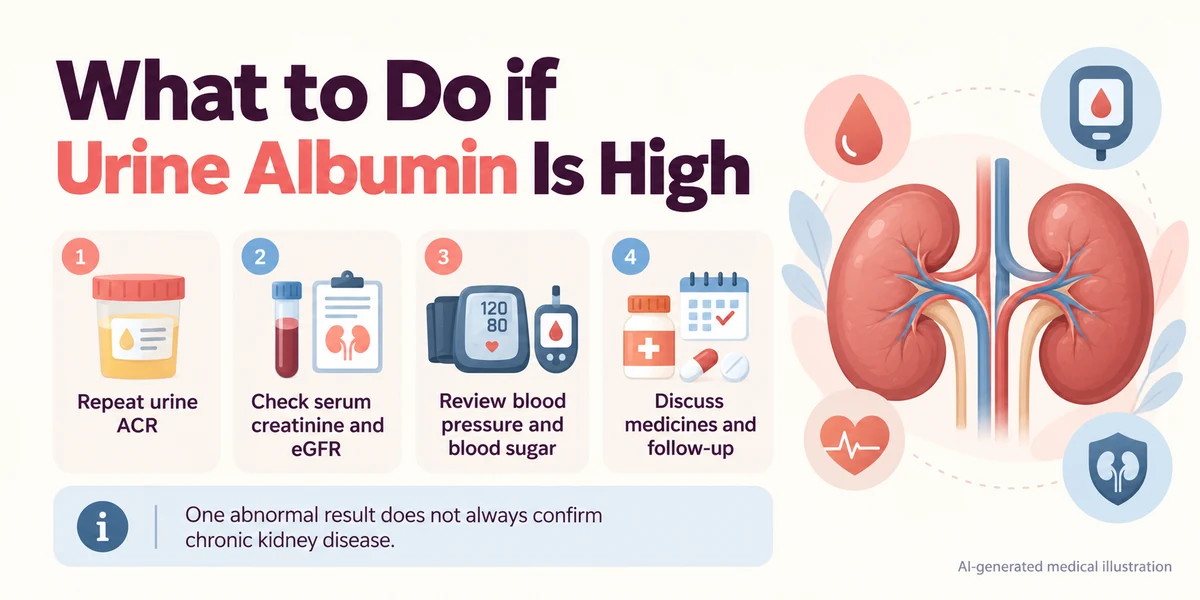
Microalbuminuria in diabetes means that a moderately increased amount of albumin is detected in urine. It may be an early marker of kidney damage, even when serum creatinine and estimated glomerular filtration rate (eGFR) appear relatively normal. The term microalbuminuria is still commonly used, but current medical guidelines generally refer to it as moderately increased albuminuria (A2). A urine albumin-to-creatinine ratio (uACR) between 30 and 299 mg/g falls within this category. However, one abnormal urine test does not automatically confirm diabetic kidney disease. Urine albumin can increase temporarily because of infection, fever, strenuous exercise or other medical factors. Urine ACR, eGFR, repeat testing and clinical evaluation help determine whether albuminuria is persistent and what may be causing it. What Is Microalbuminuria in Diabetes? Albumin is a protein normally found in the bloodstream. Healthy kidneys contain tiny filtering structures called glomeruli. These help remove waste products and excess fluid while retaining most albumin in the blood. When certain kidney conditions affect the filtration barrier, increased amounts of albumin may pass into urine. This is called albuminuria. In people with diabetes, long-term exposure to elevated blood glucose can damage the small blood vessels and filtering structures within the kidneys. However, albuminuria may also develop because of hypertension, glomerular disease or other medical conditions. Is Microalbuminuria Different From Albuminuria? Microalbuminuria is an older term describing a moderately increased amount of albumin in urine. Contemporary classification generally uses: A1: Normal to mildly increased albuminuria. A2: Moderately increased albuminuria. A3: Severely increased albuminuria. The term microalbuminuria does not mean that the albumin molecules are smaller than normal. It refers to the amount detected in urine. Why Is Albuminuria Important in People With Diabetes? Albuminuria is an important marker used when evaluating kidney health and cardiovascular risk. Persistent albuminuria may indicate kidney damage even when overall kidney filtration remains relatively preserved. It is also associated with increased cardiovascular risk. However, albuminuria does not always mean that a person has diabetic kidney disease, and it does not predict the same outcome for everyone. Early abnormalities may remain stable, improve or progress depending on the underlying condition and other health factors. Can Diabetes Damage the Kidneys Without Symptoms? Yes. Early diabetic kidney disease often develops without noticeable symptoms. A person may have: No swelling. Normal-looking urine. No pain. Relatively preserved eGFR. Serum creatinine within the laboratory reference range. Yet urine ACR testing may identify increased albumin. This is why blood and urine investigations are important when assessing kidney health in people with diabetes. Learn more about Diabetic Kidney Disease With Normal Creatinine. What Is a Urine Microalbumin Test? A urine microalbumin test is an investigation used to detect small increases in urinary albumin. The commonly recommended measurement is the urine albumin-to-creatinine ratio (uACR). It measures albumin relative to creatinine in a urine sample. Using the ratio helps account for differences in urine concentration caused by hydration and other factors. Urine ACR is useful for screening and monitoring kidney abnormalities in people with diabetes, hypertension and chronic kidney disease. How Is the Urine ACR Test Performed? Urine ACR testing is usually performed using a single urine sample. 1. Random Spot Urine Sample A sample can be collected at a convenient time. This is commonly used for routine screening. A 24-hour urine collection is not usually necessary for initial urine albumin screening. 2. First-Morning Urine Sample A first-morning specimen may be preferred when confirming an abnormal result. It can help reduce some variation related to physical activity and changes in urine concentration. 3. Laboratory Analysis The laboratory measures urinary albumin and creatinine and calculates their ratio. Results may be reported in mg/g or mg/mmol. The units matter because these two reporting systems use different numerical ranges. Follow the collection instructions provided by the laboratory or healthcare professional. What Is the Normal Range for Urine ACR? Urine ACR is commonly expressed as milligrams of albumin per gram of creatinine (mg/g). Urine ACR (mg/g) Category General interpretation Below 30 A1 Normal to mildly increased 30–299 A2 Moderately increased albuminuria 300 or above A3 Severely increased albuminuria What Does an ACR Below 30 mg/g Mean? An ACR below 30 mg/g falls within the normal to mildly increased albuminuria category. However, a result in this range does not independently rule out kidney disease. Other abnormalities, including reduced eGFR or structural kidney disorders, may still be present. What Does an ACR of 30–299 mg/g Mean? This is classified as moderately increased albuminuria. It may suggest kidney damage when persistent, particularly in people with relevant risk factors such as diabetes or hypertension. However, repeat testing and clinical evaluation are important. What Does an ACR of 300 mg/g or Above Mean? This is classified as severely increased albuminuria. It may be associated with greater kidney and cardiovascular risk, depending on the overall medical condition. Further evaluation may be appropriate to determine the cause and identify associated complications. Important: These categories describe urine albumin levels. They do not independently establish the diagnosis or cause of kidney disease. For a more detailed explanation, read Urine ACR Test Explained. Can a High Urine ACR Result Be Temporary? Yes. A single elevated urine ACR may be influenced by temporary factors. Possible contributors include: Fever or acute illness. Urinary tract infection. Strenuous exercise. Menstruation or specimen contamination. Markedly elevated blood glucose. Markedly elevated blood pressure. Heart failure or other acute medical conditions. These factors can temporarily influence urinary albumin measurements. They should be considered when interpreting a result, but an abnormal finding should not automatically be dismissed. Can Dehydration Affect the Test? Urine concentration can affect urine albumin measurements, particularly when albumin concentration is assessed without creatinine. The albumin-to-creatinine ratio helps reduce this variation. However, significant dehydration may affect kidney function or coincide with acute illness. The result should be interpreted in clinical context. Why Is Repeat Urine ACR Testing Necessary? Urine albumin excretion varies naturally from one measurement to another. A single elevated result may not establish persistent albuminuria. According to ADA guidance, clinicians commonly require at least two abnormal